PPG Morphology Features
The shape of a photoplethysmographic pulse waveform is not merely a stylized heartbeat trace. Every contour, slope, and inflection point encodes speci...
- PPG & Signal Processing
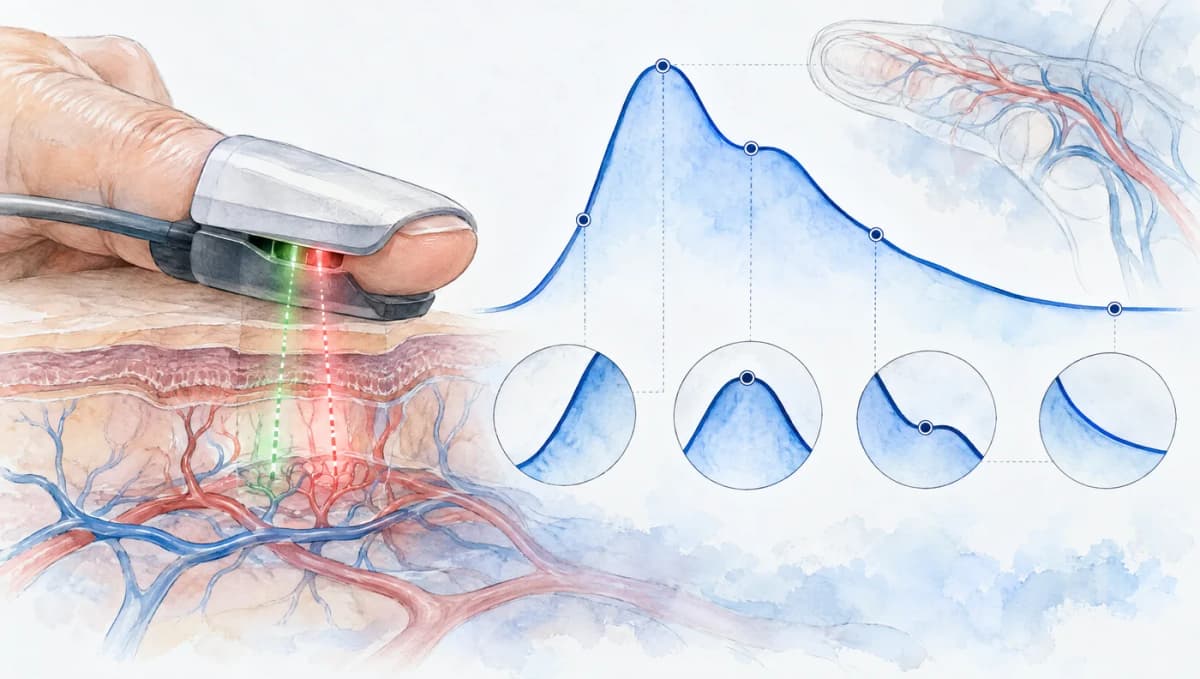
The shape of a photoplethysmographic pulse waveform is not merely a stylized heartbeat trace. Every contour, slope, and inflection point encodes specific information about the cardiovascular system that generated it. The systolic upstroke reflects left ventricular ejection dynamics. The dicrotic notch marks aortic valve closure. The diastolic decay reveals arterial compliance and peripheral resistance. The reflected wave component indicates arterial stiffness and wave reflection magnitude. Extracting and quantifying these morphological features transforms the PPG signal from a simple heart rate source into a window on cardiovascular health.
This article provides a comprehensive technical guide to PPG waveform morphology features, their physiological origins, extraction methods, and clinical applications. For foundational understanding of how PPG signals are generated, see our introduction to photoplethysmography. For information on how the AC and DC components relate to these features, see our guide on the AC/DC ratio in pulse oximetry.
Anatomy of the PPG Pulse Waveform
A single PPG pulse waveform, representing one cardiac cycle, contains several identifiable landmarks and regions. Understanding each is essential before extracting quantitative features.
The Systolic Phase
The systolic phase begins at the foot of the waveform (the trough between consecutive pulses) and extends to the systolic peak. This ascending limb reflects the arrival of the cardiac pulse wave at the measurement site.
The systolic upstroke is the rising portion from the foot to the peak. Its slope (dP/dt, or more precisely dI/dt where I is PPG intensity) is related to the rate of increase in local arterial blood volume, which depends on left ventricular contractility, proximal arterial compliance, and the propagation characteristics of the pulse wave. A steeper upstroke suggests higher pulse pressure and faster pulse wave arrival. As reviewed by Millasseau et al. (2006), the contour of the finger PPG (digital volume pulse) is sensitive to vasoactive drugs and is influenced by ageing and large artery stiffness (doi:10.1097/01.hjh.0000239277.05068.87).
The systolic peak is the maximum amplitude point of the pulse waveform. Its amplitude relative to the DC baseline defines the Perfusion Index. In subjects with stiff arteries, the systolic peak may be augmented by an early-returning reflected wave, producing a higher and sometimes broader peak than would be generated by the forward-traveling wave alone.
The Dicrotic Notch
The dicrotic notch is a small but physiologically significant deflection on the descending limb of the waveform. It corresponds to the momentary reversal of aortic flow and subsequent aortic valve closure at the end of ventricular systole. In central arterial pressure waveforms (measured invasively in the aorta), the dicrotic notch is sharp and well-defined. In peripheral PPG waveforms, it is attenuated by pulse wave damping and distortion during transmission through the arterial tree.
The visibility and prominence of the dicrotic notch vary with several factors:
- Age: The dicrotic notch is most prominent in young adults (ages 20-35) with compliant arteries and diminishes or may disappear entirely in older adults as arteries stiffen.
- Arterial stiffness: Independent of age, increased arterial stiffness reduces dicrotic notch prominence by increasing pulse wave velocity, which causes the reflected wave to arrive earlier and merge with the systolic wave.
- Heart rate: Higher heart rates compress the diastolic interval, reducing the time window in which the notch is visible.
- Measurement site: The dicrotic notch is more prominent in proximal arteries (brachial, radial) than distal sites (fingertip), and is often barely detectable in wrist PPG.
The Diastolic Phase
The diastolic phase extends from the dicrotic notch to the foot of the next pulse. The diastolic decay curve reflects the runoff of blood from the arterial system through the peripheral resistance vessels. In some subjects, particularly younger ones, a distinct diastolic peak (also called the reflected wave or diastolic wave) is visible as a secondary peak or inflection on the diastolic decay.
The diastolic peak arises from pulse wave reflection at sites of impedance mismatch in the arterial tree, primarily at arterial bifurcations and small muscular arteries. The timing and amplitude of this reflected wave carry important information about arterial stiffness and wave reflection magnitude.
Key Morphological Features and Indices
Augmentation Index (AIx)
The Augmentation Index quantifies the contribution of the reflected wave to the systolic pressure:
Where P2 is the amplitude at the inflection point (where the reflected wave arrives), P1 is the amplitude of the early systolic peak (before the reflected wave contribution), and PP is the total pulse pressure (systolic peak - diastolic foot).
In young adults with compliant arteries, the reflected wave arrives during diastole (after the systolic peak), so AIx is negative or near zero. In older adults with stiffer arteries, faster pulse wave velocity causes the reflected wave to arrive during late systole, augmenting the systolic peak and producing a positive AIx.
PPG-derived AIx is not identical to tonometric AIx because the two measure different quantities (volume versus pressure), but both rise with age as arteries stiffen.
Reflection Index (RI)
The Reflection Index quantifies the relative amplitude of the diastolic (reflected) wave compared to the systolic peak:
Where is the amplitude of the diastolic peak and is the amplitude of the systolic peak, both measured from the waveform foot.
RI reflects the magnitude of pulse wave reflection from the peripheral vasculature. Higher RI indicates stronger wave reflection, which is associated with increased peripheral vascular resistance and arterial stiffness. RI is also strongly influenced by vascular tone, so it responds to vasoactive drugs as well as to structural stiffness.
Stiffness Index (SI)
The Stiffness Index provides an estimate of aortic pulse wave velocity from the timing of the reflected wave in the PPG waveform:
Where is the time delay between the systolic peak and the diastolic peak (reflected wave). The rationale is that represents the transit time of the pulse wave from the heart to the major reflection site and back, and body height serves as a proxy for this path length.
SI was introduced by Millasseau et al. (2002) using digital volume pulse analysis and compared with carotid-femoral pulse wave velocity (cfPWV), the gold standard measure of arterial stiffness. In 87 asymptomatic subjects aged 21-68 years, SI correlated with cfPWV (r = 0.65, p < 0.0001), had a within-subject coefficient of variation of 9.6% at weekly intervals, and, like cfPWV, was independently related to age and mean arterial pressure (doi:10.1042/cs1030371). For more on pulse wave velocity measurement, see our dedicated article on PWV as an arterial stiffness marker.
Crest Time and Pulse Width
Crest time (CT) is the time from the waveform foot to the systolic peak. It reflects the rate of rise of the arterial pressure pulse and is influenced by left ventricular ejection dynamics and proximal arterial compliance. Shorter crest times are associated with faster pulse wave propagation and stiffer arteries.
Pulse width at various amplitude fractions (typically 10%, 25%, 50%, and 75% of peak amplitude) characterizes the overall shape of the waveform. Wider pulses at lower amplitude fractions suggest slower diastolic runoff and lower peripheral resistance. Pulse width features are commonly included in feature sets for cuffless blood pressure estimation.
Area Ratios
The ratio of the systolic area (from foot to dicrotic notch) to the diastolic area (from dicrotic notch to next foot) reflects the balance between cardiac ejection and diastolic runoff. This systolic-to-diastolic area ratio is related to total peripheral resistance and arterial compliance:
A higher area ratio suggests a waveform dominated by the systolic ejection phase, which can indicate reduced arterial compliance. Conversely, a lower area ratio (relatively more area under the diastolic curve) suggests better arterial compliance and lower vascular resistance. Elgendi (2012) reviews area-based and other characteristic features of the fingertip PPG waveform and the indexes derived from them (doi:10.2174/157340312801215782).
Second Derivative Analysis (SDPPG)
The second derivative of the PPG waveform, known as the acceleration plethysmogram (APG) or SDPPG, is one of the most extensively studied tools for extracting morphological information from PPG signals.
The Five Characteristic Waves
The SDPPG of a typical PPG pulse contains five identifiable waves, labeled a, b, c, d, and e by Takazawa et al. (1998) in their seminal paper (doi:10.1161/01.HYP.32.2.365):
- Wave a: The initial positive wave, corresponding to the early systolic acceleration of blood flow. It is the largest positive deflection and serves as the reference for ratio calculations.
- Wave b: The first negative wave, following a. It reflects the deceleration of the late systolic flow and the reduction in arterial distension rate. The b/a ratio increases with arterial stiffness because stiffer arteries transmit the pressure wave faster, creating a sharper transition from acceleration to deceleration.
- Wave c: The second positive wave, appearing in mid-systole. It corresponds to the re-acceleration caused by the reflected wave arrival (in subjects with moderate arterial stiffness) or the continued systolic flow pattern.
- Wave d: The second negative wave, corresponding to the dicrotic notch region. Its amplitude reflects the prominence of the dicrotic notch and therefore arterial compliance.
- Wave e: The final positive wave in the diastolic phase, corresponding to the diastolic reflected wave.
SDPPG Indices and Vascular Aging
Takazawa et al. (1998) defined an aging index from the SDPPG wave amplitudes:
Where each letter represents the amplitude of the corresponding wave (positive waves have positive values, negative waves have negative values). In 600 subjects (50 men and 50 women in each decade from the 20s to the 70s), this index increased with age (r = 0.80) and was higher in subjects with a history of diabetes, hypertension, hypercholesterolemia, or ischemic heart disease than in age-matched subjects without one (doi:10.1161/01.HYP.32.2.365).
In the same study, the individual SDPPG ratios also changed with age:
- b/a ratio: Increased with age.
- c/a ratio: Decreased with age.
- d/a ratio: Decreased with age. Related to dicrotic notch prominence and late systolic pressure augmentation.
- e/a ratio: Decreased with age. Related to the diastolic wave component.
Imanaga et al. (1998) compared the SDPPG with ultrasound-measured common carotid distensibility in 82 subjects aged 33-93 years and found that the magnitude of b/a correlated positively with arterial distensibility and decreased with the degree of carotid atherosclerosis (doi:10.1536/ihj.39.775). For clinical context on how arterial stiffness relates to cardiovascular conditions, see our conditions page.
Feature Extraction Methods
Time-Domain Feature Extraction
Time-domain feature extraction involves identifying specific fiducial points (landmarks) on the PPG waveform and computing temporal and amplitude relationships between them.
The critical first step is accurate identification of the systolic foot, systolic peak, dicrotic notch, and diastolic peak. Peak detection algorithms range from simple threshold crossings to sophisticated template-matching methods. Our peak detection algorithms guide covers these techniques in detail.
The dicrotic notch is particularly challenging to detect automatically because it varies widely in prominence and may be absent in waveforms from older subjects or those with stiff arteries. Common detection approaches include:
- First derivative zero-crossing: The dicrotic notch appears as a local minimum in the first derivative of the PPG waveform, detectable as a zero-crossing from negative to positive in the descending limb.
- Second derivative analysis: The dicrotic notch corresponds to the d-wave in the SDPPG, allowing its timing to be identified from SDPPG landmarks.
- Gaussian decomposition: Modeling the PPG pulse as a sum of Gaussian functions (typically 3-5), where one Gaussian corresponds to the dicrotic notch region.
Frequency-Domain Analysis
Fourier decomposition of the PPG waveform into harmonic components provides an alternative feature set. The relative amplitudes and phases of the first 5-10 harmonics capture the waveform shape in a compact representation. The first harmonic amplitude reflects the fundamental pulse amplitude, while higher harmonics encode waveform sharpness and complexity.
The harmonic-to-fundamental ratio (amplitude of higher harmonics relative to the first harmonic) can serve as a measure of waveform complexity. This frequency-domain approach has the advantage of being less dependent on precise fiducial point detection, which can be error-prone in noisy or low-quality signals.
Machine Learning Feature Extraction
Modern approaches increasingly use machine learning to extract features from PPG waveforms without requiring explicit fiducial point identification. Convolutional neural networks can learn relevant waveform features directly from raw or minimally preprocessed PPG segments.
Slapnicar et al. (2019) applied deep learning with spectro-temporal ResNet architecture to PPG waveforms for blood pressure estimation, achieving mean absolute errors of 9.43 mmHg for systolic and 6.88 mmHg for diastolic blood pressure in a leave-one-subject-out evaluation on 510 MIMIC III subjects (doi:10.3390/s19153420). The authors also found that personalizing the models substantially improved results, while a good general model was difficult to obtain. For more information on how machine learning is applied to PPG signals, see our algorithms overview.
Clinical Applications of Morphology Analysis
Vascular Age Estimation
PPG morphology-based vascular age estimation is one of the most mature clinical applications. By comparing a subject's PPG morphological indices (particularly SDPPG aging index, augmentation index, and stiffness index) against age-stratified reference populations, a "vascular age" can be estimated that reflects the functional state of the arterial system rather than chronological age.
A vascular age significantly exceeding chronological age suggests premature arterial aging, which is a risk factor for cardiovascular events. Conversely, a vascular age below chronological age may indicate favorable vascular health. In 524 hypertensive patients, Bortolotto et al. (2000) found that the SDPPG aging index was higher in those with atherosclerotic alterations and was influenced by age and atherosclerosis, although carotid-femoral PWV was the stronger independent marker (doi:10.1016/S0895-7061(99)00192-2).
Atrial Fibrillation Detection
While atrial fibrillation detection from PPG primarily relies on heart rate irregularity (absence of the regular sinus rhythm pattern), morphological features provide additional discriminative power. During AF, PPG pulses show beat-to-beat variability in amplitude, shape, and timing that is distinct from the regular morphology variation seen in normal sinus rhythm with respiratory sinus arrhythmia.
Combining morphology features (pulse amplitude variability, waveform complexity measures) with rhythm irregularity metrics is a common strategy for improving AF detection. For more on how AF detection works from PPG, see our AF detection algorithms page.
Sleep Staging and Autonomic Assessment
PPG morphology changes during different sleep stages, reflecting the autonomic nervous system shifts that accompany sleep architecture transitions. During deep slow-wave sleep, sympathetic withdrawal leads to vasodilation, increasing pulse amplitude and shifting morphological indices. During REM sleep, sympathetic surges can cause transient vasoconstriction and morphology changes.
Measuring these morphological shifts over a night of sleep provides a non-invasive window into autonomic balance that complements heart rate variability analysis. Wrist-worn wearables that capture continuous PPG during sleep are positioned to exploit these morphological features for improved sleep staging and autonomic health assessment.
Challenges and Limitations
Signal Quality Dependence
Morphology analysis requires substantially higher signal quality than simple heart rate extraction. Heart rate can be estimated from heavily corrupted signals using frequency-domain methods, but morphological features require accurate representation of the waveform shape, including small features like the dicrotic notch. Signal quality assessment is therefore essential before morphology analysis. For techniques to handle noisy PPG signals, see our motion artifact removal guide.
Measurement Site Variability
PPG waveform morphology varies significantly across body sites due to pulse wave transmission effects. The waveform at the fingertip differs from the earlobe, which differs from the wrist. Features extracted at one site cannot be directly compared with reference values established at another site without site-specific calibration or normalization. This is particularly relevant for wrist-based wearables, where the PPG waveform is typically more damped and less feature-rich than fingertip recordings.
Individual Variability
Even at a fixed measurement site, PPG morphology varies substantially between individuals due to differences in arterial anatomy, body composition, skin properties, and cardiovascular physiology. Population-level correlations between morphological features and clinical parameters (e.g., blood pressure, arterial stiffness) may not translate to accurate individual-level estimation. Establishing personalized baselines and tracking within-individual trends is generally more robust than applying population-derived thresholds.
Summary
PPG waveform morphology analysis extends the information extractable from photoplethysmography far beyond heart rate and SpO2. By quantifying features of the pulse waveform shape, including systolic upstroke characteristics, dicrotic notch prominence, reflected wave timing and amplitude, and second derivative wave patterns, researchers and clinicians can assess arterial stiffness, vascular age, autonomic function, and potentially estimate blood pressure non-invasively. While challenges remain in signal quality requirements, measurement site standardization, and individual variability, the growing deployment of high-quality PPG sensors in clinical and consumer devices is accelerating the translation of morphology analysis from research to practice.
Frequently Asked Questions
What is the dicrotic notch in a PPG waveform?
The dicrotic notch is a small downward deflection that appears on the descending (diastolic) portion of the PPG pulse waveform. It corresponds to the momentary retrograde flow and subsequent aortic valve closure at the end of ventricular systole. In PPG, the dicrotic notch is attenuated compared to central arterial waveforms because the pulse wave undergoes distortion as it travels to the periphery. The prominence of the dicrotic notch decreases with age and arterial stiffness: young adults with compliant arteries show a distinct notch, while older adults with stiff arteries often show a smooth, notch-free descending limb.
What does the second derivative of a PPG signal (SDPPG) reveal?
The second derivative of the PPG signal (SDPPG or acceleration plethysmogram) amplifies inflection points in the original waveform, making subtle morphological features more visible and quantifiable. The SDPPG typically contains five characteristic waves labeled a through e, whose relative amplitudes reflect arterial stiffness and vascular aging. The b/a ratio (ratio of the second to first wave amplitude) increases with arterial stiffness, while the d/a ratio decreases. Takazawa et al. (1998) showed in 600 subjects that the aging index (b-c-d-e)/a derived from SDPPG increases with chronological age (r = 0.80) and is higher in people with cardiovascular risk factors (doi:10.1161/01.HYP.32.2.365).
Can PPG waveform features estimate blood pressure?
PPG waveform morphology features have been extensively studied for cuffless blood pressure estimation, but with limited clinical success so far. Features like pulse width, diastolic peak timing, reflection index, and area ratios correlate with blood pressure in population studies, but the correlations are generally insufficient for individual-level blood pressure tracking. The primary challenge is that PPG morphology is influenced by multiple physiological variables simultaneously (arterial stiffness, vascular tone, stroke volume, heart rate), making it difficult to isolate the blood pressure contribution. Current research focuses on combining morphology features with machine learning and pulse transit time for improved accuracy.
How does age affect PPG waveform shape?
Aging produces characteristic changes in PPG waveform morphology driven by progressive arterial stiffening. In young adults (ages 20-30), PPG waveforms show a sharp systolic peak, a clear dicrotic notch, and a prominent diastolic peak. The augmentation index is low and the reflection index is moderate. With aging, arterial pulse wave velocity increases, causing the reflected wave to return earlier and merge with the systolic peak. By age 60-70, the dicrotic notch often disappears, the waveform becomes more triangular, and augmentation index increases. These changes are well-documented and form the basis of PPG-based vascular age estimation.
References
- Millasseau, S. C., Ritter, J. M., Takazawa, K., & Chowienczyk, P. J. (2006). Contour analysis of the photoplethysmographic pulse measured at the finger. Journal of Hypertension, 24(8), 1449-1456. https://doi.org/10.1097/01.hjh.0000239277.05068.87
- Millasseau, S. C., et al. (2002). Determination of age-related increases in large artery stiffness by digital pulse contour analysis. Clinical Science, 103(4), 371-377. https://doi.org/10.1042/cs1030371
- Elgendi, M. (2012). On the analysis of fingertip photoplethysmogram signals. Current Cardiology Reviews, 8(1), 14-25. https://doi.org/10.2174/157340312801215782
- Takazawa, K., et al. (1998). Assessment of vasoactive agents and vascular aging by the second derivative of photoplethysmogram waveform. Hypertension, 32(2), 365-370. https://doi.org/10.1161/01.HYP.32.2.365
- Imanaga, I., Hara, H., Koyanagi, S., & Tanaka, K. (1998). Correlation between wave components of the second derivative of plethysmogram and arterial distensibility. Japanese Heart Journal, 39(6), 775-784. https://doi.org/10.1536/ihj.39.775
- Slapnicar, G., Mlakar, N., & Lustrek, M. (2019). Blood pressure estimation from photoplethysmogram using a spectro-temporal deep neural network. Sensors, 19(15), 3420. https://doi.org/10.3390/s19153420
- Bortolotto, L. A., et al. (2000). Assessment of vascular aging and atherosclerosis in hypertensive subjects: second derivative of photoplethysmogram versus pulse wave velocity. American Journal of Hypertension, 13(2), 165-171. https://doi.org/10.1016/S0895-7061(99)00192-2
Core guide: PPG Waveform Morphology: Features and Analysis
Related articles
Pulse Wave Analysis Using PPG: Waveform Features, Vascular Health, and Clinical Applications
Complete guide to pulse wave analysis from PPG signals. Covers augmentation index, stiffness index, derivatives, fiducial points, and vascular assessment.
PPG Waveform: Anatomy, Features, and Clinical Meaning
The PPG waveform encodes far more than heart rate. Learn the anatomy of each pulse wave, what dicrotic notch position means, and how waveform shape reveals cardiovascular health.
PPG Stress Detection Methods: Physiological Stress Measurement from PPG Features
**Stress detection is one of the most commercially visible applications of PPG technology, yet it remains one of the most scientifically challenging.*...
PPG Biomarkers for Early Sepsis Screening: Signal Features, Evidence & Clinical Potential
**Sepsis kills approximately 11 million people annually worldwide and remains the leading cause of death in hospitalized patients, yet the average tim...
Savitzky-Golay Filter for PPG: Smoothing Without Flattening Morphology
Savitzky-Golay filter for PPG smooths noise while preserving peaks and slopes when window length, polynomial order, and edge handling are chosen well.