PPG Perfusion Index Clinical
Perfusion Index (PI) is one of the most underutilized parameters available from photoplethysmography, yet it provides uniquely direct information abou...
- PPG & Signal Processing
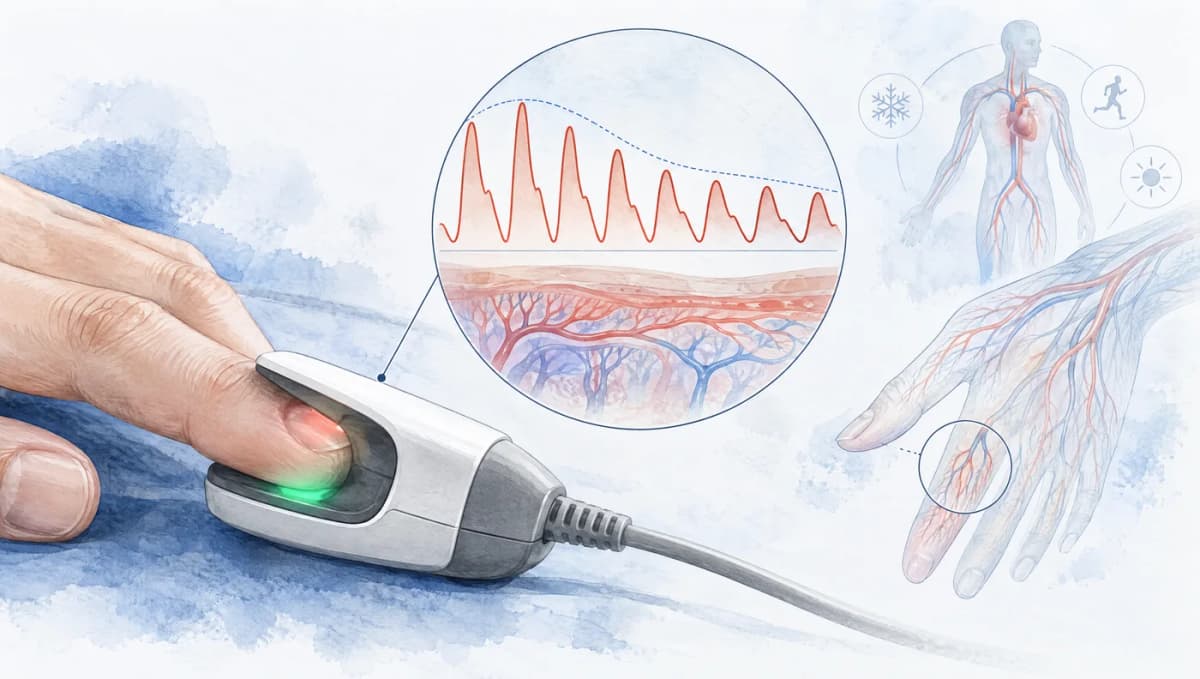
Perfusion Index (PI) is one of the most underutilized parameters available from photoplethysmography, yet it provides uniquely direct information about peripheral vascular tone and tissue perfusion that no other non-invasive measurement offers. Every modern pulse oximeter already captures the data needed to compute PI, and many clinical devices now display it alongside SpO2 and heart rate. Despite this availability, PI remains poorly understood by many clinicians and largely unexploited in consumer wearables.
This article provides a comprehensive technical explanation of how Perfusion Index is derived from the PPG signal, what physiological information it encodes, and how it is being applied in clinical settings from anesthesia monitoring to neonatal screening. For foundational background on the PPG signal and its components, see our introduction to photoplethysmography.
What Is Perfusion Index?
Perfusion Index quantifies the strength of the pulsatile blood flow at the measurement site relative to the static (non-pulsatile) signal. It is expressed as a percentage and calculated from the two fundamental components of the PPG signal:
Where AC is the peak-to-trough amplitude of the pulsatile component (driven by arterial blood volume changes with each heartbeat) and DC is the baseline level of the signal (reflecting absorption by non-pulsatile tissue, venous blood, and baseline arterial blood volume).
A PI of 2.0 means that the pulsatile component is 2% of the total signal. A PI of 0.2 means the pulsatile component is only 0.2% of the total signal, indicating very weak peripheral pulsatile flow. This ratio directly reflects how much arterial blood volume change is occurring at the measurement site with each cardiac cycle, which is determined by the combination of cardiac output, local vascular tone, and arterial compliance.
The elegance of PI as a measurement is its simplicity: it requires no additional hardware beyond what a standard pulse oximeter already contains, no calibration against invasive measurements, and no complex signal processing algorithms. It is a direct optical measurement of a meaningful physiological quantity. To see how a given PI value compares with published adult and newborn values, try the perfusion index checker.
Physiological Determinants of Perfusion Index
PI is not a single physiological parameter but rather an integrated measure reflecting multiple cardiovascular variables. Understanding what drives PI changes is essential for interpreting it clinically.
Sympathetic Vascular Tone
The dominant determinant of PI at peripheral sites (fingertip, toe) is sympathetic vasoconstrictor tone. The digital arteries are richly innervated by sympathetic vasomotor nerves, and changes in sympathetic outflow produce rapid and dramatic changes in peripheral vascular resistance. During sympathetic activation (stress, cold exposure, hypovolemia, pain), arteriolar constriction reduces the amplitude of the blood volume pulse, decreasing PI. During sympathetic withdrawal (warming, anesthesia, vasodilator administration), arteriolar dilation increases pulsatile flow and raises PI.
Shelley (2007, doi:10.1213/01.ane.0000269512.82836.c9) reviewed how the pulse oximeter waveform carries physiological information beyond oxygen saturation and heart rate, including vascular volume status and sympathetic tone. That sensitivity to sympathetic tone is why PI is studied as an indicator of autonomic nervous system shifts.
Cardiac Output and Stroke Volume
PI is also influenced by central hemodynamics. Higher stroke volume generates a larger pulse pressure wave, which translates to a larger pulsatile component at peripheral sites. Patients with reduced cardiac output from heart failure, severe hypovolemia, or cardiogenic shock tend to have lower PI values. However, the relationship between cardiac output and PI is modulated by peripheral vascular tone, so PI cannot be used as a standalone surrogate for cardiac output without accounting for vasomotor status.
Local Factors
Local tissue temperature, perfusion pressure, and vascular anatomy all affect PI. The fingertip typically shows higher PI than the earlobe or forehead due to the dense arterial anastomoses in digital tissue. Peripheral vascular disease, Raynaud phenomenon, and local compression can reduce PI independent of systemic hemodynamic status. Understanding PPG sensor placement and its effects on signal quality is directly relevant to PI measurement.
Normal Ranges and Variability
Establishing "normal" PI values has proven challenging due to the parameter's inherent variability. Lima et al. (2002, doi:10.1097/00003246-200206000-00006) measured PI in 108 healthy adults (median 1.4, range 0.3-10.0) and 37 critically ill patients, and found that a cutoff of 1.4 best reflected poor peripheral perfusion, defined as a capillary refill time over 2 seconds and a core-to-toe temperature difference of at least 7 °C.
In healthy adults at rest, fingertip PI values typically range from 1.0 to 20.0, with a median around 3.0-5.0. The wide range reflects individual differences in peripheral vascular tone, ambient temperature, and digital arterial anatomy. Intra-individual variability is also substantial: PI can change by 2-5 fold within minutes in response to temperature changes, posture shifts, or emotional state.
This variability means that PI is most useful when tracked as a trend within a single patient rather than compared against fixed population thresholds. A patient whose PI drops from 4.0 to 0.8 is communicating important information about their hemodynamic trajectory, regardless of where 0.8 falls relative to a population reference range.
Measurement Site Differences
PI varies substantially across body sites due to differences in local vascular anatomy and sympathetic innervation density:
- Fingertip: Highest PI values (typically 1.0-20.0) due to dense arteriovenous anastomoses. Most responsive to sympathetic tone changes.
- Toe: Similar range to fingertip but with greater susceptibility to peripheral vascular disease.
- Earlobe: Lower PI (typically 0.5-5.0) with less sympathetic variability, making it more stable but less sensitive.
- Forehead: Lowest PI (typically 0.3-3.0) but most resistant to vasoconstriction-related signal loss because forehead vessels are less sympathetically innervated.
Clinical Applications
Anesthesia and Regional Blockade Assessment
One of the most validated clinical applications of PI is monitoring the effectiveness of regional anesthesia. When a sympathetic nerve block takes effect (epidural, spinal, brachial plexus block), vasoconstriction in the blocked territory is released, causing local vasodilation and a corresponding increase in PI.
Sebastiani et al. (2012, doi:10.1007/s12630-012-9796-3) studied 30 patients receiving interscalene nerve catheters. In the 25 with successful blocks, the PI difference between the blocked and unblocked arm increased within five minutes of local anesthetic application and kept rising until 15 minutes, suggesting PI as an indicator of successful block placement in awake patients.
For epidural anesthesia, Ginosar et al. (2009, doi:10.1111/j.1399-6576.2009.01968.x) found that toe PI rose by 326% within 20 minutes of lumbar epidural anesthesia in 29 analyzable patients and met sympathectomy criteria earlier than mean arterial pressure or toe temperature (26 of 29 patients at 10 minutes, versus 6 and 8 of 29). This application is particularly valuable because it provides continuous, objective monitoring compared to the intermittent, subjective nature of pinprick testing.
Neonatal Screening and Assessment
PI has emerged as a valuable screening tool in neonatal medicine, where non-invasive monitoring is especially important due to the fragility of neonatal patients.
De Felice et al. (2005, doi:10.1136/adc.2004.068882) showed that PI in the first minutes after birth can flag subclinical chorioamnionitis in term newborns: in a prospective validation set of 329 newborns, cut-offs of 1.74 or less at one minute and 2.18 or less at five minutes gave 100% sensitivity and 99.4% specificity. Low PI in the immediate postnatal period reflects poor peripheral perfusion, which can indicate systemic hypoperfusion, congenital heart disease, or sepsis.
Granelli and Ostman-Smith (2007) proposed using PI as a screening tool for critical left heart obstruction in newborns (doi:10.1111/j.1651-2227.2007.00439.x). In 10,000 healthy newborns the median PI was 1.70 (5th percentile 0.70). Of 9 infants with duct-dependent systemic circulation, 5 (56%) had a pre- or postductal PI below 0.70, and a PI under 0.70 carried an odds ratio of 23.75 for left heart obstruction, suggesting PI could add to SpO2 screening.
Sepsis and Hemodynamic Instability
Peripheral perfusion assessment is central to sepsis management, and PI provides a continuous, quantitative measure of perfusion that complements clinical examination.
He et al. (2015, doi:10.1186/s13054-015-1057-8) followed 202 critically ill patients undergoing resuscitation and found that PI measured 8 hours after early resuscitation was an independent risk factor for 30-day mortality, with a PI of 0.6 or less linked to poor outcomes. Combining low PI with a central venous oxygen saturation below 70% identified the group with the lowest survival, suggesting PI as a marker of resuscitation adequacy.
van Genderen et al. (2014, doi:10.1186/cc13905) followed 111 patients after major abdominal surgery and found that capillary refill time, PI and the forearm-to-fingertip skin temperature gradient were all altered in the 19 patients who went on to develop severe complications, with PI altered from the first postoperative day. PI has the advantage of continuous automated measurement without requiring clinician assessment. For understanding how PPG-derived metrics relate to cardiovascular conditions, see our conditions overview.
Prediction of Hypotension
Low PI has been investigated as a predictor of impending hypotension in perioperative and critical care settings. The rationale is that sympathetic vasoconstriction (reducing PI) is an early compensatory response to falling cardiac output or intravascular volume depletion, occurring before blood pressure itself begins to decline.
Toyama et al. (2013, doi:10.1093/bja/aet058) found that a higher baseline PI predicted spinal anesthesia-induced hypotension during Caesarean delivery: a cutoff of 3.5 identified at-risk parturients with 81% sensitivity and 86% specificity. In a related application, Mowafi et al. (2009, doi:10.1213/ane.0b013e31818fc35b) showed that a PI decrease of 10% or more detected intravascular injection of an epinephrine-containing epidural test dose with 100% sensitivity and specificity in 40 propofol-anesthetized adults.
Technical Considerations for PI Measurement
Wavelength Selection
Most clinical pulse oximeters compute PI from the infrared channel (940nm) rather than the red channel (660nm). The infrared wavelength is preferred for several reasons: it provides a more stable PI measurement because absorption at 940nm is less dependent on oxygen saturation than at 660nm, it has greater tissue penetration providing a more representative sampling of the vascular bed, and it is less affected by melanin absorption. For a detailed explanation of wavelength-specific behavior in PPG, see our wavelength comparison guide.
Signal Quality and Artifacts
PI calculation is sensitive to motion artifact because any non-cardiac fluctuation in the PPG signal can corrupt the AC component measurement. Most devices apply a combination of artifact detection and temporal averaging to stabilize PI readings. A moving average window of 4-8 seconds is typical, providing a balance between responsiveness and noise rejection.
Low PI values (below 0.3-0.5) present a particular challenge because the pulsatile signal approaches the noise floor of the measurement system. At very low PI, the AC component may be indistinguishable from noise, rendering PI unreliable. Pulse oximeter manufacturers typically flag PI values below a device-specific threshold (often 0.2-0.3) as potentially unreliable, and some devices will not report SpO2 when PI is below this threshold because the pulsatile signal is insufficient for accurate ratio-of-ratios calculation. For techniques used to handle noisy PPG signals, see our guide on motion artifact removal.
Perfusion Index vs. Pleth Variability Index
Perfusion Index should not be confused with Pleth Variability Index (PVI), a related but distinct parameter developed by Masimo Corporation. While PI measures the absolute ratio of pulsatile to non-pulsatile signal, PVI measures the respiratory-induced variation in PI over a respiratory cycle:
PVI reflects the degree to which mechanical ventilation modulates stroke volume, and it is used as a predictor of fluid responsiveness in mechanically ventilated patients. Cannesson et al. (2008) demonstrated that a PVI above 14% predicted fluid responsiveness with a sensitivity of 81% and specificity of 100% in mechanically ventilated patients under general anesthesia (n = 25, doi:10.1093/bja/aen133).
PI in Consumer Wearables
Despite PI's clinical utility, it remains largely absent from consumer wearable devices. Most smartwatches and fitness trackers measure continuous PPG signals that contain both AC and DC components, meaning the raw data to compute PI is available. However, several technical challenges limit consumer PI implementation.
Wrist-based reflectance PPG has inherently lower and more variable PI than fingertip transmission PPG. The wrist measurement site has less dense arterial vasculature, and reflectance-mode geometry produces a weaker pulsatile signal relative to the DC baseline. Wrist PI values are typically 0.1-2.0, compared to 1.0-20.0 at the fingertip, making the measurement more susceptible to noise and artifact contamination.
Motion artifact is especially problematic for PI because any movement-induced signal fluctuation directly corrupts the AC measurement. While sophisticated signal processing algorithms can extract heart rate from motion-corrupted signals (because heart rate requires only frequency information), PI requires accurate amplitude measurement, which is more demanding.
Nevertheless, PI from wrist PPG represents an untapped opportunity for consumer health monitoring. Continuous PI tracking could provide insights into autonomic nervous system activity, stress responses, thermoregulatory status, and cardiovascular fitness that current wearable metrics do not capture. As sensor hardware and algorithms improve, PI may become a standard wearable metric alongside heart rate and HRV. For where PI fits among the waveform features used in wearable studies, see this overview of perfusion index in wearable research. To explore the current state of PPG-derived algorithm development, visit our algorithms overview.
Research Frontiers
PI-Based Pain Assessment
Quantifying pain objectively remains one of medicine's most persistent challenges. Because PI responds to sympathetic nervous system activation, which occurs during pain, several research groups have explored PI as an objective pain indicator. While PI cannot replace subjective pain assessment, it may serve as an adjunctive tool for monitoring pain in non-communicative patients such as sedated ICU patients, neonates, or patients with cognitive impairment.
Continuous Hemodynamic Monitoring
Integration of PI with other PPG-derived parameters such as heart rate variability, respiratory rate, and pulse wave morphology features could enable comprehensive non-invasive hemodynamic monitoring. Machine learning models trained on multi-parameter PPG data, including PI, may be able to estimate cardiac output, systemic vascular resistance, and intravascular volume status with clinically useful accuracy. This remains an active area of research with significant potential for both clinical and consumer applications.
PI in Telemedicine and Remote Monitoring
As telemedicine expands, the ability to assess peripheral perfusion remotely becomes increasingly valuable. Fingertip pulse oximeters that report PI are inexpensive and widely available, and PI data transmitted from home could help clinicians monitor patients with heart failure, sepsis risk, or post-surgical recovery. The key challenge is establishing evidence-based PI thresholds and trends that trigger clinical action in the remote monitoring context.
Summary
Perfusion Index transforms the pulse oximeter from a device that merely reports SpO2 and heart rate into a peripheral perfusion monitor. By quantifying the ratio of pulsatile to non-pulsatile PPG signal, PI provides continuous, non-invasive insight into sympathetic vascular tone, hemodynamic status, and tissue perfusion. Its clinical applications span anesthesia monitoring, neonatal screening, sepsis assessment, and perioperative hemodynamic management, with emerging research exploring pain assessment and remote monitoring.
The parameter's simplicity of calculation belies the richness of physiological information it encodes. As both clinical and consumer PPG devices continue to advance, Perfusion Index is poised to become a standard vital sign alongside heart rate, SpO2, and blood pressure.
Frequently Asked Questions
What is a normal Perfusion Index value?
In healthy adults at rest, Perfusion Index typically ranges from 0.02 to 20.0, with most values falling between 1.0 and 5.0. Values below 0.5 are generally considered indicative of poor peripheral perfusion, while values above 5.0 suggest strong pulsatile flow. However, PI is highly variable between individuals and body sites, so trends within a single patient are more clinically meaningful than absolute thresholds. Lima et al. (2002, doi:10.1097/00003246-200206000-00006) found that a PI below 1.4 at the fingertip correlates with reduced peripheral perfusion in critically ill adults.
How is Perfusion Index calculated from a PPG signal?
Perfusion Index is calculated as the ratio of the pulsatile (AC) component to the non-pulsatile (DC) component of the PPG signal, expressed as a percentage: . The AC component represents the cardiac-driven change in blood volume, while the DC component represents baseline absorption from tissue, venous blood, and non-pulsatile arterial blood. Most clinical pulse oximeters compute PI continuously using the infrared wavelength channel (typically 940nm) to minimize the influence of oxygen saturation on the measurement.
Can Perfusion Index predict outcomes in critically ill patients?
Multiple studies have demonstrated that low Perfusion Index is associated with adverse outcomes in critical care. He et al. (2015, doi:10.1186/s13054-015-1057-8) found that a PI of 0.6 or less after early resuscitation was associated with higher 30-day mortality in critically ill patients. In newborns, De Felice et al. (2005, doi:10.1136/adc.2004.068882) showed that PI within the first minutes of life identified subclinical chorioamnionitis with high accuracy. PI serves as an early marker of hemodynamic compromise because peripheral vasoconstriction, which reduces PI, is one of the body's earliest compensatory responses to shock.
Does skin pigmentation affect Perfusion Index accuracy?
Perfusion Index is less affected by skin pigmentation than SpO2 measurements because PI uses the ratio of AC to DC components at a single wavelength rather than the ratio-of-ratios across two wavelengths. Since melanin absorption affects both AC and DC components proportionally within the same wavelength, the ratio partially cancels out the melanin effect. However, very high melanin absorption can reduce overall signal quality, leading to noisier PI estimates. Using the infrared channel (940nm) further minimizes melanin influence, as melanin absorption is substantially lower at infrared wavelengths.
References
- Cannesson M, Desebbe O, Rosamel P, et al. (2008). Pleth variability index to monitor the respiratory variations in the pulse oximeter plethysmographic waveform amplitude and predict fluid responsiveness in the operating theatre. Br J Anaesth, 101(2), 200-206. https://doi.org/10.1093/bja/aen133
- de-Wahl Granelli A, Östman-Smith I. (2007). Noninvasive peripheral perfusion index as a possible tool for screening for critical left heart obstruction. Acta Paediatr, 96(10), 1455-1459. https://doi.org/10.1111/j.1651-2227.2007.00439.x
- De Felice C, Del Vecchio A, Criscuolo M, et al. (2005). Early postnatal changes in the perfusion index in term newborns with subclinical chorioamnionitis. Arch Dis Child Fetal Neonatal Ed, 90(5), F411-F414. https://doi.org/10.1136/adc.2004.068882
- Ginosar Y, Weiniger CF, Meroz Y, et al. (2009). Pulse oximeter perfusion index as an early indicator of sympathectomy after epidural anesthesia. Acta Anaesthesiol Scand, 53(8), 1018-1026. https://doi.org/10.1111/j.1399-6576.2009.01968.x
- He H, Long Y, Liu D, Wang X, Zhou X. (2015). Clinical classification of tissue perfusion based on the central venous oxygen saturation and the peripheral perfusion index. Crit Care, 19. https://doi.org/10.1186/s13054-015-1057-8
- Lima AP, Beelen P, Bakker J. (2002). Use of a peripheral perfusion index derived from the pulse oximetry signal as a noninvasive indicator of perfusion. Crit Care Med, 30(6), 1210-1213. https://doi.org/10.1097/00003246-200206000-00006
- Mowafi HA, Ismail SA, Shafi MA, Al-Ghamdi AA. (2009). The efficacy of perfusion index as an indicator for intravascular injection of epinephrine-containing epidural test dose in propofol-anesthetized adults. Anesth Analg, 108(2), 549-553. https://doi.org/10.1213/ane.0b013e31818fc35b
- Sebastiani A, Philippi L, Boehme S, et al. (2012). Perfusion index and plethysmographic variability index in patients with interscalene nerve catheters. Can J Anaesth, 59(12), 1095-1101. https://doi.org/10.1007/s12630-012-9796-3
- Shelley KH. (2007). Photoplethysmography: beyond the calculation of arterial oxygen saturation and heart rate. Anesth Analg, 105(6 Suppl), S31-S36. https://doi.org/10.1213/01.ane.0000269512.82836.c9
- Toyama S, Kakumoto M, Morioka M, et al. (2013). Perfusion index derived from a pulse oximeter can predict the incidence of hypotension during spinal anaesthesia for Caesarean delivery. Br J Anaesth, 111(2), 235-241. https://doi.org/10.1093/bja/aet058
- van Genderen ME, Paauwe J, de Jonge J, et al. (2014). Clinical assessment of peripheral perfusion to predict postoperative complications after major abdominal surgery early: a prospective observational study in adults. Crit Care, 18(3). https://doi.org/10.1186/cc13905
Core guide: Perfusion Index in PPG Signal Processing
Related articles
Neonatal Perfusion Index Explained: How PPG Supports NICU Monitoring
Understand neonatal perfusion index, how PPG derives it from the waveform, and how NICU teams use bedside trends to assess peripheral flow in newborns.
Neonatal Oxygen Monitoring Guide: SpO2 Targets, Sensors, and Clinical Protocols
Clinical guide to neonatal pulse oximetry covering SpO2 target ranges, sensor placement, alarm thresholds, and evidence-based monitoring protocols for preterm and term newborns.
What Is Pulse Wave Velocity? Normal Ranges, Clinical Thresholds, and PPG Estimation
Plain-language explanation of pulse wave velocity, normal ranges by age, clinical risk thresholds, and how PPG wearables estimate PWV from pulse transit time.
Pulse Wave Analysis Using PPG: Waveform Features, Vascular Health, and Clinical Applications
Complete guide to pulse wave analysis from PPG signals. Covers augmentation index, stiffness index, derivatives, fiducial points, and vascular assessment.
Wearable AHI Estimation: Can PPG Approximate the Apnea-Hypopnea Index?
Can wearable PPG estimate AHI? See where ODI-based severity tracking helps, where calibration fails, and what validation wearables need before clinical use.