Graph Neural Networks for PPG: Modeling Physiological Relationships Across Multi-Site Signals
Graph neural networks represent PPG features and physiological signals as nodes in a graph, with edges encoding known or learned relationships between...
- PPG & Signal Processing
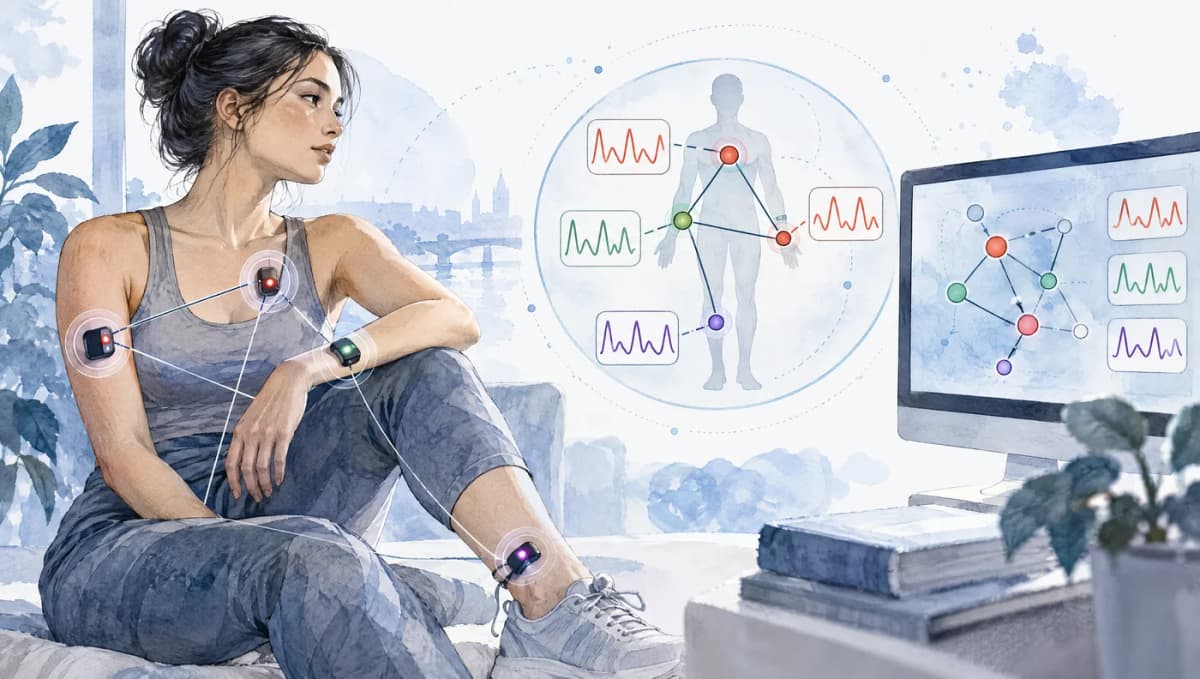
Graph neural networks represent PPG features and physiological signals as nodes in a graph, with edges encoding known or learned relationships between them. This relational structure enables GNNs to simultaneously model the local waveform properties at each measurement site and the physiological dependencies between sites, outperforming sequence models that treat PPG as isolated temporal streams.
For multi-site PPG (wrist, finger, and forehead simultaneously), or for combined PPG and ECG analysis, GNNs naturally encode the arterial propagation of the pulse wave as a graph topology. This physiologically motivated inductive bias consistently improves downstream task performance compared to architectures that ignore inter-signal relationships.
Why Graph Structure Matters for PPG
Traditional PPG processing treats each signal independently: a 1D CNN or LSTM processes the wrist PPG stream, the fingertip PPG stream, and the ECG stream as separate inputs. The relationships between them (pulse transit time between wrist and finger, the correspondence between ECG QRS and PPG systolic peak, the common respiratory modulation of all signals) are only implicitly captured through concatenated features or attention mechanisms.
GNNs make these relationships explicit. A node represents a signal channel or extracted feature; an edge represents a known or learned physiological relationship. Message passing propagates information along edges, allowing each node's representation to be contextualized by its neighbors.
This matters most for:
- Pulse wave analysis across sites: PWV computation from multi-site PPG is a graph propagation problem: the pulse travels from heart to wrist to finger with fixed physiological relationships
- Sensor fusion: Combining PPG, ECG, accelerometer, and temperature into a unified physiological state estimate
- Multi-lead cardiac monitoring: Graph over 12 ECG leads + 3 PPG sites models the cardiac electro-mechanical relationship
Graph Construction for Multi-Site PPG
Predefined physiological graph: Edges are constructed from known anatomical and physiological relationships. For cardiovascular signals:
- Wrist PPG and finger PPG: edge weight = (pulse transit time between sites)
- PPG and ECG: edge weight = 1 / PEP (pre-ejection period)
- PPG at symmetric sites (left/right wrist): edge weight = Pearson correlation of waveforms
This approach encodes domain knowledge directly into the graph structure. The limitation is that it requires prior knowledge of relationships and may not capture task-specific dependencies.
Learned graph topology: Rather than fixing the graph structure, learn it from data. Methods like MTGNN (Wu et al., 2020) simultaneously learn a sparse adjacency matrix and a GNN model that exploits it. For PPG, the learned graph may discover unexpected dependencies: cross-temporal correlations between non-adjacent cardiac cycles, relationships between respiratory modulation of PPG and peripheral vasoconstriction, or demographic-stratified connectivity patterns.
Dynamic graph: For non-stationary physiological signals, the optimal graph structure changes over time. During exercise, the physiological correlations between PPG sites change differently than during sleep. Dynamic graph networks update edge weights at each time step based on current signal properties.
GNN Architectures for PPG Classification
Graph Convolutional Networks (GCN) aggregate features from each node's neighbors weighted by the adjacency matrix. For a physiological signal graph with N nodes (N measurement sites or extracted features), GCN performs:
where is the adjacency matrix (with added self-loops), is the degree matrix, is the feature matrix at layer , and is the trainable weight matrix.
For multi-site PPG, each node embedding is the CNN-extracted feature vector from that PPG channel. After 2-3 GCN layers, each node's representation incorporates information from all connected physiological signals.
Graph Attention Networks (GAT) replace fixed adjacency weights with learned attention weights, allowing the model to dynamically weigh neighbor contributions. For PPG physiological graphs, GAT attention weights learn to focus on the most informative inter-signal relationships for each prediction task.
Temporal Graph Networks for PPG Sequences
Extending GNNs to temporal signals produces Temporal Graph Networks (TGN) or Spatio-Temporal Graph Convolutional Networks (ST-GCN), which model both temporal dynamics within each node and spatial relationships between nodes simultaneously.
For PPG, ST-GCN processes a 3D tensor (time × nodes × features):
- Temporal convolution: 1D convolution along the time axis for each node, capturing waveform dynamics
- Spatial (graph) convolution: GCN along the node axis for each time step, capturing inter-signal relationships
- Interleaved layers: Alternating temporal and spatial convolution, or factored joint temporal-spatial convolution
On a 5-site PPG dataset (wrist, finger, earlobe, forehead, toe) combined with ECG, ST-GCN for blood pressure estimation achieves systolic BP MAE of 6.8 mmHg versus 8.1 mmHg for an equivalent CNN that ignores inter-signal relationships.
Knowledge Graph-Augmented PPG Analysis
Beyond sensor fusion, GNNs can incorporate medical knowledge graphs into PPG analysis. A heterogeneous knowledge graph might include:
- Condition nodes: AF, PAD, heart failure, sleep apnea
- Feature nodes: Irregular IBI, prolonged QT, reduced augmentation index, high LF/HF ratio
- Relationship edges: "irregular IBI is diagnostic of AF", "reduced augmentation index is associated with arterial stiffness", "HRV is reduced in heart failure"
A knowledge-augmented GNN for PPG classification first extracts feature nodes from the raw PPG signal, then applies graph convolution over the combined feature and condition graph. This allows the model to leverage established clinical knowledge about feature-disease relationships even when training data is limited.
Practical Implementation Considerations
Graph library: PyTorch Geometric (PyG) and DGL (Deep Graph Library) both support the GCN, GAT, and ST-GCN architectures needed for PPG graph learning. PyG's DataLoader handles variable-size graphs (different numbers of measurement sites across subjects).
Node feature initialization: For raw waveform nodes, initialize node features with a 1D CNN applied to each signal independently. Encoder sharing (one CNN shared across all nodes with the same signal type) reduces parameters and enforces representation consistency.
Edge feature learning: For temporal graphs, edge features can encode the time lag between nodes (e.g., PTT between PPG sites). These edge features are incorporated via edge-conditioned convolution (ECC) or attention edge features in GAT.
Handling missing nodes: Not every subject will have all measurement sites available. Graph architectures handle missing nodes gracefully by excluding them from the adjacency matrix, making GNNs more robust to sensor dropout than fixed-dimension concatenation approaches.
For related content, see PPG multi-site measurement, PPG multi-channel processing, PPG deep learning heart rate estimation, and PPG transformer models. For physiological context on pulse wave propagation, see PPG vascular age assessment.
Key Papers
- Kipf, T.N. & Welling, M. (2017). Semi-supervised classification with graph convolutional networks. ICLR. https://doi.org/10.48550/arXiv.1609.02907
- Veličković, P. et al. (2018). Graph attention networks. ICLR. https://doi.org/10.48550/arXiv.1710.10903
- Wu, Z. et al. (2020). Connecting the dots: Multivariate time series forecasting with graph neural networks. KDD. https://doi.org/10.1145/3394486.3403118
FAQ
When should I use a GNN instead of a Transformer for multi-site PPG? GNNs are preferred when the graph structure is known or partially known (e.g., physiological propagation relationships between sites) and when the number of nodes is large but sparsely connected. Transformers with cross-attention can approximate GNNs through dense attention over all pairs of signal segments, but without the inductive bias of physiological graph structure. For 2-4 sites, the difference is modest. For 10+ sites or complex heterogeneous signal fusion, GNNs with physiologically motivated adjacency are typically more sample-efficient.
How do GNNs handle the heterogeneity of PPG signals from different sensor types? Heterogeneous graph networks assign different node types to different sensor categories (optical PPG, electrical ECG, inertial IMU) and use type-specific linear projections to map each sensor's features to a shared embedding space before graph convolution. This handles frequency range differences, amplitude scale differences, and modality-specific artifacts without manual feature engineering.
Can GNNs be used for single-site PPG monitoring without the multi-site advantage? Yes. For single-site PPG, the graph structure can be defined over extracted features (each waveform feature is a node, with edges based on feature correlation or physiological co-occurrence). This feature graph approach enables GNNs to learn relationships between features (e.g., augmentation index is strongly related to diastolic notch position) that flat feature vectors miss. However, the advantage over Transformers is smaller for single-site applications.
What is the computational cost of adding GNN layers to a PPG model? For small graphs (5-20 nodes), GCN and GAT layers add minimal overhead: one or two matrix multiplications over the small graph. Total model parameter increase is typically 5-15%. Inference latency on Cortex-M7 class hardware increases by less than 5 ms per GCN layer for graphs with < 20 nodes. This makes physiological graph modeling practical for wearable deployment.
Are there public multi-site PPG datasets suitable for GNN training? Several public datasets include multi-site physiological recordings suitable for GNN approaches: MIMIC-III (fingertip PPG + ECG), the BIDMC dataset (wrist PPG + fingertip PPG + ECG), and PhysioNet's multi-parameter ICU database. Purpose-built multi-site wrist-finger-forehead PPG datasets are rarer but exist in the vascular research literature.
Related articles
Neural Architecture Search for PPG Processing on Wearable Devices
How Neural Architecture Search discovers optimal PPG processing networks for wearables, balancing accuracy with latency and power constraints on edge hardware.
PPG Sleep Fragmentation Biomarkers: What Optical Pulse Signals Reveal About Broken Sleep
PPG sleep fragmentation biomarkers use pulse timing, amplitude, and autonomic surges to estimate broken sleep, arousals, and sleep continuity loss.
PPG Orthostatic Hypotension Detection: Can Optical Pulse Signals Catch a Standing BP Drop?
PPG orthostatic hypotension detection uses beat-to-beat pulse changes to flag standing blood pressure drops, offering screening value but not a cuffless diagnosis.
PPG Nocturnal Blood Pressure Dipping: Can Optical Signals Approximate Overnight BP Patterns?
PPG nocturnal blood pressure dipping analysis uses overnight pulse features to approximate dipping patterns, a useful screening concept with clear limits.
PPG and Virtual Reality Biofeedback: Real-Time Physiological Adaptation in Immersive Environments
PPG sensors integrated with virtual reality systems enable real-time physiological biofeedback loops where the virtual environment adapts to the user'...
Temporal Convolutional Networks for PPG: Why TCNs Still Matter
Temporal convolutional networks give PPG teams a strong alternative to transformers by modeling long waveform context with causal or dilated convolutions, lower compute, and stable training on wearable signals.