Simultaneous Multi-Site PPG Measurement: Techniques, Applications & Pulse Transit Time
**Simultaneous PPG measurement at multiple body sites unlocks physiological parameters that are fundamentally inaccessible from a single measurement l...
- PPG & Signal Processing
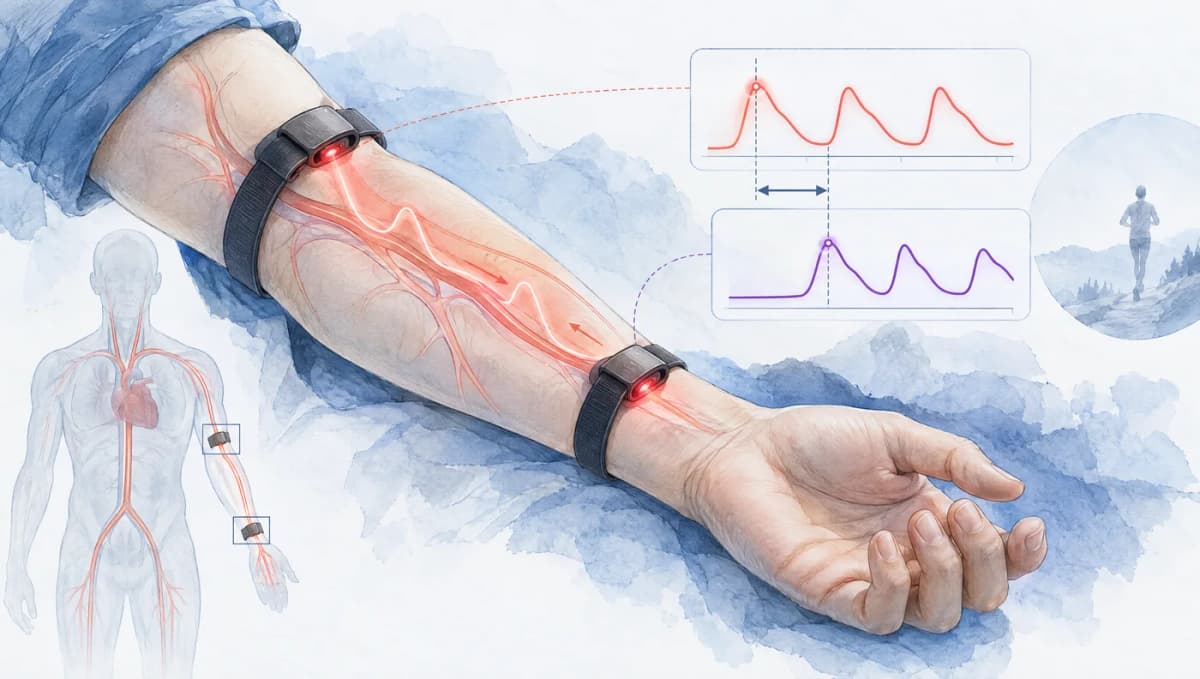
Simultaneous PPG measurement at multiple body sites unlocks physiological parameters that are fundamentally inaccessible from a single measurement location, most notably pulse transit time and pulse wave velocity for cuffless blood pressure estimation. While a single PPG sensor captures local blood volume changes, the temporal relationship between PPG waveforms at different anatomical locations encodes information about arterial stiffness, vascular tone, and central hemodynamics that no amount of signal processing can extract from a single-site recording.
This article provides a comprehensive technical treatment of multi-site PPG measurement, covering synchronization requirements, sensor placement strategies, pulse transit time estimation, and clinical applications. For foundational PPG concepts, see our introduction to PPG technology. For how multi-site PPG relates to blood pressure estimation, see our PPG blood pressure estimation methods guide.
Physiological Basis for Multi-Site PPG
The Arterial Pulse Wave
Each cardiac contraction generates a pressure wave that propagates from the aortic root through the arterial tree to peripheral vessels. This pulse wave travels at a finite velocity, pulse wave velocity (PWV), which is determined by the mechanical properties of the arterial wall and the blood pressure distending it. The Moens-Korteweg equation describes this relationship:
where is the elastic modulus of the arterial wall, is wall thickness, is vessel radius, and is blood density. Because increases with distending pressure (due to the nonlinear stress-strain relationship of arterial tissue), PWV increases with blood pressure. This fundamental relationship is the basis for PTT-based cuffless blood pressure estimation.
Aortic PWV is lowest in healthy young adults and rises with age and arterial stiffening. Peripheral PWV in muscular arteries is generally higher than in the elastic aorta, reflecting the different elastic properties of peripheral versus central arteries (see the expert consensus by Laurent et al., 2006; doi:10.1093/eurheartj/ehl254).
What Multi-Site PPG Captures
A PPG sensor at each measurement site records the local arterial pulse wave arrival. The time delay between pulse arrivals at two sites, the pulse transit time (PTT), is related to PWV by:
where D is the arterial path length between the two measurement sites. Since PWV is related to blood pressure through arterial mechanics, PTT provides an indirect measure of blood pressure changes.
Beyond PTT, multi-site PPG also captures:
Pulse waveform morphology differences between central and peripheral sites, reflecting wave reflection patterns and local vascular compliance. The PPG waveform at the finger is more peaked and has a more prominent dicrotic notch than the waveform at the earlobe, due to impedance mismatch-driven wave reflections in the peripheral vasculature. For more on dicrotic notch analysis, see our dicrotic notch detection guide.
Perfusion asymmetry between bilateral sites (left vs. right), which can indicate peripheral vascular disease, thoracic outlet syndrome, or subclavian steal syndrome. Allen and Murray (2000) (doi:10.1088/0967-3334/21/3/303) recorded PPG simultaneously from both ears, thumbs, and big toes in 40 healthy subjects and found right-left pulse shapes highly similar (median correlation coefficients above 0.98 at all three levels). This baseline symmetry is what makes left-right differences diagnostically interesting.
Regional vascular reactivity differences during physiological challenges such as cold pressor test, Valsalva maneuver, or reactive hyperemia. Multi-site PPG enables simultaneous assessment of vascular responses at different vascular beds.
Measurement Site Selection
Signal Quality Considerations
PPG signal quality varies substantially across body sites, driven by differences in superficial blood perfusion, tissue thickness, melanin content, and venous pooling. The choice of measurement sites for multi-site PPG must balance signal quality against arterial path length and practical wearability.
Fingertip: The gold standard for PPG signal quality. The fingertip has the highest density of arteriovenous anastomoses in the body, producing AC/DC ratios of 2-5% in transmittance mode. Both transmittance and reflectance modes work well. Limitations include susceptibility to cold-induced vasoconstriction (which can reduce signal amplitude by >90%) and impracticality for continuous wearable monitoring.
Earlobe: Excellent signal quality (AC/DC ratio 1-3%) with low motion artifact susceptibility during seated measurements. Transmittance mode works well due to the thin tissue. The earlobe is less affected by sympathetic vasoconstriction than the finger, providing more stable measurements during stress. Practical for clinical monitoring but less suitable for consumer wearables.
Forehead: Good signal quality (AC/DC ratio 1-2%) with minimal vasoconstriction effects because the supraorbital and supratrochlear arteries are branches of the internal carotid, which has limited sympathetic innervation. Reflectance mode is used. Forehead PPG is used in clinical settings for patients with poor peripheral perfusion.
Wrist: Moderate signal quality (AC/DC ratio 0.5-2%) with significant motion artifact challenges. Reflectance mode with green LEDs is standard. The radial artery provides a pulsatile source, but the relatively thick overlying tissue and variable sensor-skin contact make wrist PPG noisier than fingertip or earlobe measurements. See our motion artifact removal guide for techniques to address this.
Toe: Similar signal quality to the fingertip but more susceptible to peripheral vascular disease effects. The toe provides the longest arterial path length from the heart, making it valuable as the distal site in PTT measurements.
Optimizing Arterial Path Length
For PTT-based measurements, the arterial path length between sites directly affects measurement precision. Longer paths produce larger PTT values, reducing the relative impact of timing errors.
Finger-to-toe: Path length approximately 1.5 m. PTT values of 150-300 ms. This provides the best temporal resolution for PTT measurement and is the standard configuration in vascular research.
Finger-to-ear (or finger-to-forehead): Path length approximately 0.8-1.0 m. PTT values of 50-150 ms. This is the most common configuration in clinical PTT studies because both sites have high signal quality and the subject can remain seated.
Wrist-to-finger (ipsilateral): Path length only 0.15-0.25 m. PTT values of 15-40 ms. The short path length makes accurate PTT measurement extremely challenging, requiring sub-millisecond synchronization. This configuration is primarily of interest for single-arm wearable devices but has limited practical utility for blood pressure estimation.
Synchronization Requirements and Methods
Timing Accuracy Requirements
The required synchronization accuracy depends on the target application and the PTT values being measured. For PTT-based blood pressure estimation, PTT changes by only a few milliseconds over clinically relevant blood pressure changes, so timing errors of even a millisecond between sites translate into meaningful blood pressure error.
For aortic PWV estimation using finger-to-toe PTT, the typical PWV change of 1 m/s corresponds to a PTT change of approximately 20-40 ms over the 1.5 m path length. This relaxes the synchronization requirement to approximately 2-5 ms for clinically meaningful PWV resolution.
Hardware Synchronization
The most reliable synchronization approach uses a shared hardware clock or trigger signal between PPG AFE channels. Modern multi-channel AFEs such as the MAX86141 (2 channels) and ADPD4101 (8 input channels) provide inherent synchronization between channels because all channels share a single clock and sampling sequencer. When both PPG sensors connect to the same AFE, synchronization is exact to within the ADC conversion time (typically 1-10 us).
For sensors connected to separate AFEs on separate devices (e.g., a wrist device and an ear clip), hardware synchronization requires a wired trigger line or wireless trigger with deterministic latency. A GPIO trigger pulse from one device to the other can achieve synchronization better than 1 us when properly implemented.
Software Synchronization
When hardware connections between devices are impractical, software-based time synchronization is necessary. Several approaches are used:
Bluetooth timestamp synchronization: BLE time synchronization achieves typical accuracy of 1-5 ms, which is marginal for PTT applications on short arterial paths but adequate for finger-to-toe measurements. The precision depends heavily on the BLE stack implementation, connection interval, and whether the devices support the BLE Isochronous Channels feature introduced in Bluetooth 5.2.
Cross-correlation-based alignment: Rather than relying on absolute time synchronization, the PPG signals from both sites can be aligned using cross-correlation to find the optimal time delay. This approach is robust to clock drift and eliminates the need for precise time synchronization, but it assumes a specific model for the expected waveform delay (typically that the two waveforms have similar morphology, which is only approximately true between central and peripheral sites).
Network time protocols: For laboratory setups using wired connections, IEEE 1588 Precision Time Protocol (PTP) can synchronize devices to within 1 us over Ethernet. This is the standard approach for research-grade multi-site PPG systems.
Pulse Transit Time Estimation Algorithms
Feature-Based PTT Estimation
The traditional approach to PTT estimation identifies characteristic features (fiducial points) on each PPG waveform and calculates the time difference between corresponding features at the two sites.
Foot of the pulse wave: The pulse foot, defined as the point of maximum acceleration at the onset of the systolic upstroke, is the most commonly used fiducial point. It corresponds most closely to the actual arrival of the pressure wave front. Detection methods include the intersecting tangent method (drawing tangent lines on the diastolic trough and systolic upstroke and finding their intersection) and the second derivative maximum (the point of maximum positive acceleration in the waveform).
Peak of the pulse wave: The systolic peak is the easiest feature to detect but is influenced by wave reflection timing and local vascular compliance, making it a less pure measure of pulse wave arrival time. Peak-based PTT includes both the transit time and the local pulse wave buildup time, introducing a site-dependent offset.
Maximum slope (dP/dt max): The point of maximum rate of rise on the systolic upstroke. This feature is less sensitive to wave reflection effects than the peak and more robust to baseline wander than the foot. It represents a compromise between the theoretical purity of the foot and the detection reliability of the peak. For deeper analysis of PPG waveform derivatives, see our second derivative analysis guide.
Waveform-Based PTT Estimation
Instead of extracting discrete features, waveform-based approaches estimate PTT from the overall shape relationship between the two PPG signals.
Cross-correlation: Computing the cross-correlation function between windowed segments of the two PPG signals and finding the lag at maximum correlation. This provides a robust PTT estimate that averages over the entire waveform rather than relying on a single feature. The temporal resolution is limited by the sampling rate (typically 0.01-0.04 ms at 25-100 Hz) but can be improved with parabolic interpolation around the correlation peak.
Phase difference in the frequency domain: Computing the phase of the cross-spectral density between the two signals at the cardiac fundamental frequency. This approach naturally provides sub-sample temporal resolution and is robust to noise, but assumes that the phase relationship is linear across the cardiac frequency band (which is approximately true for PTT but breaks down if the waveform morphology differs substantially between sites).
Gao et al. (2016) (doi:10.14814/phy2.12768) compared noninvasive PTT estimates against invasively measured PTT in swine over a wide blood pressure range. PTT between two PPG waveforms correlated well with all blood pressure levels (group average R² 0.81-0.85, not significantly different from invasive PTT), whereas ECG-to-PPG pulse arrival time correlated less well (best R² 0.70, for systolic BP) because it includes the pre-ejection period. This supports measuring true PTT between two PPG sites rather than using the ECG R-peak as the proximal marker.
Clinical Applications
Cuffless Blood Pressure Estimation
The primary clinical driver for multi-site PPG research is cuffless blood pressure monitoring. The inverse relationship between PTT and blood pressure is well established, though its strength varies across studies, individuals, and conditions (see the review by Mukkamala et al., 2015).
The current state of the art for PPG-PPG PTT blood pressure estimation achieves mean absolute errors of 5-10 mmHg for systolic and 4-7 mmHg for diastolic pressure in controlled laboratory studies. However, several challenges limit clinical adoption:
Calibration requirement: The PTT-BP relationship varies between individuals due to differences in arterial path length, vascular compliance, and autonomic tone. Individual calibration against a reference cuff measurement is necessary, typically using a linear or logarithmic model: BP = a * PTT + b or BP = a * ln(PTT) + b.
Calibration drift: The calibration parameters drift over time due to changes in vascular tone, hydration status, and long-term arterial remodeling. Recalibration is typically needed every 1-4 weeks, which limits the practical utility of continuous monitoring. For a broader discussion of cuffless blood pressure challenges, see our cuffless blood pressure guide.
Arterial Stiffness Assessment
Aortic PWV is an independent predictor of cardiovascular mortality and is recommended by ESH/ESC guidelines for cardiovascular risk stratification. Reference values for carotid-femoral PWV are well established: an expert consensus recommends 10 m/s as the cut-off for carotid-femoral PWV (Van Bortel et al., 2012; doi:10.1097/HJH.0b013e32834fa8b0).
Multi-site PPG provides a noninvasive, operator-independent alternative to tonometry-based PWV measurement. Finger-to-toe PPG PWV has been studied as a surrogate for carotid-femoral PWV, the gold standard. The main limitation is that the finger-to-toe path includes both elastic central arteries and stiff muscular peripheral arteries, making the measured PWV a composite value that does not directly correspond to aortic stiffness.
Peripheral Vascular Disease Screening
Bilateral multi-site PPG at symmetric body sites (left vs. right fingers, left vs. right toes) can detect vascular asymmetry indicative of peripheral arterial disease (PAD). Because left and right pulses are highly similar in healthy people (Allen and Murray, 2000), PPG-based detection of peripheral vascular disease is one of the clinical applications reviewed by Allen (2007) (doi:10.1088/0967-3334/28/3/R01). See our peripheral artery disease guide for diagnostic-accuracy evidence.
The advantage of PPG over the traditional ankle-brachial index (ABI) is that PPG can be performed as a continuous, unattended measurement rather than requiring a trained operator with a Doppler probe and sphygmomanometer. Multi-site PPG waveform analysis also provides additional information about the severity and location of stenosis through wave reflection timing analysis.
Practical Implementation Considerations
Multi-Channel Data Acquisition
For research-grade multi-site PPG systems, simultaneous acquisition of 2-8 PPG channels plus accelerometer and ECG reference channels is common. Key hardware considerations include:
Sampling rate matching: All PPG channels should be sampled at the same rate and ideally from the same clock domain. Mismatched sampling rates require resampling, which introduces interpolation error that directly affects PTT accuracy.
Channel crosstalk: When multiple PPG sensors are close together (e.g., multi-wavelength sensors on adjacent fingers), optical crosstalk between LED sources can corrupt the signals. Sequential LED driving (time-division multiplexing) eliminates optical crosstalk at the cost of a small timing offset between channels (typically 0.1-1 ms, which is negligible for most applications).
Ambient light rejection: Each measurement site may have different ambient light conditions, requiring independent ambient light cancellation for each channel. This is handled automatically by most multi-channel AFEs through correlated double sampling on each channel independently.
ECG-PPG vs. PPG-PPG Transit Time
An important distinction in the literature is between ECG-derived pulse arrival time (PAT) and PPG-PPG pulse transit time (PTT). PAT, measured as the delay between the ECG R-wave and a peripheral PPG feature, includes both the pre-ejection period (PEP, the isovolumetric contraction time of the left ventricle, typically 30-80 ms) and the actual pulse transit time. PEP varies with cardiac contractility, preload, and afterload, introducing a confounding variable that degrades the PAT-BP correlation.
PPG-PPG PTT, measured between two peripheral PPG sites, largely eliminates the PEP component because both sites are downstream of the aortic valve. This makes PPG-PPG PTT a purer measure of pulse wave velocity and, theoretically, a better surrogate for blood pressure. However, PPG-PPG PTT requires two wearable sensors rather than the single sensor plus ECG electrode combination used for PAT measurement.
Conclusion
Multi-site PPG measurement extends the clinical and research utility of photoplethysmography far beyond what is possible with a single sensor, enabling assessment of arterial stiffness, blood pressure tracking, and peripheral vascular disease screening. The critical technical challenges are sensor synchronization (sub-millisecond for PTT applications), robust fiducial point detection for accurate PTT estimation, and individual calibration for blood pressure applications. As wearable form factors mature and multi-device synchronization improves, multi-site PPG has the potential to bring continuous, cuffless hemodynamic monitoring from the research laboratory to routine clinical practice. For engineers building multi-site PPG systems, careful attention to the signal processing pipeline and power management is essential for practical implementation.
References
- Laurent, S., et al. (2006). Expert consensus document on arterial stiffness: methodological issues and clinical applications. European Heart Journal, 27(21), 2588-2605. https://doi.org/10.1093/eurheartj/ehl254
- Allen, J., & Murray, A. (2000). Similarity in bilateral photoplethysmographic peripheral pulse wave characteristics at the ears, thumbs and toes. Physiological Measurement, 21(3), 369-377. https://doi.org/10.1088/0967-3334/21/3/303
- Allen, J. (2007). Photoplethysmography and its application in clinical physiological measurement. Physiological Measurement, 28(3), R1-R39. https://doi.org/10.1088/0967-3334/28/3/R01
- Mukkamala, R., et al. (2015). Toward ubiquitous blood pressure monitoring via pulse transit time: theory and practice. IEEE Transactions on Biomedical Engineering, 62(8), 1879-1901. https://doi.org/10.1109/TBME.2015.2441951
- Gao, M., Olivier, N. B., & Mukkamala, R. (2016). Comparison of noninvasive pulse transit time estimates as markers of blood pressure using invasive pulse transit time measurements as a reference. Physiological Reports, 4(10), e12768. https://doi.org/10.14814/phy2.12768
- Van Bortel, L. M., et al. (2012). Expert consensus document on the measurement of aortic stiffness in daily practice using carotid-femoral pulse wave velocity. Journal of Hypertension, 30(3), 445-448. https://doi.org/10.1097/HJH.0b013e32834fa8b0
Related articles
Pulse Transit Time from PPG for Cuffless BP
How pulse transit time (PTT) from PPG tracks blood pressure without a cuff: PTT vs PAT, calibration, sensor sites, and where validation stands today.
PPG Vascular Age Assessment: Arterial Stiffness Measurement from Pulse Wave Analysis
**Arterial stiffness is one of the earliest detectable markers of cardiovascular disease, and the PPG waveform encodes surprisingly rich information a...
Pulse Wave Velocity Measurement Methods: Equipment, Protocols, and PPG-Based Approaches
Compare pulse wave velocity measurement methods including carotid-femoral, brachial-ankle, and PPG-based PWV with equipment, accuracy, and protocol details.
Pulse Wave Analysis Using PPG: Waveform Features, Vascular Health, and Clinical Applications
Complete guide to pulse wave analysis from PPG signals. Covers augmentation index, stiffness index, derivatives, fiducial points, and vascular assessment.
PPG in Affective Computing: Applications from Gaming to Therapy
Survey of PPG-based affective computing applications covering emotion-adaptive gaming, mental health monitoring, human-robot interaction, and biofeedback therapy with accuracy benchmarks.