Multi-Wavelength PPG Signal Fusion: Algorithms for Multi-Channel Processing
**Multi-wavelength PPG signal fusion exploits the fundamental principle that different light wavelengths interact with tissue and blood through distin...
- PPG & Signal Processing
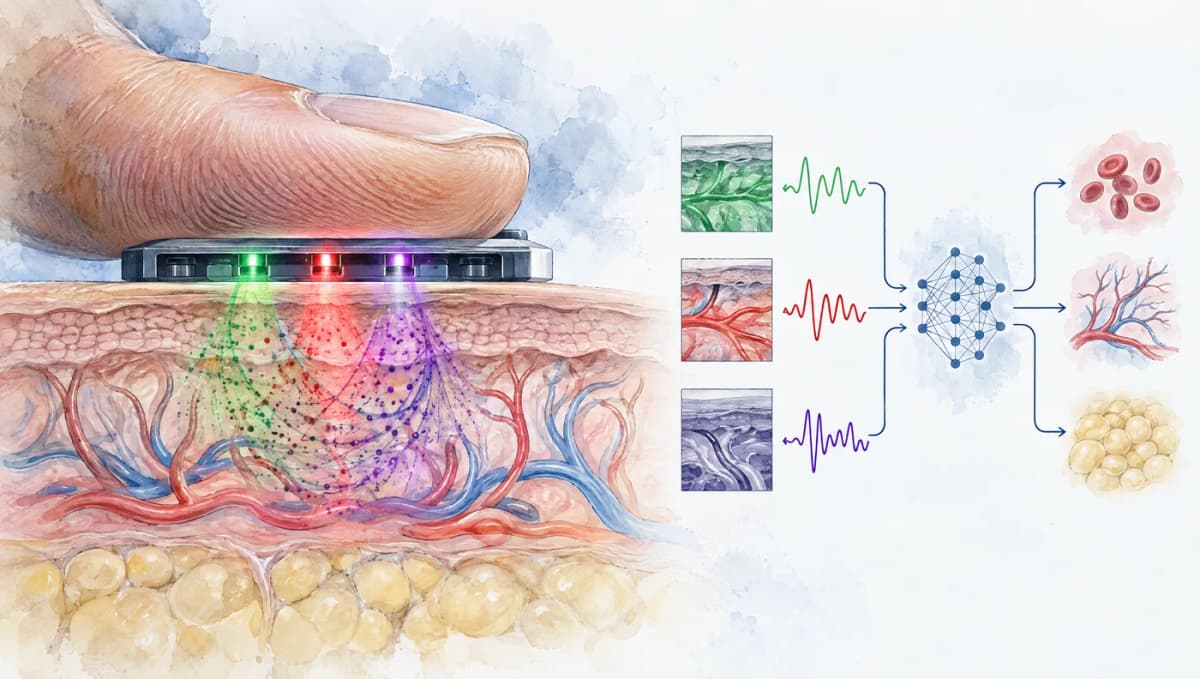
Multi-wavelength PPG signal fusion exploits the fundamental principle that different light wavelengths interact with tissue and blood through distinct physical mechanisms, providing complementary information that no single wavelength can capture alone. By combining signals from two or more wavelengths, multi-channel PPG systems can simultaneously measure multiple physiological parameters (heart rate, SpO2, hemoglobin variants), improve motion artifact robustness through spectral diversity, and reduce measurement bias across diverse skin pigmentation.
This guide covers the physics of multi-wavelength tissue interaction, sensor array design considerations, classical and modern fusion algorithms, and the practical tradeoffs of multi-channel PPG systems. For the foundational physics of individual wavelength behavior, see our green vs. red vs. infrared PPG wavelength guide.
Physics of Multi-Wavelength Tissue Interaction
Wavelength-Dependent Optical Properties
The optical behavior of biological tissue varies dramatically across the PPG-relevant spectrum (400-1000 nm). Three tissue properties determine the detected signal at each wavelength: absorption, scattering, and penetration depth.
Absorption is dominated by hemoglobin (oxy- and deoxy-), melanin, water, and lipids. Hemoglobin absorption peaks near 420 nm (Soret band), with secondary peaks at 540 nm and 576 nm for oxyhemoglobin. The critical diagnostic window lies between 600-1000 nm, where oxyhemoglobin and deoxyhemoglobin absorption diverge significantly: at 660 nm, deoxyhemoglobin absorbs much more strongly than oxyhemoglobin, while at 940 nm, oxyhemoglobin absorbs more. This crossover is the basis of pulse oximetry (Tremper, 1989, doi:10.1378/chest.95.4.713).
Scattering in tissue follows an approximate inverse power law with wavelength: , where ranges from 0.5 to 2.0 depending on tissue type. Shorter wavelengths scatter more, resulting in shallower penetration and more diffuse light distribution. Jacques (2013) reviewed reported tissue optical properties and gave formulae for the wavelength dependence of scattering and absorption in generic tissue (doi:10.1088/0031-9155/58/11/R37).
Penetration depth determines which vascular structures contribute to the PPG signal. Green light at 525 nm penetrates 1-2 mm, sampling the superficial dermal capillary plexus. Red light at 660 nm penetrates 2-5 mm, reaching the deep dermal plexus. Infrared at 940 nm penetrates 5-10 mm, probing subcutaneous vessels and potentially larger arterioles. This depth stratification means that each wavelength samples a different cross-section of the vascular tree, providing structural as well as spectral diversity.
Information Content per Wavelength
Each wavelength in a multi-channel PPG system contributes unique information based on its interaction profile:
Green (520-530 nm): Highest AC amplitude at the wrist (PI typically 0.5-2.5%), strongest motion artifact susceptibility, most affected by melanin, and shallow penetration capturing superficial capillary dynamics. Best for heart rate accuracy.
Red (660 nm): Moderate AC amplitude (PI 0.1-0.8% at wrist), high sensitivity to oxygenation state (deoxy-Hb dominant absorption), moderate melanin sensitivity, and medium penetration depth. Essential for SpO2 as one half of the ratio-of-ratios.
Infrared (880-940 nm): Lower AC amplitude at wrist (PI 0.1-0.5%), complementary oxygenation sensitivity (oxy-Hb dominant absorption), minimal melanin sensitivity, and deep penetration sampling larger vessels. Essential as the second SpO2 wavelength and most equitable across skin tones.
Near-infrared (740-780 nm): Near the isosbestic point where HbO2 and Hb absorption are similar, providing oxygen-insensitive blood volume measurement. Useful as a reference channel for normalizing oxygenation-dependent wavelengths.
The combination of wavelengths at different penetration depths also provides pulse arrival time differences between vascular beds, which correlate with blood pressure and arterial stiffness, opening the door to cuffless blood pressure estimation.
Sensor Array Design
Multi-LED Architectures
Multi-wavelength PPG sensors use multiple LEDs with a shared photodetector or multiple LED-photodetector pairs. The time-division multiplexing (TDM) approach sequences LED activations so that only one LED is on at any time, and the photodetector captures each wavelength's signal in successive time slots. TDM is the dominant architecture in commercial devices because it uses a single photodetector and avoids spectral crosstalk between channels.
Typical TDM timing allocates 50-500 microseconds per LED pulse with a total cycle time of 0.5-5 ms for 2-4 wavelengths, yielding effective per-channel sampling rates of 25-100 Hz. The critical design parameter is ensuring that the time delay between wavelength samples within one cycle is small enough that the cardiac signal does not change significantly. For a 75 BPM heart rate with a systolic rise time of approximately 100 ms, a total cycle time under 5 ms introduces timing errors below 5% of the pulse amplitude, which is negligible.
The Maxim MAX86176, a widely used multi-channel PPG AFE, supports up to 6 LED wavelengths and 2 photodetectors with programmable TDM sequencing, 20-bit ADC resolution, and integrated ambient light cancellation. The Texas Instruments AFE4900 supports 4 LED channels with simultaneous ambient subtraction. These integrated AFEs have dramatically reduced the hardware complexity of multi-wavelength PPG system design.
Spatial Diversity
Beyond spectral diversity, spatial diversity -- placing multiple sensor elements at different locations on the skin -- provides additional information. Multi-site PPG captures pulse wave propagation, allowing pulse transit time (PTT) measurement between two locations without ECG synchronization. Spatially separated sensors also experience partially decorrelated motion artifacts, enabling spatial filtering to improve signal quality. The motion decorrelation occurs because different skin locations experience different mechanical coupling to the underlying tissue during motion.
Ring-form-factor sensors (such as the Oura Ring) inherently provide spatial diversity because the curved sensor geometry means that LED-photodetector pairs on opposite sides of the finger sample different tissue regions. This spatial diversity contributes to the robustly high signal quality observed in ring-based PPG compared to flat-backed watch sensors.
Classical Fusion Algorithms
Weighted Averaging
The simplest fusion approach is weighted averaging of heart rate or SpO2 estimates from each channel, with weights determined by per-channel signal quality. Channels with higher SNR or perfusion index receive higher weights:
where is the signal quality index for each channel. This approach provides robust heart rate estimation because different wavelengths experience motion artifact corruption at different severities. Green-channel motion artifact power may exceed the cardiac signal during arm swing, while the infrared channel at the same moment may retain a detectable cardiac component due to its deeper penetration below the mechanically disturbed superficial tissue.
Independent Component Analysis (ICA)
ICA treats multi-wavelength PPG signals as linear mixtures of independent source components (cardiac, motion, respiration, noise) and attempts to unmix them into separate sources. With N wavelength channels, ICA can separate up to N independent components. Two channels (e.g., green and infrared) can separate cardiac from one dominant motion source. Three or more channels enable separation of cardiac, motion, and respiratory components simultaneously.
The FastICA algorithm (Hyvarinen and Oja, 2000, doi:10.1016/S0893-6080(00)00026-5) is the most commonly used ICA variant for PPG due to its computational efficiency and cubic convergence. Applied to dual-wavelength PPG with only a few channels, FastICA converges quickly.
Kim and Yoo (2006) reduced motion artifacts in dual-wavelength PPG by combining ICA with block interleaving and low-pass filtering, exploiting the quasi-periodicity of the PPG and its independence from motion artifacts, and demonstrated the approach on synthetic and real data (doi:10.1109/TBME.2005.869784). The key assumption -- statistical independence of cardiac and motion components -- generally holds except during lock-in conditions where heart rate equals stride cadence.
Canonical Correlation Analysis (CCA)
CCA finds linear combinations of multi-channel PPG signals that maximize correlation with a reference (e.g., periodic template at the estimated heart rate) or between two sets of channels. Unlike ICA, CCA does not assume source independence but instead optimizes for correlation structure, which can be advantageous when cardiac and motion components are partially correlated.
Deep Learning Fusion
Multi-Input CNN Architectures
Deep learning approaches to multi-channel PPG fusion treat each wavelength as a separate input channel to a convolutional neural network, analogous to RGB channels in image processing. The network learns optimal feature extraction and fusion jointly from training data, without requiring explicit assumptions about signal statistics.
A typical architecture processes each wavelength through separate convolutional branches (1-3 conv layers each) that extract wavelength-specific features, then merges the branches through concatenation or element-wise addition before joint processing layers. This allows early layers to learn wavelength-specific representations while later layers learn cross-wavelength relationships.
Reiss et al. (2019) introduced the large PPG-DaLiA dataset, recorded during a wide range of activities under close to real-life conditions, and an end-to-end CNN that takes time-frequency spectra of synchronized PPG and accelerometer signals as input. On large datasets the CNN significantly outperformed classical methods, reducing mean absolute error by 31% on PPG-DaLiA and 21% on WESAD (doi:10.3390/s19143079).
Attention-Based Fusion
Attention mechanisms provide a learned, dynamic weighting scheme that allocates processing focus to the most informative wavelength at each time step. Self-attention applied across channels allows the network to model inter-wavelength dependencies, while temporal attention captures time-varying signal quality.
Transformer-based architectures for multi-channel PPG fusion are emerging in recent literature. Cross-channel attention can, in principle, learn to suppress channels with transient motion artifacts, and attention maps offer a degree of interpretability.
Multi-Parameter Extraction
Beyond SpO2: Extended Hemoglobin Species
Standard pulse oximetry with two wavelengths (red, infrared) estimates SpO2 by assuming that only two hemoglobin species (HbO2 and Hb) are present. In practice, carboxyhemoglobin (COHb, from carbon monoxide exposure) and methemoglobin (MetHb, from oxidative stress) are always present at low concentrations (typically under 2% each in healthy individuals) and absorb light at distinct wavelengths.
Measuring these additional species requires additional wavelengths because each species adds an unknown to the system of equations. The Beer-Lambert model for N hemoglobin species requires a minimum of N wavelengths to solve the system. Barker et al. (2006) evaluated an eight-wavelength Masimo pulse oximeter (Rad-57) in human volunteers with induced dyshemoglobinemia and found that it measured carboxyhemoglobin with an uncertainty of +/-2% over 0-15% and methemoglobin with an uncertainty of 0.5% over 0-12% (doi:10.1097/00000542-200611000-00008).
Accuracy of extended hemoglobin species measurement degrades rapidly with each additional parameter because the absorption spectra become increasingly collinear (poorly conditioned). Noninvasive total hemoglobin estimates, for example, are generally considered useful for trending rather than for transfusion decisions.
Pulse Wave Velocity from Multi-Depth Sensing
Multi-wavelength PPG enables estimation of pulse wave velocity (PWV) through the depth-dependent penetration of different wavelengths. Green light captures pulse arrival at the superficial capillary bed, while infrared captures arrival at deeper arterioles. The time difference between these arrival events is related to the local pulse transit time through the tissue layers.
The time differences involved are very small and this approach remains experimental, but if validated it could provide a cuff-free, single-site measurement related to arterial stiffness and support continuous blood pressure trending in wearable devices. For more on PPG-based cardiovascular assessment, see our conditions monitoring guide.
Skin Tone Equity in Multi-Wavelength Systems
The Melanin Challenge
Melanin absorption is a significant confounding factor in PPG that varies with skin pigmentation. Melanin absorption follows an approximately exponential decay with wavelength: , meaning melanin absorbs strongly at shorter wavelengths (green) and minimally at longer wavelengths (infrared).
Bent et al. (2020) tested consumer- and research-grade wearables across the full range of skin tones and found no statistically significant difference in heart rate accuracy across skin tones, but significant differences between devices and activity types, with absolute error during activity on average 30% higher than at rest (doi:10.1038/s41746-020-0226-6). Even so, signal amplitude at shorter wavelengths is reduced in darker skin, so incorporating red or infrared channels gives a system more options for individuals with higher pigmentation.
Adaptive Wavelength Selection
Multi-wavelength systems can implement adaptive wavelength selection algorithms that assess signal quality at each wavelength and preferentially use channels with the highest SNR for each individual. During initial calibration (first few minutes of wear), the system evaluates perfusion index and AC amplitude at each wavelength, builds a quality profile, and configures the fusion weights accordingly.
Fallow et al. (2013) compared 470, 520, 630, and 880 nm PPG in 23 adults of varying skin types. At rest, green (520 nm) gave greater modulation than all other wavelengths regardless of skin type, and type V skin had significantly lower modulation than other skin types; during exercise, blue and green gave higher signal-to-noise ratios than red or infrared (doi:10.1007/s10877-013-9436-7). These per-wavelength differences are what an adaptive selection scheme exploits.
Implementation Considerations
Power Budget
Each additional wavelength increases system power consumption linearly through LED drive current. A 3-wavelength system consumes approximately 3x the LED power of a single-wavelength system. For battery-constrained wearables, this creates a direct tradeoff between multi-wavelength benefits and battery life. Mitigation strategies include duty-cycling wavelengths at different rates (green at 25 Hz for continuous heart rate, red and infrared at 1 Hz for periodic SpO2 snapshots) and using compressed sensing to reduce per-channel sampling requirements.
Calibration
Multi-wavelength systems require careful calibration to account for LED wavelength tolerances (typically plus or minus 5-15 nm), photodetector spectral response variation, and optical coupling differences between channels. SpO2 accuracy is particularly sensitive to wavelength calibration: a 5 nm shift in the red LED wavelength can introduce 1-2% SpO2 error if not compensated.
Factory calibration using reference measurements at known oxygen saturations establishes the empirical ratio-of-ratios to SpO2 mapping for each device. Per-device calibration adds manufacturing cost but is essential for clinical-grade SpO2 accuracy. Research-grade systems like the Maxim MAXREFDES220 reference design include wavelength calibration coefficients in onboard memory for per-unit correction.
For engineers implementing multi-channel PPG signal processing, our algorithms reference provides detailed guidance on pipeline design and parameter tuning for multi-wavelength systems.
References
- Tremper, K. K. (1989). Pulse oximetry. Chest, 95(4), 713-715. https://doi.org/10.1378/chest.95.4.713
- Jacques, S. L. (2013). Optical properties of biological tissues: a review. Physics in Medicine and Biology, 58(11), R37-R61. https://doi.org/10.1088/0031-9155/58/11/R37
- Hyvarinen, A., & Oja, E. (2000). Independent component analysis: algorithms and applications. Neural Networks, 13(4-5), 411-430. https://doi.org/10.1016/S0893-6080(00)00026-5
- Kim, B. S., & Yoo, S. K. (2006). Motion artifact reduction in photoplethysmography using independent component analysis. IEEE Transactions on Biomedical Engineering, 53(3), 566-568. https://doi.org/10.1109/TBME.2005.869784
- Reiss, A., Indlekofer, I., Schmidt, P., & Van Laerhoven, K. (2019). Deep PPG: Large-scale heart rate estimation with convolutional neural networks. Sensors, 19(14), 3079. https://doi.org/10.3390/s19143079
- Barker, S. J., Curry, J., Redford, D., & Morgan, S. (2006). Measurement of carboxyhemoglobin and methemoglobin by pulse oximetry: a human volunteer study. Anesthesiology, 105(5), 892-897. https://doi.org/10.1097/00000542-200611000-00008
- Bent, B., Goldstein, B. A., Kibbe, W. A., & Dunn, J. P. (2020). Investigating sources of inaccuracy in wearable optical heart rate sensors. npj Digital Medicine, 3, 18. https://doi.org/10.1038/s41746-020-0226-6
- Fallow, B. A., Tarumi, T., & Tanaka, H. (2013). Influence of skin type and wavelength on light wave reflectance. Journal of Clinical Monitoring and Computing, 27(3), 313-317. https://doi.org/10.1007/s10877-013-9436-7
Related articles
PPG Motion Artifact Removal: Algorithms, Methods & Implementation Guide
A comprehensive technical guide to PPG motion artifact removal covering adaptive filtering (LMS, RLS, NLMS), ICA, EMD, wavelet decomposition, SVD, and deep learning methods. Includes algorithm comparison, pipeline design, benchmark datasets, and real-time implementation considerations.
Singular Value Decomposition (SVD) for PPG Signal Processing
**Singular Value Decomposition is one of the most powerful yet underutilized tools in PPG signal processing.** While adaptive filters and deep learnin...
Real-Time PPG Signal Processing on Microcontrollers: Embedded Implementation Guide
**Implementing real-time PPG signal processing on a microcontroller requires navigating tight constraints on compute cycles, memory, power, and latenc...
rPPG Signal Decomposition ICA
The raw pixel values of a face video contain a mixture of signals: blood volume pulsation, motion artifacts, illumination changes, skin specular refle...
rPPG Algorithms Deep Dive
Remote photoplethysmography (rPPG) extracts vital signs from video by detecting the optical signature of blood flow in facial skin. The algorithms tha...
Devices in this article
Research records with the datasets, papers and published validation results for each device.