PPG Vascular Age Assessment: Arterial Stiffness Measurement from Pulse Wave Analysis
**Arterial stiffness is one of the earliest detectable markers of cardiovascular disease, and the PPG waveform encodes surprisingly rich information a...
- PPG & Signal Processing
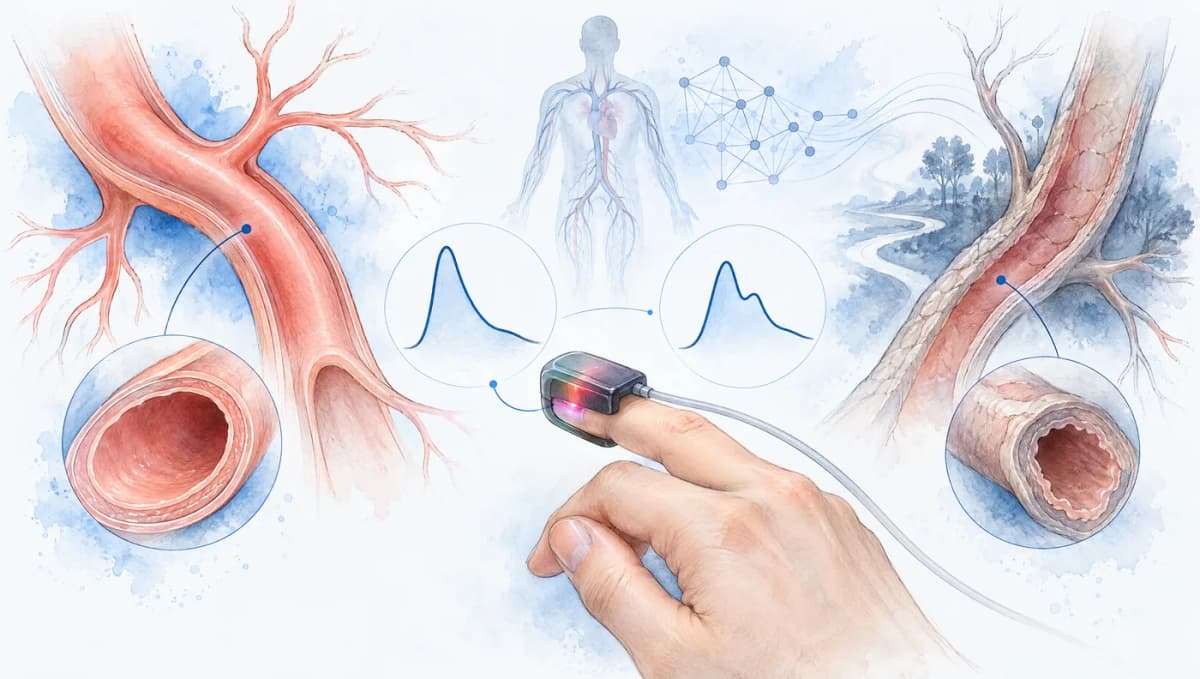
Arterial stiffness is one of the earliest detectable markers of cardiovascular disease, and the PPG waveform encodes surprisingly rich information about it. As arteries lose compliance with age, disease, or lifestyle factors, the shape of the peripheral pulse wave changes in measurable ways: the systolic peak sharpens, reflected waves arrive earlier, the dicrotic notch elevates, and the overall waveform morphology shifts. These changes can be quantified from a simple finger or wrist PPG recording, enabling non-invasive vascular age estimation without the cuff-based or tonometric equipment traditionally required.
This article covers the physiological basis of PPG-based vascular assessment, the specific waveform features that encode arterial stiffness information, validated algorithms for vascular age estimation, and the current evidence for clinical utility. For background on how PPG signals are generated, see our introduction to PPG technology.
Arterial Stiffness and the Pulse Wave
Why Arteries Stiffen
The arterial wall consists of three layers: the intima (endothelial lining), the media (smooth muscle and elastic fibers), and the adventitia (connective tissue). In healthy young arteries, the media contains a high proportion of elastin fibers that allow the vessel to expand during systole and recoil during diastole, acting as a Windkessel (compression chamber) that converts pulsatile cardiac output into more continuous peripheral flow.
With aging, elastin fibers fragment and are replaced by stiffer collagen. Advanced glycation end-products (AGEs) cross-link collagen fibers, further reducing compliance. Smooth muscle tone increases, and calcification deposits form within the media. These structural changes increase pulse wave velocity (PWV), the speed at which the pressure wave travels through the arterial tree. In reference data from 16,867 subjects across eight European countries, PWV increased with both age and blood pressure category, with the age-related rise steeper at higher blood pressures (Reference Values for Arterial Stiffness Collaboration, 2010; doi:10.1093/eurheartj/ehq165).
How Stiffness Alters the PPG Waveform
The PPG waveform at any peripheral site is the superposition of the forward-traveling pulse wave generated by ventricular ejection and backward-traveling reflected waves from impedance mismatches in the arterial tree (primarily at bifurcations and arteriolar beds). In compliant arteries, the reflected wave arrives during diastole, augmenting diastolic pressure and coronary perfusion. In stiff arteries, the reflected wave travels faster and arrives during late systole, augmenting systolic pressure and altering the waveform morphology.
This fundamental mechanism produces several quantifiable changes in the PPG pulse contour:
- Earlier reflected wave arrival: The diastolic peak moves closer to the systolic peak, reducing the peak-to-peak time interval.
- Increased augmentation: The reflected wave adds to systolic pressure, creating a shoulder or secondary peak on the systolic upstroke.
- Dicrotic notch elevation: The notch between systolic and diastolic components becomes shallower and may disappear entirely in very stiff arteries.
- Narrower pulse width: The overall pulse wave narrows as propagation velocity increases.
- Steeper systolic upstroke: Reduced arterial buffering produces a more abrupt rise to peak systole.
Understanding these waveform changes is essential for the PPG signal processing algorithms used in vascular assessment.
PPG-Derived Arterial Stiffness Indices
Stiffness Index (SI)
The stiffness index, introduced by Millasseau et al. (2002) (doi:10.1042/cs1030371), is defined as body height divided by the time delay between the systolic peak and the diastolic peak (or inflection point) of the finger PPG waveform:
where delta_T is the peak-to-peak time in seconds and height is in meters, yielding SI in m/s. This metric provides a surrogate for aortic PWV because the time delay between the systolic and diastolic peaks reflects the transit time of the pulse wave from the heart to the peripheral reflection site and back. Millasseau et al. reported a correlation of r = 0.65 (p < 0.0001) between finger-derived SI and carotid-femoral PWV measured by applanation tonometry in 87 subjects aged 21-68, with a week-to-week within-subject coefficient of variation of 9.6% for SI.
Typical SI values range from 5-7 m/s in healthy young adults (age 20-30) to 10-15 m/s in older adults (age 60-80). Values exceeding age-matched reference ranges suggest accelerated vascular aging.
Augmentation Index (AIx)
The augmentation index quantifies the contribution of the reflected wave to the systolic peak. In PPG, AIx is typically calculated from the second derivative of the waveform (the acceleration plethysmogram, APG) or from the first derivative:
where P1 is the early systolic peak (forward wave) and P2 is the late systolic peak or shoulder (reflected wave). Negative AIx values indicate that the reflected wave arrives after the systolic peak (young, compliant arteries), while positive values indicate systolic augmentation (stiff arteries).
In 524 hypertensive patients, Bortolotto et al. (2000) found that a related PPG augmentation index (the ratio of the late to the early systolic peak) was independently influenced by age and systolic blood pressure (doi:10.1016/S0895-7061(99)00192-2). However, AIx is also influenced by heart rate, peripheral vascular resistance, and vasoactive substances, requiring careful interpretation.
Second Derivative (APG) Indices
The second derivative of the PPG waveform, known as the acceleration plethysmogram (APG), decomposes the pulse wave into five characteristic waves labeled a, b, c, d, and e. Ratios of these wave amplitudes provide robust indices of vascular aging:
- b/a ratio: The most studied APG index, reflecting large artery stiffness. The b/a ratio becomes less negative (increases toward zero) with increasing arterial stiffness. Takazawa et al. (1998) studied 600 subjects and found that b/a increased with age (doi:10.1161/01.HYP.32.2.365).
- c/a ratio: Reflects the positive component of the reflected wave. Decreases with age.
- d/a ratio: Reflects late systolic wave dynamics. Decreases with age.
- e/a ratio: Related to diastolic properties. Shows variable age relationships.
- AGI (Aging Index): Defined as (b - c - d - e) / a, this composite index integrates all five wave components and correlated with age at r = 0.80 in Takazawa's 600-subject study. In 524 hypertensives, it was higher in patients with atherosclerotic alterations, although carotid-femoral PWV reflected age, blood pressure, and atherosclerosis better (Bortolotto et al., 2000; doi:10.1016/S0895-7061(99)00192-2).
The second-derivative indices also track the reflected wave itself. In 39 patients, Takazawa et al. (1998) found that the negative d/a ratio correlated with the plethysmographic augmentation index (r = 0.79) and with the invasively measured ascending aortic augmentation index (r = 0.80), and the aging index was higher in subjects with a history of diabetes, hypertension, hypercholesterolemia, or ischemic heart disease than in age-matched subjects without such a history.
These indices can be extracted from the PPG algorithms described in our technical documentation.
Reflection Index (RI)
The reflection index is the ratio of the diastolic peak amplitude to the systolic peak amplitude:
RI decreases with increasing arterial stiffness because the reflected wave, arriving earlier, merges with the systolic peak rather than forming a distinct diastolic peak. RI is generally less discriminative than SI or APG indices when used alone but is valuable as part of multi-feature models.
Machine Learning Approaches to Vascular Age Estimation
Feature-Based Models
Modern vascular age estimation goes beyond individual indices to combine multiple PPG features using machine learning. Typical feature sets include:
Time-domain features (15-25 features):
- Crest time (time from pulse onset to systolic peak)
- Pulse width at 25%, 50%, and 75% of amplitude
- Systolic and diastolic peak times
- Dicrotic notch time and amplitude
- Inter-beat interval and its variability
- Pulse area ratios (systolic area / diastolic area)
Frequency-domain features (5-10 features):
- Fundamental frequency amplitude
- Harmonic amplitude ratios (2nd/1st, 3rd/1st)
- Spectral centroid and bandwidth
- Power spectral density slope
Second derivative features (5-10 features):
- APG wave ratios (b/a, c/a, d/a, e/a)
- Aging index variants
- Zero-crossing intervals
Dall'Olio et al. (2020) (doi:10.1038/s41598-020-76816-6) used smartphone PPG from the crowd-sourced Heart for Heart dataset to predict healthy vascular aging. Ridge-penalized regression applied to 38 extracted features found that just two features, the a wave of the second-derivative PPG and tpr, plus sex, height, weight, and smoking, achieved an AUC of 94.7%.
Deep Learning Models
Several groups have applied deep learning directly to raw or minimally processed PPG waveforms, avoiding manual feature engineering.
In the same study, Dall'Olio et al. (2020) applied several convolutional neural networks to the whole PPG signal; the best, a 12-layer ResNet, reached an AUC of 95.3%, similar to the two-feature regression model but at a much higher computational cost.
For researchers implementing these models, our guide to PPG signal processing covers the preprocessing steps necessary before feature extraction or model inference.
Clinical Validation Studies
Comparison with Carotid-Femoral PWV
The gold standard for arterial stiffness assessment is carotid-femoral pulse wave velocity (cfPWV), measured using applanation tonometry (SphygmoCor) or oscillometric devices (Mobil-O-Graph). A cfPWV exceeding 10 m/s is considered a threshold for increased cardiovascular risk (2018 ESC/ESH Guidelines).
Millasseau et al. (2002) found that finger SI correlated with tonometric cfPWV at r = 0.65, and that SI and cfPWV had similar regression relationships with age and mean arterial pressure (doi:10.1042/cs1030371).
Charlton et al. (2022) (doi:10.1152/ajpheart.00392.2021) reviewed PPG-based vascular age assessment for VascAgeNet, covering single-PPG pulse wave analysis, multi-site PPG (such as pulse transit time), and PPG combined with other signals, along with the evidence on performance, repeatability, and clinical utility.
Population Studies and Risk Stratification
The Framingham Heart Study has contributed extensively to understanding arterial stiffness as a cardiovascular risk predictor. Mitchell et al. (2010) (doi:10.1161/CIRCULATIONAHA.109.886655) followed 2,232 participants for a median of 7.8 years and found that higher aortic PWV was associated with a 48% increase in cardiovascular disease risk per SD (95% CI: 1.16-1.91), independent of traditional risk factors. An individual participant meta-analysis of 17,635 subjects by Ben-Shlomo et al. (2014) (doi:10.1016/j.jacc.2013.09.063) reached a similar conclusion: after adjustment for conventional risk factors, each 1-SD increase in log-transformed aortic PWV carried a hazard ratio of 1.30 for cardiovascular events. While these studies used tonometric PWV, the principle applies to PPG-derived estimates that correlate with these measurements.
Vascular Age Gap as a Biomarker
The clinical value of a PPG vascular age estimate lies less in the absolute number than in the gap between estimated vascular age and chronological age. A positive gap points toward accelerated arterial aging. Arterial stiffness is increased in hypertension and diabetes mellitus (Prenner and Chirinos, 2015; doi:10.1016/j.atherosclerosis.2014.12.023), as well as with other cardiovascular risk factors such as smoking, so a persistently elevated gap is a prompt to review risk factors rather than a diagnosis in itself.
Practical Implementation Considerations
Signal Quality Requirements
Vascular age estimation demands higher signal quality than simple heart rate detection. The dicrotic notch and reflected wave features that encode stiffness information are subtle morphological details that are easily corrupted by motion artifacts, poor sensor contact, or vasoconstriction.
Key quality requirements include:
- Signal-to-noise ratio: Greater than 15 dB for reliable dicrotic notch detection
- Sampling rate: Minimum 100 Hz, preferably 250 Hz or higher to resolve fine morphological features
- Sensor contact: Consistent contact pressure; finger-clip sensors provide more reproducible waveforms than wrist-based reflectance sensors
- Physiological state: Measurements should be taken at rest, in a thermoneutral environment, after 5 minutes of seated acclimatization
Our guide to motion artifact removal describes the preprocessing necessary to ensure waveform quality before stiffness analysis.
Measurement Site Considerations
The PPG waveform morphology varies substantially by measurement site due to pulse wave amplification and site-specific vascular properties:
- Fingertip (transmission mode): Highest signal quality and most studied site for vascular assessment. The digital arteries provide clear systolic and diastolic peaks. Most SI and APG validation studies use this site.
- Ear lobe: Good signal quality with minimal motion artifact but less studied for vascular age assessment.
- Wrist (reflectance mode): Most convenient for wearable applications but lower signal quality and less pronounced diastolic features. Requires site-specific calibration models.
- Toe: Useful for lower-extremity vascular assessment and ankle-brachial index estimation.
Transfer functions exist to map peripheral waveforms to central aortic waveforms, but these introduce additional estimation error. Site-specific normative databases are essential for accurate vascular age scoring.
Confounding Factors
Several physiological and environmental factors affect PPG waveform morphology independently of arterial stiffness:
- Heart rate: Higher heart rates shorten the cardiac cycle, compressing waveform features. AIx shows a strong heart rate dependence (approximately -4% per 10 bpm increase). Rate correction is essential.
- Blood pressure: Acute blood pressure changes alter waveform morphology through changes in vascular tone.
- Vasoactive substances: Caffeine, nicotine, and medications affecting vascular tone can transiently alter PPG-derived stiffness indices.
- Temperature: Cold-induced vasoconstriction dramatically changes PPG waveform morphology and can inflate stiffness estimates.
- Respiration: Respiratory-induced blood pressure variations modulate pulse wave features. Averaging across respiratory cycles or using respiratory gating improves measurement stability.
For a deeper understanding of how these factors affect PPG signals, see our page on conditions affecting PPG measurements.
Future Directions
Multi-Wavelength Vascular Assessment
Most vascular age studies use single-wavelength green or infrared PPG. Multi-wavelength systems (combining green, red, and infrared) can simultaneously probe different tissue depths, potentially separating superficial microvascular compliance from deeper conduit artery stiffness. Whether wavelength-dependent differences in pulse wave morphology carry additional vascular information beyond single-wavelength analysis remains an open research question.
For background on how different wavelengths interact with tissue, see our comparison of green vs. red vs. infrared PPG.
Continuous Monitoring and Trend Analysis
Unlike single-point-in-time measurements, wearable PPG enables continuous or repeated vascular age estimation over days, weeks, and months. This longitudinal capability could detect vascular aging trajectories, monitor responses to antihypertensive therapy or lifestyle interventions, and provide early warning of accelerated stiffening.
The size of the changes such monitoring would need to detect is known from reference methods. A meta-analysis of 42 randomized trials (1,627 participants) found that aerobic exercise training reduced PWV by a weighted mean of 0.63 m/s (0.39 m/s for carotid-femoral PWV), with larger reductions in people with stiffer arteries at baseline (Ashor et al., 2014; doi:10.1371/journal.pone.0110034). Changes of this size are smaller than typical day-to-day measurement variability, which is why repeated, standardized measurements matter more than any single reading.
Open Validation Questions
Two gaps limit clinical use today. First, most PPG vascular age models were developed in specific, often East Asian or European, cohorts, and how well they generalize across ethnicities, body compositions, skin tones, and comorbidity profiles is incompletely characterized. Second, PPG-derived vascular age correlates with established risk factors, but prospective evidence that it adds predictive value for hard endpoints (myocardial infarction, stroke, cardiovascular death) beyond existing risk scores such as SCORE2 is still lacking.
Integration with Other PPG Biomarkers
Vascular age estimation becomes more powerful when combined with other PPG-derived parameters including heart rate variability, blood pressure estimation, and SpO2. Multi-parameter cardiovascular risk scores derived entirely from PPG could provide comprehensive screening without requiring multiple devices or clinical visits. This integrative approach represents one of the most promising directions for PPG-based cardiovascular health assessment.
Conclusion
PPG-based vascular age assessment transforms a simple optical pulse measurement into a window on arterial health. While not yet a replacement for clinical-grade tonometric PWV measurement, PPG-derived stiffness indices provide accessible, repeatable, and increasingly accurate estimates of vascular aging that are well-suited for screening, monitoring, and population health applications. As machine learning models improve and wearable sensor quality advances, the gap between PPG-based estimates and reference measurements continues to narrow, bringing non-invasive vascular age assessment closer to widespread clinical and consumer use.
References
- Reference Values for Arterial Stiffness' Collaboration. (2010). Determinants of pulse wave velocity in healthy people and in the presence of cardiovascular risk factors: 'establishing normal and reference values'. European Heart Journal, 31(19), 2338-2350. https://doi.org/10.1093/eurheartj/ehq165
- Millasseau, S. C., et al. (2002). Determination of age-related increases in large artery stiffness by digital pulse contour analysis. Clinical Science, 103(4), 371-377. https://doi.org/10.1042/cs1030371
- Takazawa, K., et al. (1998). Assessment of vasoactive agents and vascular aging by the second derivative of photoplethysmogram waveform. Hypertension, 32(2), 365-370. https://doi.org/10.1161/01.HYP.32.2.365
- Bortolotto, L. A., et al. (2000). Assessment of vascular aging and atherosclerosis in hypertensive subjects: second derivative of photoplethysmogram versus pulse wave velocity. American Journal of Hypertension, 13(2), 165-171. https://doi.org/10.1016/S0895-7061(99)00192-2
- Dall'Olio, L., et al. (2020). Prediction of vascular aging based on smartphone acquired PPG signals. Scientific Reports, 10, 19756. https://doi.org/10.1038/s41598-020-76816-6
- Charlton, P. H., et al. (2022). Assessing hemodynamics from the photoplethysmogram to gain insights into vascular age: a review from VascAgeNet. American Journal of Physiology-Heart and Circulatory Physiology, 322(4), H493-H522. https://doi.org/10.1152/ajpheart.00392.2021
- Mitchell, G. F., et al. (2010). Arterial stiffness and cardiovascular events: the Framingham Heart Study. Circulation, 121(4), 505-511. https://doi.org/10.1161/CIRCULATIONAHA.109.886655
- Ben-Shlomo, Y., et al. (2014). Aortic pulse wave velocity improves cardiovascular event prediction: an individual participant meta-analysis of prospective observational data from 17,635 subjects. Journal of the American College of Cardiology, 63(7), 636-646. https://doi.org/10.1016/j.jacc.2013.09.063
- Prenner, S. B., & Chirinos, J. A. (2015). Arterial stiffness in diabetes mellitus. Atherosclerosis, 238(2), 370-379. https://doi.org/10.1016/j.atherosclerosis.2014.12.023
- Ashor, A. W., et al. (2014). Effects of exercise modalities on arterial stiffness and wave reflection: a systematic review and meta-analysis of randomized controlled trials. PLoS ONE, 9(10), e110034. https://doi.org/10.1371/journal.pone.0110034
Related articles
PPG Augmentation Index (AIx): Waveform Analysis for Arterial Stiffness Assessment
**The augmentation index derived from photoplethysmography waveforms provides a non-invasive window into arterial stiffness and cardiovascular health,...
Pulse Wave Analysis Using PPG: Waveform Features, Vascular Health, and Clinical Applications
Complete guide to pulse wave analysis from PPG signals. Covers augmentation index, stiffness index, derivatives, fiducial points, and vascular assessment.
PPG Waveform Decomposition: Extracting Physiological Components from the Pulse Wave
**The photoplethysmography waveform is not a simple cardiac pulse but a composite signal encoding information about cardiac function, vascular complia...
PAD Detection with PPG: Ankle-Brachial Index, Pulse Wave Analysis & Screening
**Peripheral artery disease affects over 230 million people worldwide, yet up to 50% of cases remain undiagnosed because standard screening requires s...
Simultaneous Multi-Site PPG Measurement: Techniques, Applications & Pulse Transit Time
**Simultaneous PPG measurement at multiple body sites unlocks physiological parameters that are fundamentally inaccessible from a single measurement l...
Athletic and Sports Performance Metrics from PPG: VO2max, Lactate Threshold & Recovery Analysis
**The photoplethysmographic (PPG) sensor in a wrist-worn device or chest-strap monitor captures far more than just heart rate during exercise. The con...