PPG Contact Pressure Optimization: How Sensor Force Affects Signal Quality
**The contact pressure between a PPG sensor and the skin is a critical but frequently neglected determinant of signal quality, with the difference bet...
- PPG & Signal Processing
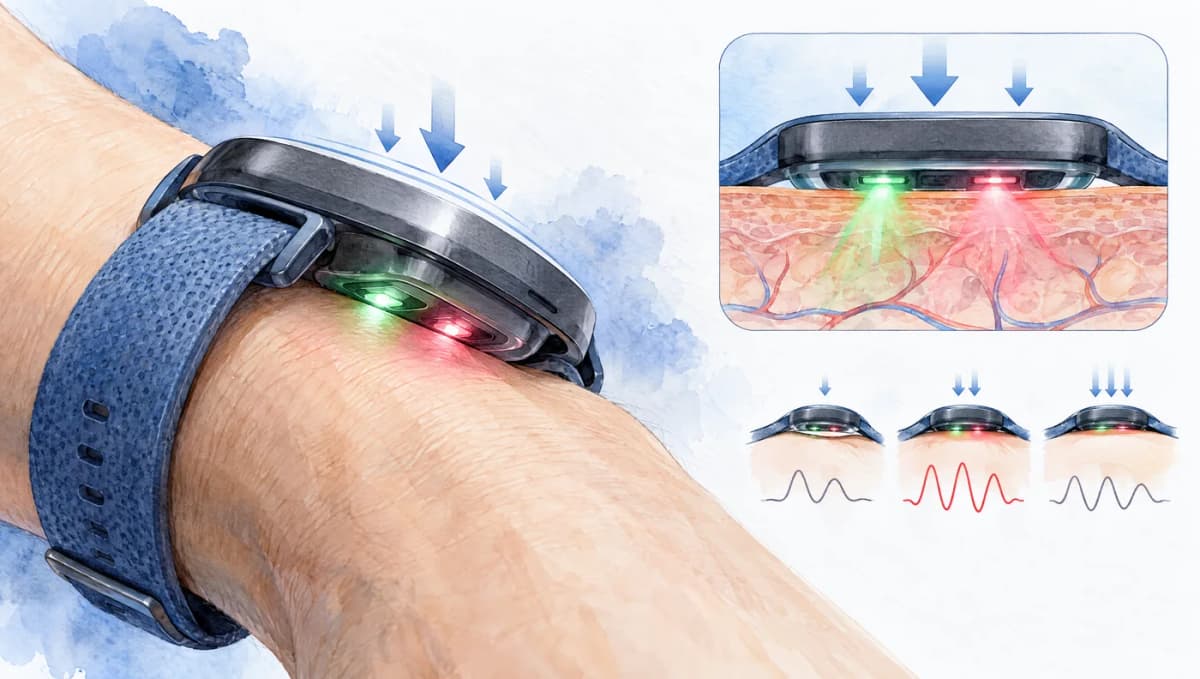
The contact pressure between a PPG sensor and the skin is a critical but frequently neglected determinant of signal quality, with the difference between optimal and suboptimal pressure capable of changing signal amplitude by a factor of 5-10 and introducing systematic errors in SpO2, blood pressure, and waveform-derived parameters. Unlike electronic noise or motion artifacts, which have well-characterized mitigation strategies, contact pressure effects are governed by the biomechanics of tissue compression and vascular physiology, making them fundamentally different from other noise sources and requiring specific design and protocol considerations.
This guide covers the biophysics of how contact pressure modulates the PPG signal, quantifies the optimal pressure ranges for different measurement sites, reviews the implications for SpO2 and waveform accuracy, and discusses design strategies for maintaining consistent contact force in both clinical and wearable devices. For background on PPG signal fundamentals, see our introduction to PPG technology.
Biophysics of Tissue Under Pressure
When a PPG sensor applies force to the skin surface, several physical changes occur simultaneously that affect the optical measurement:
Vascular Compression
External pressure applied to the skin surface is transmitted through soft tissue to the underlying vasculature. The transmural pressure of a vessel (the difference between internal blood pressure and external tissue pressure) determines whether the vessel remains patent (open) or collapses. Veins and venules, with typical transmural pressures of 5-15 mmHg, collapse first. Capillaries (transmural pressure 15-25 mmHg) collapse at moderate external pressures. Arterioles and small arteries (transmural pressure 30-80 mmHg) resist compression until higher forces are applied.
This sequential compression has a direct and predictable effect on the PPG signal. At zero external pressure, the optical path samples all vascular compartments: arterial, capillary, and venous. As external pressure increases, venous blood is displaced first, reducing the DC (baseline) component. Continuing to increase pressure progressively eliminates the venous and then capillary blood volume, initially improving the pulsatile-to-baseline ratio (because venous blood contributes to DC but not AC) before reducing the AC component as the arterial pulsatile compartment is itself compressed.
Optical Coupling
The interface between the sensor window and the skin surface is a major source of optical loss in reflectance-mode PPG. At very low contact pressure, air gaps and imperfect contact create variable scattering at the sensor-skin interface. Increasing pressure improves optical coupling by deforming the skin to conform to the sensor surface, reducing air gaps, and creating a more uniform optical interface.
This coupling effect explains why PPG signal quality often improves dramatically with initial pressure application, even before vascular compression effects become significant.
Tissue Deformation
Soft tissue is viscoelastic, meaning it exhibits both elastic (spring-like) and viscous (time-dependent) behavior under load. When sustained pressure is applied, the tissue initially deforms rapidly (elastic response) and then continues to creep (viscous response) over seconds to minutes. This creep causes the PPG baseline to drift gradually after sensor application, with the signal stabilizing over 30-90 seconds as the tissue reaches mechanical equilibrium.
For measurement protocols, this means that PPG signals recorded immediately after sensor application are not representative of steady-state conditions. A stabilization period of at least 30-60 seconds should be allowed before collecting data for analysis, particularly for any parameter that depends on baseline stability or waveform morphology.
The Contact Pressure-Signal Amplitude Relationship
The relationship between contact pressure and PPG signal amplitude follows a characteristic non-monotonic curve that has been documented across multiple studies and measurement sites.
The Inverted-U Response
Teng and Zhang (2004) (doi:10.1088/0967-3334/25/5/020) published a foundational study on contact force effects on reflective finger PPG. They recorded signals from the fingers of 15 healthy subjects while increasing contact force from 0.2 N to 1.8 N. Their key findings included:
- Pulse (AC) amplitude and the AC/DC ratio first increased and then decreased with increasing force
- The force giving peak amplitude varied between subjects (0.2-1.0 N), and most subjects reached maximum pulse amplitude at 0.2-0.4 N
- The DC amplitude increased with contact force, while the normalized pulse area decreased
- Between 0.2 N and 0.8 N, DC amplitude and normalized pulse area changed significantly
The inverted-U shape arises from the combination of two competing effects. At low pressures, increasing force improves optical coupling and compresses venous blood (improving AC/DC ratio). At high pressures, the dominant effect is arterial compression, which reduces pulsatile blood volume. The optimal point balances these two effects.
Site-Specific Optimal Pressures
The optimal contact pressure varies by measurement site, primarily determined by local tissue thickness, vascular depth, and arterial pressure:
Fingertip (transmission mode): Optimal force approximately 0.5-1.0 N. Clinical finger-clip pulse oximeters use spring mechanisms intended to keep force in a moderate range. Excessive clip force is a recognized source of error, particularly in pediatric patients with smaller fingers and lower arterial pressure.
Fingertip (reflectance mode): In Teng and Zhang (2004), most subjects reached maximum pulse amplitude at 0.2-0.4 N. Lower than transmission mode because the sensor only needs to couple with the skin surface rather than compress through the entire finger.
Wrist: Optimal force approximately 0.3-0.6 N/cm2 distributed over the sensor area. Wrist PPG is more complex because the primary vascular target (radial artery) lies 2-4 mm beneath the surface, and surface pressure affects superficial vessels disproportionately relative to the artery. Excessive wrist pressure can paradoxically reduce PPG signal quality by collapsing superficial capillaries while not significantly compressing the radial artery, reducing the SNR of the arterial pulsatile signal.
Ear lobe: Optimal force approximately 0.3-0.5 N. The thin tissue of the ear lobe makes it sensitive to over-compression, and spring forces above 1 N can cause discomfort and vascular occlusion.
Forehead: Optimal pressure approximately 0.2-0.5 N/cm2. Forehead PPG sensors are typically applied with adhesive rather than clamping force, and the flat contact area distributes pressure evenly. The superficial temporal artery provides a relatively robust signal that is less sensitive to moderate pressure variations.
Effects on SpO2 Accuracy
Contact pressure systematically affects pulse oximetry SpO2 measurements through two mechanisms. First, the reduced signal amplitude at non-optimal pressures degrades SNR and increases measurement noise. Second, non-uniform compression of arterial versus venous compartments changes the effective composition of the pulsatile blood volume, altering the R-ratio.
Contact pressure may also shift SpO2 readings. The direction of any shift depends on whether venous blood (which is less oxygenated) is included in or excluded from the pulsatile signal. At very light pressure, venous pulsations contribute to the AC signal, pulling the SpO2 reading down. At moderate pressure, venous pulsations are eliminated, giving a pure arterial SpO2. At excessive pressure, the remaining pulsatile signal may not be representative of arterial blood.
The practical implication is that probe selection and proper application matter for SpO2 accuracy, and that interchanging probes between devices can introduce systematic measurement differences.
Waveform Morphology Changes Under Pressure
Contact pressure affects not only signal amplitude but also the shape of the PPG waveform, with implications for all morphology-dependent derived parameters.
Dicrotic Notch and Reflected Wave
As contact pressure increases from zero to the optimal range, the dicrotic notch becomes more clearly defined and the reflected wave component more visible. This is because venous blood, which does not pulsate synchronously with the arterial system, adds a broadband noise-like component that smooths waveform features. Eliminating the venous contribution through moderate compression clarifies the arterial waveform morphology.
However, excessive pressure distorts the waveform by narrowing the systolic peak (due to reduced pulse pressure at the partially occluded measurement site), attenuating the diastolic component disproportionately, and introducing artifactual oscillations from tissue mechanical resonance.
Implications for Derived Parameters
Any PPG-derived parameter that depends on waveform shape is affected by contact pressure. This includes the augmentation index and other vascular stiffness indices, blood pressure estimation from pulse transit time (PTT) or pulse wave analysis, pulse rate variability derived from beat-to-beat intervals, and respiratory rate estimation from the respiratory modulation envelope. For these applications, contact pressure should be standardized, documented, and ideally actively monitored and controlled.
Because pulse-timing measurements depend on fiducial points in the waveform, pressure-induced changes in waveform shape can also bias pulse transit time, so pressure errors can matter for applications beyond simple heart rate monitoring.
Design Strategies for Consistent Contact Pressure
Clinical Devices
Clinical finger-clip pulse oximeters use spring mechanisms calibrated to apply force in the optimal range. Design considerations include spring constant selection that maintains force within the optimal range across the full range of finger sizes (pediatric through adult), pivot geometry that distributes force evenly across the sensor-skin contact area, and soft rubber or silicone padding that improves optical coupling while distributing pressure.
Reusable finger clips should be tested periodically for spring fatigue, as repeated use can reduce the spring force below optimal levels. Disposable adhesive sensors avoid this issue but introduce adhesive-related optical coupling variables.
Wrist-Worn Wearables
Achieving consistent contact pressure at the wrist is fundamentally more challenging than at the finger because the wrist is irregularly shaped, changes diameter with hand position and muscle flexion, and is subject to continuous gravitational and inertial forces during daily activities. Design strategies include:
Sensor protrusion: Many wrist wearables have the PPG sensor module protruding slightly (0.5-1.5 mm) from the case back surface. This concentrates contact force on the sensor area, ensuring adequate coupling even if the watch body does not sit flush with the skin. The protrusion must be designed to not cause discomfort or pressure marks during extended wear.
Strap design: Strap material elasticity and closure mechanism affect contact pressure consistency. Silicone straps with micro-adjustment clasps allow finer tension control than leather or metal bands. Some advanced designs use a separate inner gasket or bridge that maintains sensor-to-skin pressure independently of overall band tension.
Pressure sensing: Integrating a force or pressure sensor adjacent to or beneath the PPG sensor enables real-time contact pressure monitoring. This data can be used to qualify measurements (flagging readings obtained at non-optimal pressure), provide user feedback (haptic or visual alert when the band is too loose or too tight), and apply pressure-dependent calibration corrections.
Ear-Worn Devices
In-ear PPG sensors face unique contact pressure challenges because the ear canal is a rigid, irregularly shaped cavity. Contact force is determined by the earbud fit, which varies widely across individuals and can change with jaw movement (talking, chewing). Compliant ear tips (silicone or foam) with internal spring elements can maintain more consistent pressure across different ear canal geometries.
Dynamic Pressure Effects and Motion Artifacts
During activity, contact pressure is not static but fluctuates continuously due to limb movement, muscle contraction, and inertial forces. These dynamic pressure changes are a significant source of motion artifacts in PPG, distinct from the purely optical motion artifacts caused by sensor-skin relative displacement.
Pressure-mediated motion artifacts have characteristic properties. They are typically lower frequency than displacement artifacts (concentrated below 2 Hz for most activities). They are correlated with accelerometer signals but with a different transfer function than optical displacement artifacts. They can be partially separated from displacement artifacts using multi-axis force sensing or by exploiting the different frequency characteristics.
For wrist-worn devices, gravitational effects during arm movement cause periodic pressure variations as the weight of the device shifts relative to the wrist. During running, for example, the arm swing cycle produces a pressure modulation at the step frequency (approximately 2.5-3.5 Hz) that is directly correlated with the primary motion artifact frequency. This correlation means that pressure-mediated and displacement-mediated motion artifacts are difficult to separate algorithmically, but hardware approaches (reducing device mass, improving strap compliance) can selectively reduce the pressure component.
Recommendations for Researchers and Engineers
Standardizing contact pressure in PPG measurements is essential for reproducibility and accuracy. The following practices are recommended:
For clinical measurement protocols: Use calibrated sensors with known, documented spring forces. Allow a 30-60 second stabilization period after sensor application before recording data. Record the contact force or pressure for each measurement session. Avoid positioning the sensor over bony prominences where tissue compression is non-uniform.
For wearable device design: Target contact pressure in the range of 0.3-0.8 N/cm2 for reflectance-mode sensors. Incorporate protrusion or compression geometry that concentrates force on the sensor area. Consider integrating force sensing for measurement qualification. Design strap and retention mechanisms that maintain consistent pressure across a range of body sizes and activity levels.
For signal processing: Include contact pressure as a covariate in any analysis of PPG-derived parameters. Implement signal quality metrics that are sensitive to pressure-related signal degradation (e.g., perfusion index thresholds, baseline stability criteria). When comparing measurements across devices or sessions, normalize for contact pressure differences.
Understanding contact pressure effects is one component of the broader challenge of maintaining PPG signal quality across diverse conditions. For other factors that influence measurement reliability, see our discussions of temperature effects, skin tone considerations, and the comprehensive algorithms and signal processing resources.
References
- Teng, X. F., & Zhang, Y. T. (2004). The effect of contacting force on photoplethysmographic signals. Physiological Measurement, 25(5), 1323-1335. https://doi.org/10.1088/0967-3334/25/5/020
Related articles
PPG Signal Quality Assessment: SQI Metrics, Methods & Implementation
**Signal quality assessment is the gatekeeper of every PPG processing pipeline, and deploying it incorrectly either discards usable data or passes cor...
PPG Reading Interpretation Guide: Normal Waveforms, Abnormal Patterns, and Signal Quality
Learn how to interpret a PPG reading. Covers normal waveform patterns, abnormal signals, AC/DC components, dicrotic notch, and signal quality assessment.
PPG Autoencoder Models for Cardiac Anomaly Detection and Signal Quality Screening
How autoencoders detect cardiac anomalies in PPG signals using reconstruction error, VAE latent spaces, and one-class classification for wearable monitoring.
PPG SNR Improvement Techniques: Raising Signal Quality Before Denoising
PPG SNR improvement techniques start before denoising. Improve optics, contact, motion control, and quality gating so algorithms work on better raw data.
Facial PPG Signal Extraction
Extracting a photoplethysmographic signal from the human face is a problem in optics, anatomy, and signal processing simultaneously. The face is rich ...