PPG Augmentation Index (AIx): Waveform Analysis for Arterial Stiffness Assessment
**The augmentation index derived from photoplethysmography waveforms provides a non-invasive window into arterial stiffness and cardiovascular health,...
- PPG & Signal Processing
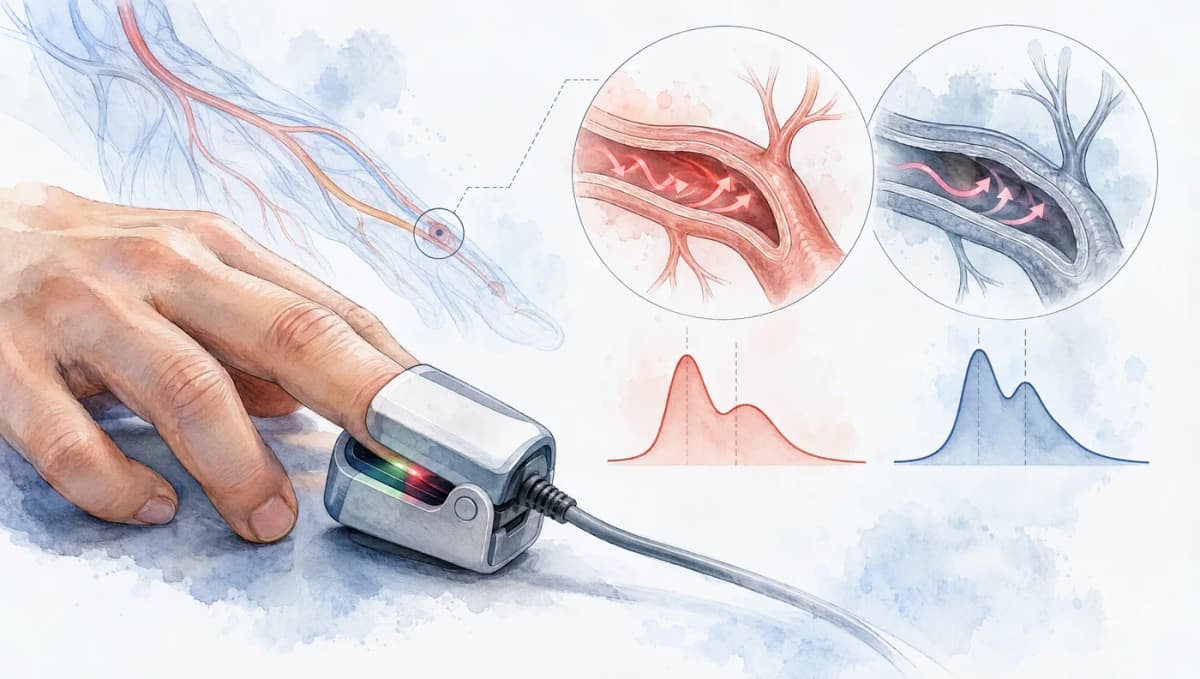
The augmentation index derived from photoplethysmography waveforms provides a non-invasive window into arterial stiffness and cardiovascular health, but extracting it reliably requires careful signal processing and an understanding of the underlying hemodynamics. Unlike simple heart rate or SpO2 extraction, AIx analysis depends on preserving the subtle morphological features of the PPG pulse wave, particularly the timing and amplitude of the reflected wave component. This guide covers the physics of wave reflection, computational methods for AIx extraction, clinical validation evidence, and the practical challenges of implementing waveform analysis in wearable devices.
For foundational context on how PPG signals are generated, see our introduction to PPG technology. The signal processing techniques discussed here build directly on the PPG signal processing algorithms framework.
Arterial Wave Reflection Physiology
The arterial pressure waveform is not a simple pulse. It is the superposition of a forward-traveling wave generated by left ventricular ejection and one or more backward-traveling reflected waves generated at impedance mismatch points in the arterial tree. These reflection sites include arterial bifurcations (particularly the aortic bifurcation), points where arterial diameter changes abruptly, and high-resistance arteriolar beds.
In young, compliant arteries, the pulse wave travels relatively slowly (4-6 m/s in the aorta). The reflected wave returns to the central aorta during diastole, augmenting diastolic pressure and improving coronary perfusion. As arteries stiffen with age, hypertension, diabetes, or atherosclerosis, pulse wave velocity increases (8-14 m/s in stiffened aortas). The reflected wave now returns during late systole rather than diastole, augmenting systolic pressure instead. This systolic augmentation increases left ventricular afterload and myocardial oxygen demand while simultaneously reducing diastolic coronary perfusion pressure.
The augmentation index quantifies this phenomenon. Defined for central aortic pressure as:
where P1 is the first systolic shoulder (forward wave peak), P2 is the late systolic peak (augmented by the reflected wave), and PP is the total pulse pressure. A negative AIx indicates that the reflected wave arrives after the systolic peak (typical in young subjects), while a positive and increasing AIx indicates earlier reflected wave arrival and greater systolic augmentation.
PPG Waveform Morphology and Wave Reflection
The PPG signal recorded at peripheral sites (finger, ear, wrist) does not directly reproduce the central aortic pressure waveform. The peripheral PPG waveform is shaped by pulse wave amplification, local vascular tone, and the transfer function of the arterial tree between the aorta and the measurement site. Despite these transformations, the reflected wave component is preserved in the PPG waveform morphology and can be quantified through several analytical approaches.
Millasseau et al. (2002) published a landmark validation study (doi:10.1042/cs1030371) demonstrating that the digital volume pulse (DVP) recorded by finger PPG contains information about large artery stiffness. They showed that a stiffness index derived from the timing of the direct and reflected wave components in the finger PPG correlates with carotid-femoral PWV measured by applanation tonometry (r = 0.65, p < 0.0001, n = 87).
The PPG pulse waveform typically exhibits two characteristic features related to wave reflection. The systolic peak corresponds primarily to the forward-traveling pulse wave. The diastolic component, often visible as a secondary peak or inflection point in the descending limb, is largely generated by the reflected wave. The relative timing and amplitude of these components encode information about arterial stiffness and wave reflection magnitude.
For a deeper understanding of how different wavelengths affect the capture of these waveform features, see our guide on green vs red vs infrared PPG.
Computational Methods for AIx Extraction
First Derivative Analysis
The simplest approach to identifying the reflected wave component uses the first derivative (dPPG/dt) of the PPG waveform. The zero crossings and extrema of the first derivative correspond to inflection points and peaks in the original waveform. The systolic peak is identified as the first major maximum, and the dicrotic notch (or inflection point) is identified from subsequent zero crossings (see dicrotic notch detection).
Takazawa et al. (1998) (doi:10.1161/01.HYP.32.2.365) defined a plethysmographic augmentation index as the ratio of the late to the early systolic peak and showed in 39 patients that the second-derivative d/a index tracked both plethysmographic and ascending aortic augmentation indices (r = 0.79 and 0.80). However, first derivative analysis is sensitive to high-frequency noise, and the reflected wave component often appears as a subtle shoulder rather than a distinct peak, making automated detection unreliable without preprocessing.
Second Derivative (SDPPG) Analysis
The second derivative of the PPG waveform (SDPPG, also called the acceleration plethysmogram) has proven more useful for waveform decomposition. The SDPPG of a single pulse cycle typically exhibits five characteristic waves, labeled a, b, c, d, and e by Takazawa et al. (1998):
- Wave a: Early systolic positive peak (initial upstroke acceleration)
- Wave b: Early systolic negative peak (deceleration after initial upstroke)
- Wave c: Late systolic re-acceleration peak (related to reflected wave arrival)
- Wave d: Late systolic/diastolic negative peak (deceleration after reflected wave)
- Wave e: Early diastolic positive peak (related to dicrotic wave)
The ratios of these wave amplitudes provide indices of vascular aging and arterial stiffness. The most commonly used is the aging index:
Takazawa et al. (1998) evaluated this index in 600 subjects, showing a strong age correlation (r = 0.80) and higher values in subjects with a history of diabetes, hypertension, hypercholesterolemia, or ischemic heart disease than in age-matched subjects without them. Imanaga et al. (1998) found in 82 subjects that the magnitude of b/a correlated positively with common carotid artery distensibility measured by ultrasound (doi:10.1536/ihj.39.775).
The SDPPG approach has several practical advantages. The five waves are typically more distinct and easier to detect algorithmically than features in the original waveform. The method is less affected by baseline wander, and the ratios are normalized, reducing sensitivity to signal amplitude variations. However, the SDPPG amplifies high-frequency noise (each differentiation multiplies noise by approximately 2pif), requiring careful bandpass filtering (typically 0.5-15 Hz) before derivative computation.
Pulse Decomposition Analysis
A more sophisticated approach models the PPG pulse as the superposition of multiple Gaussian or log-normal component waves, each corresponding to a distinct hemodynamic event. Baruch et al. (2011) (doi:10.1186/1753-4631-5-1) described Pulse Decomposition Analysis, which models the peripheral arterial pulse as five component pulses: the first from left ventricular ejection and the rest from reflections and re-reflections at two central arterial reflection sites.
The relative timing and amplitudes of these decomposed components provide direct estimates of wave reflection magnitude and timing. In Baruch et al.'s lower body negative pressure study of 15 subjects, the delay between the first and third components (T13) correlated significantly with pulse pressure. Millasseau et al. (2006) review how digital volume pulse contour measures relate to pressure-pulse contour analysis (doi:10.1097/01.hjh.0000239277.05068.87).
Pulse decomposition is computationally more expensive than derivative analysis, requiring iterative nonlinear optimization (typically Levenberg-Marquardt or Nelder-Mead algorithms). Convergence depends on good initial parameter estimates, which must be derived from the raw waveform features. For real-time implementation guidance on these types of algorithms, see our algorithms section.
Machine Learning Approaches
Recent work has applied deep learning to PPG-based arterial stiffness estimation, bypassing explicit waveform feature extraction entirely. For example, Slapnicar et al. (2019) (doi:10.3390/s19153420) trained a spectro-temporal ResNet on PPG waveforms and their derivatives from 510 subjects to estimate blood pressure, learning from both time-domain morphology and spectral representations. Similar architectures can be trained against arterial stiffness references. The advantage of deep learning is its ability to capture complex nonlinear relationships between waveform shape and arterial properties that simple ratios miss, but it requires large training datasets with gold-standard reference measurements.
Clinical Validation and Reference Values
Correlation with Gold-Standard Measures
The gold standard for AIx measurement is aortic applanation tonometry using the SphygmoCor system (AtCor Medical), which records the radial artery pressure waveform and applies a validated generalized transfer function to estimate central aortic pressure and AIx. PPG-derived AIx values do not directly correspond to tonometry-derived values because the peripheral PPG waveform undergoes different transformations than the pressure waveform.
Extensive validation studies have characterized the relationship. Takazawa et al. (1998) found that the SDPPG d/a index correlated with ascending aortic AIx (r = 0.80) in 39 patients. Correlations reported across studies vary with PPG measurement site, signal quality filtering criteria, and study population demographics.
A critical finding is that PPG-derived indices are more reliable for tracking within-subject changes over time than for absolute cross-sectional assessment. Bland-Altman analysis typically shows mean biases of 5-15% with limits of agreement of plus or minus 20-30%, which is insufficient for clinical diagnosis but potentially useful for longitudinal monitoring and screening applications.
Age and Sex Normative Data
Central AIx measured by tonometry follows well-characterized age and sex patterns. McEniery et al. (2005) (doi:10.1016/j.jacc.2005.07.037) characterized these patterns in the Anglo-Cardiff Collaborative Trial (ACCT), involving 4,001 healthy, normotensive individuals aged 18-90. AIx and aortic PWV both increased with age, but non-linearly: AIx rose more in younger individuals (under 50), while aortic PWV rose more in older individuals. The authors concluded that AIx may be a more sensitive marker of arterial stiffening in younger people and aortic PWV a better measure in older people.
Women generally show higher AIx values than men, partly due to shorter stature (a shorter aortic path length means earlier wave reflection), and height is an independent determinant of AIx.
PPG-derived reflection indices follow similar age trends but with different absolute scales depending on the specific index used. SDPPG aging index increases with age (r = 0.80 in Takazawa et al.'s 600 subjects), making it a reasonable surrogate for vascular aging assessment in population screening contexts.
Measurement Site Considerations
The choice of PPG measurement site significantly affects the quality and interpretability of AIx-related waveform features. Each site imposes different constraints on waveform morphology.
Finger PPG
The finger is the most validated site for PPG-based arterial stiffness assessment. The fingertip has a dense superficial capillary bed, producing high-amplitude pulsatile signals with clearly resolved systolic and diastolic components. Transmission-mode finger PPG (light source and detector on opposite sides of the finger) produces cleaner waveforms than reflectance-mode, with the dicrotic notch and reflected wave components more consistently identifiable.
Millasseau et al. (2002, 2006) conducted their primary validation work using finger PPG, which remains the reference site for PPG-based vascular assessment. The stiffness index () derived from finger PPG correlated with carotid-femoral PWV at r = 0.65 (doi:10.1042/cs1030371).
Wrist PPG
Wrist PPG presents greater challenges for AIx extraction. The radial artery is deeper than fingertip capillaries, the reflectance-mode geometry captures more superficial tissue signals, and the waveform is more susceptible to motion artifacts and contact pressure variations. The reflected wave component is often attenuated or obscured in wrist PPG waveforms, particularly at green wavelengths where penetration depth is shallow (1-2 mm).
Despite these challenges, wrist PPG is the most practically relevant site given the ubiquity of wrist-worn wearables. Research is ongoing to determine whether advanced signal processing and machine learning can compensate for the lower waveform fidelity. For details on how sensor positioning affects signal quality, see our PPG sensor placement comparison.
Ear PPG
Ear lobe and ear canal PPG offer intermediate waveform quality between finger and wrist. The ear has relatively thin tissue with good superficial vascularization, and the dicrotic notch is usually identifiable. Ear-based wearables (hearables) are therefore a candidate platform for continuous AIx monitoring, although validation against finger PPG and tonometry is limited.
Practical Implementation Challenges
Sampling Rate Requirements
AIx extraction demands higher sampling rates than simple heart rate detection. Heart rate can be reliably estimated from PPG sampled at 25-50 Hz, but waveform morphology analysis requires at least 100 Hz, and many researchers recommend 250-1000 Hz for optimal resolution of the reflected wave timing. The temporal resolution needed to distinguish the systolic peak from the reflected wave shoulder is on the order of 10-30 ms, corresponding to a Nyquist frequency of at least 33-100 Hz.
Allen (2007) (doi:10.1088/0967-3334/28/3/R01) gives a comprehensive review of PPG instrumentation, measurement protocol, and pulse wave analysis for vascular assessment.
Signal Quality Assessment
Not every PPG pulse is suitable for AIx analysis. Signal quality screening is essential to exclude pulses corrupted by motion artifacts, ectopic beats, respiratory modulation, or poor sensor contact. A robust implementation should include beat-by-beat quality assessment using template matching (correlation with a rolling average beat template, threshold r > 0.90), amplitude consistency checking (rejecting beats where peak amplitude deviates more than 30% from the running median), and morphological validation (confirming the presence of expected waveform features).
Elgendi (2016) (doi:10.3390/bioengineering3040021) compared eight PPG signal quality indices (including perfusion, kurtosis, skewness, and entropy) on 106 expert-annotated recordings and found that skewness performed best, with F1 scores of 79.1-87.2% across classification tasks.
Heart Rate Correction
AIx is strongly heart-rate-dependent. Higher heart rates shorten the ejection period and alter the timing of wave reflection relative to the cardiac cycle, systematically reducing AIx. Wilkinson et al. (2000) (doi:10.1111/j.1469-7793.2000.t01-1-00263.x) used incremental cardiac pacing in 22 subjects and found an inverse linear relationship between AIx and heart rate (r = -0.76), with AIx falling by around 4% for each 10 BPM increase. AIx is therefore commonly normalized to a standard heart rate, such as 75 BPM.
Any PPG-based AIx measurement must incorporate heart rate correction to be meaningful for cross-sectional comparisons or longitudinal tracking. Without this correction, an increase in resting heart rate from exercise training could be misinterpreted as a decrease in arterial stiffness.
Clinical Applications and Future Directions
PPG-derived AIx and related vascular indices have potential applications in cardiovascular risk screening, hypertension management monitoring, and pharmacological intervention assessment. The low cost and accessibility of PPG technology make it attractive for population-level screening, where identifying individuals with accelerated vascular aging could prompt earlier preventive intervention.
Current limitations include the moderate correlation with gold-standard measures, the influence of confounders (heart rate, temperature, vasoactive substances, hydration status), and the lack of standardized measurement protocols and reference ranges specific to PPG. The field needs large, multi-site validation studies comparing PPG-derived indices against clinical outcomes (stroke, myocardial infarction, cardiovascular mortality) rather than only against surrogate measures like tonometric AIx.
Integration of AIx analysis with other PPG-derived parameters, including heart rate variability and blood pressure estimation, could provide a more comprehensive cardiovascular profile from a single optical sensor. Machine learning models that jointly estimate multiple cardiovascular parameters from the PPG waveform may achieve better accuracy than single-parameter approaches by leveraging shared physiological information.
For researchers implementing PPG waveform analysis systems, the key priorities are maintaining high sampling rates (at least 100 Hz), implementing rigorous signal quality filtering, applying heart rate correction, and validating against established reference methods in diverse populations. The clinical promise is substantial, but the technical requirements for reliable AIx extraction from PPG remain demanding.
References
- Millasseau, S. C., et al. (2002). Determination of age-related increases in large artery stiffness by digital pulse contour analysis. Clinical Science, 103(4), 371-377. https://doi.org/10.1042/cs1030371
- Takazawa, K., et al. (1998). Assessment of vasoactive agents and vascular aging by the second derivative of photoplethysmogram waveform. Hypertension, 32(2), 365-370. https://doi.org/10.1161/01.HYP.32.2.365
- Imanaga, I., Hara, H., Koyanagi, S., & Tanaka, K. (1998). Correlation between wave components of the second derivative of plethysmogram and arterial distensibility. Japanese Heart Journal, 39(6), 775-784. https://doi.org/10.1536/ihj.39.775
- Baruch, M. C., et al. (2011). Pulse decomposition analysis of the digital arterial pulse during hemorrhage simulation. Nonlinear Biomedical Physics, 5, 1. https://doi.org/10.1186/1753-4631-5-1
- Millasseau, S. C., Ritter, J. M., Takazawa, K., & Chowienczyk, P. J. (2006). Contour analysis of the photoplethysmographic pulse measured at the finger. Journal of Hypertension, 24(8), 1449-1456. https://doi.org/10.1097/01.hjh.0000239277.05068.87
- Slapnicar, G., Mlakar, N., & Lustrek, M. (2019). Blood pressure estimation from photoplethysmogram using a spectro-temporal deep neural network. Sensors, 19(15), 3420. https://doi.org/10.3390/s19153420
- McEniery, C. M., et al. (2005). Normal vascular aging: differential effects on wave reflection and aortic pulse wave velocity: the Anglo-Cardiff Collaborative Trial (ACCT). Journal of the American College of Cardiology, 46(9), 1753-1760. https://doi.org/10.1016/j.jacc.2005.07.037
- Allen, J. (2007). Photoplethysmography and its application in clinical physiological measurement. Physiological Measurement, 28(3), R1-R39. https://doi.org/10.1088/0967-3334/28/3/R01
- Elgendi, M. (2016). Optimal signal quality index for photoplethysmogram signals. Bioengineering, 3(4), 21. https://doi.org/10.3390/bioengineering3040021
- Wilkinson, I. B., et al. (2000). The influence of heart rate on augmentation index and central arterial pressure in humans. The Journal of Physiology, 525(1), 263-270. https://doi.org/10.1111/j.1469-7793.2000.t01-1-00263.x
Core guide: Augmentation Index (AIx) from PPG Waveform Analysis
Related articles
PPG Vascular Age Assessment: Arterial Stiffness Measurement from Pulse Wave Analysis
**Arterial stiffness is one of the earliest detectable markers of cardiovascular disease, and the PPG waveform encodes surprisingly rich information a...
PAD Detection with PPG: Ankle-Brachial Index, Pulse Wave Analysis & Screening
**Peripheral artery disease affects over 230 million people worldwide, yet up to 50% of cases remain undiagnosed because standard screening requires s...
Continuous Blood Pressure Monitoring from PPG: Beat-to-Beat Waveform Analysis
**Beat-to-beat blood pressure monitoring from PPG waveform analysis represents the frontier of non-invasive hemodynamic assessment, offering the possi...
Pulse Wave Analysis Using PPG: Waveform Features, Vascular Health, and Clinical Applications
Complete guide to pulse wave analysis from PPG signals. Covers augmentation index, stiffness index, derivatives, fiducial points, and vascular assessment.
Arterial Line Waveform: 1-2 Oscillations Optimal
Square-wave test: 1-2 oscillations is optimal (damping 0.5-0.7). None or one sluggish oscillation means overdamped; 3 or more means underdamped.
PPG Autonomic Function Testing: Nervous System Assessment via PPG-Derived HRV
**The autonomic nervous system (ANS) controls virtually every involuntary physiological process, and its dysfunction underlies or accompanies a wide r...