Reflectance vs Transmittance PPG: Sensor Modes Compared for Accuracy, SNR & Wearable Design
**Transmittance PPG through the fingertip remains the gold standard for clinical pulse oximetry, while reflectance PPG has become the universal mode f...
- SpO2 & Oximetry
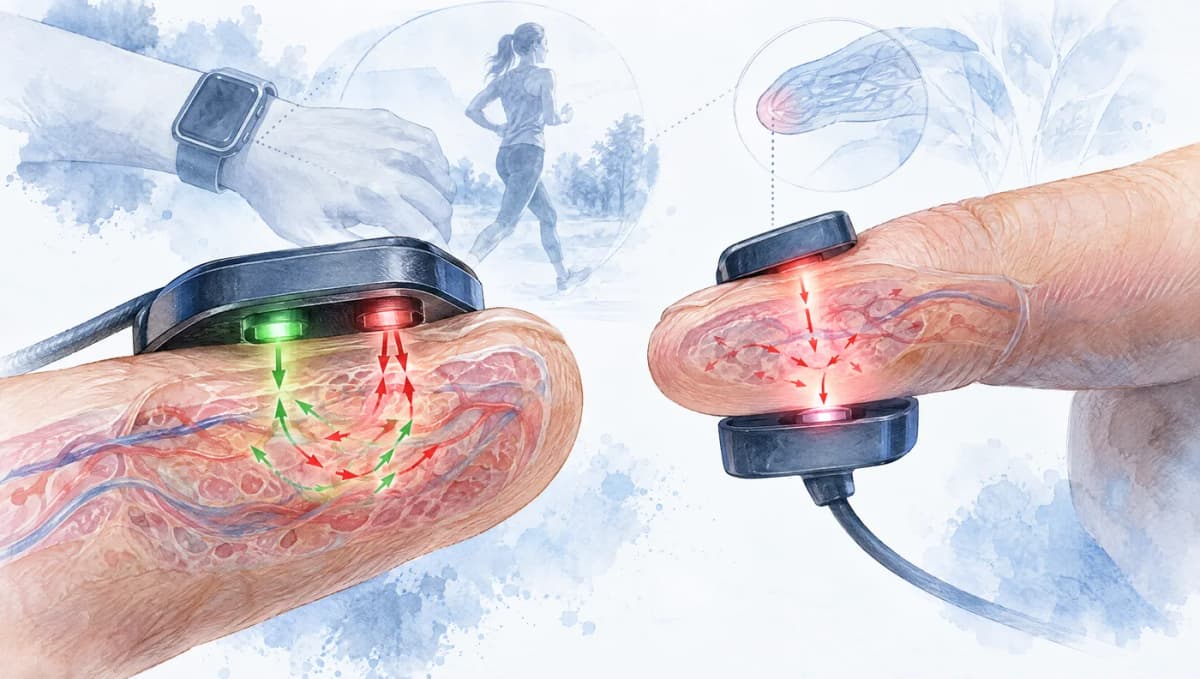
Transmittance PPG through the fingertip remains the gold standard for clinical pulse oximetry, while reflectance PPG has become the universal mode for wrist-worn wearables because the wrist is simply too thick for light to pass through. This fundamental constraint of tissue geometry drives the entire distinction between the two modes, affecting signal quality, measurement accuracy, body site selection, and sensor design. Understanding the physics behind each mode is essential for anyone designing PPG sensors, interpreting clinical pulse oximetry data, or evaluating wearable device accuracy.
This article provides a rigorous technical comparison of reflectance and transmittance PPG, covering optical physics, signal characteristics, accuracy data, and practical design considerations. For foundational PPG concepts, see our introduction to PPG technology. For how LED wavelength interacts with measurement mode, see our wavelength comparison guide.
Optical Physics of Each Mode
Transmittance PPG
In transmittance (also called transmission) mode, the LED light source and photodetector are positioned on opposite sides of the tissue. Light enters the tissue from the LED side, passes through the full tissue thickness, and exits on the detector side. The detected intensity is the residual light that has survived absorption and scattering through the entire tissue volume.
The Beer-Lambert law provides the theoretical framework:
where is the incident intensity, is the absorption coefficient of the tissue, and is the optical path length (approximately equal to the tissue thickness). In practice, scattering dominates over absorption in biological tissue, and the modified Beer-Lambert law introduces a differential path length factor (DPF) and a scattering loss term:
where DPF accounts for the increased path length due to scattering and G represents scattering-related losses. Delpy et al. (1988) estimated optical pathlength directly from the time of flight of picosecond light pulses; across the rat head, the pathlength was 5.3 +/- 0.3 times the head diameter (doi:10.1088/0031-9155/33/12/008).
The key advantage of transmittance mode is that the optical path traverses the full arterial cross-section. Light passes through the arteries, arterioles, capillaries, venules, and veins in the tissue, and the pulsatile component arises from the blood volume changes in the arteries and arterioles. Because the light traverses the entire tissue, it samples a large arterial volume, producing a strong pulsatile signal.
Reflectance PPG
In reflectance mode, the LED and photodetector are positioned on the same surface of the tissue, separated by a distance typically ranging from 3-10 mm. Light enters the tissue from the LED, penetrates to a depth determined by the wavelength-dependent absorption and scattering properties, and is backscattered toward the detector.
The interrogated tissue volume in reflectance mode forms a banana-shaped region between the LED and detector, with a depth approximately half the source-detector separation. For a typical LED-detector separation of 5 mm, the measurement depth is approximately 2-3 mm, sampling only the superficial dermis and subcutaneous tissue.
Schmitt (1991) used photon diffusion theory to derive the ac-dc intensity ratios measured by transmission-mode and reflectance-mode pulse oximeters, showing that multiple scattering makes the calibration sensitive to tissue attenuation, blood volume, and source-detector placement (doi:10.1109/10.137285). In the diffusion approximation, reflectance falls off with separation approximately as:
where is the source-detector separation and is the effective attenuation coefficient. This relationship shows that detected intensity drops rapidly with source-detector separation, limiting the practical range and the measurement depth.
Photon Path Differences
The fundamental difference between modes is the photon path geometry through the vascular bed:
Transmittance: Photons traverse the full tissue cross-section, including deep arteries (radial, ulnar, digital arteries with diameters of 1-4 mm). The pulsatile signal originates from blood volume changes in these larger arteries plus the arteriolar bed. The AC/DC ratio is typically 2-5% at the fingertip, reflecting the substantial arterial blood volume in the optical path.
Reflectance: Photons sample only the superficial vascular bed, primarily arterioles and capillaries with diameters of 10-100 um. The AC/DC ratio is typically 0.5-2% at the wrist and 1-3% at the fingertip in reflectance mode. The smaller pulsatile signal is a direct consequence of the smaller arterial blood volume in the shallow interrogation zone.
As Reisner et al. (2008) note in their review, the relation between the PPG and the underlying circulation is complicated by optical, biomechanical, and physiologic covariates, so measurement geometry matters (doi:10.1097/ALN.0b013e31816c89e1).
Signal Quality Comparison
Pulsatile Signal Amplitude (AC/DC Ratio)
The AC/DC ratio, also called the perfusion index (PI), is the primary metric for PPG signal quality. It represents the ratio of the pulsatile (cardiac-driven) component to the quasi-static (DC) component of the detected light.
Typical AC/DC ratios by mode and body site:
Scroll horizontally if needed
| Body Site | Transmittance | Reflectance |
|---|---|---|
| Fingertip | 2-5% | 1-3% |
| Earlobe | 1-3% | 0.5-2% |
| Wrist | N/A (too thick) | 0.5-2% |
| Forehead | N/A (skull) | 1-2% |
| Toe | 1.5-4% | 0.5-2% |
These values represent healthy adults at rest with adequate perfusion. In conditions of poor perfusion (hypothermia, shock, peripheral vascular disease), reflectance PPG signal amplitudes can drop by 80-95%, while transmittance amplitudes are more robust because the deeper arterial path provides a more stable signal source.
Signal-to-Noise Ratio
SNR in PPG is determined by the AC signal amplitude relative to noise sources including photodetector shot noise, amplifier noise, ambient light interference, and motion artifacts. Transmittance mode has inherent SNR advantages because:
- Higher AC signal amplitude (2-5x higher as noted above)
- More stable optical coupling (clip-on sensors maintain consistent contact pressure)
- Better ambient light rejection (the tissue itself acts as a shield, blocking ambient light from reaching the detector)
Motion Artifact Susceptibility
Motion artifacts affect both modes but through different mechanisms:
Transmittance: The primary motion artifact mechanism is sensor displacement relative to the tissue, which modulates the optical path length. In clip-on finger sensors, the spring mechanism maintains relatively stable contact, limiting artifact amplitude during mild motion. However, during vigorous hand movement, the changing venous blood distribution in the finger and the mechanical coupling between finger and clip create significant artifacts.
Reflectance: Motion artifacts arise from sensor-skin relative displacement, changing contact pressure, tissue deformation, and venous blood redistribution. The reflectance geometry is inherently more sensitive to these effects because the source-detector separation is small (3-10 mm), and even sub-millimeter shifts in sensor position can significantly alter the detected signal. Wrist-worn reflectance sensors are particularly susceptible during activities involving forearm rotation (typing, turning doorknobs) and during running where arm swing creates periodic artifacts. For a comprehensive treatment of motion artifact removal algorithms, see our motion artifact removal guide.
SpO2 Measurement Accuracy
Transmittance SpO2: The Clinical Standard
Transmittance pulse oximetry at the fingertip is the established clinical standard for noninvasive SpO2 measurement, with a performance requirement of ARMS (root mean square accuracy) of 3% or better over the 70-100% SpO2 range per ISO 80601-2-61. Modern FDA-cleared finger pulse oximeters typically achieve ARMS of 1.5-2.5% across diverse populations.
The SpO2 calculation relies on the ratio of ratios (R):
SpO2 is then estimated using an empirically derived calibration curve relating R to SaO2 (arterial oxygen saturation measured by co-oximetry). In transmittance mode, the optical path through the arterial bed is well-defined and relatively consistent across individuals, making the calibration curve transferable across patients.
Severinghaus and Kelleher (1992) reviewed the development and accuracy limits of transmittance pulse oximetry (doi:10.1097/00000542-199206000-00024).
Reflectance SpO2: Emerging but Challenging
Reflectance SpO2 at the wrist is used by devices including Apple Watch, Samsung Galaxy Watch, and Garmin Venu, but with substantially lower accuracy than transmittance fingertip oximetry. Key challenges include:
Lower pulsatile amplitude: The AC components at both red and infrared wavelengths are smaller in reflectance mode, making the R ratio calculation more susceptible to noise. Small errors in AC measurement produce proportionally larger errors in the R ratio and thus in SpO2.
Different optical path: In reflectance mode, the optical path does not traverse large arteries. The pulsatile signal originates primarily from arterioles and capillaries, where the effective oxygen saturation may differ from large-artery SaO2 due to oxygen extraction in the capillary bed. This introduces a systematic bias that must be accounted for in calibration.
Variable LED-detector geometry: Contact pressure variations at the wrist change the effective source-detector separation and the interrogation depth, altering the R ratio independently of SpO2 changes. This geometric sensitivity is a major source of reflectance SpO2 error.
Body Site Constraints
Transmittance-Compatible Sites
Transmittance PPG is physically limited to body sites where tissue is thin enough for detectable light transmission. At red and infrared wavelengths (660/940 nm), maximum usable tissue thickness is approximately 10-15 mm. At green wavelengths (525 nm), the higher tissue attenuation limits transmittance to even thinner tissue, typically under 5-8 mm.
Practical transmittance sites include:
- Fingertip: 8-15 mm thickness. The primary clinical site. Both digit orientation (across the nail bed or across the finger pad) work, with the nail bed orientation providing slightly higher SNR.
- Earlobe: 3-8 mm thickness. Excellent for monitoring in clinical settings, operating rooms, and sleep studies. Less affected by peripheral vasoconstriction.
- Toe: 10-18 mm thickness in adults. Similar signal quality to fingertip. Used when fingers are unavailable (burns, trauma) or for multi-site PTT measurement.
- Nasal septum: 2-5 mm thickness. Excellent signal quality but impractical for ambulatory monitoring.
- Neonatal foot/hand: 3-8 mm thickness. Standard site for neonatal pulse oximetry due to small tissue dimensions.
Reflectance-Accessible Sites
Reflectance PPG can theoretically be performed on any body surface with sufficient superficial blood perfusion, making it far more versatile for wearable applications:
- Wrist (dorsal): The standard consumer wearable site. Signal quality depends heavily on sensor placement, contact pressure, and individual anatomy.
- Forehead: Increasingly used in clinical monitoring, particularly for patients with poor peripheral perfusion. The temporal artery branch provides consistent signal.
- Upper arm: Used in some armband devices. Lower motion artifact than wrist during running.
- Chest: Good signal quality with minimal motion artifact in resting conditions. Used in chest-strap monitors.
- Behind the ear: Emerging site for hearable devices. Relatively low motion artifact and good perfusion.
For how body site selection affects overall system design, including power consumption considerations, the choice between reflectance and transmittance has significant implications for LED drive requirements and battery life.
Design Tradeoffs for Wearable Devices
Optical Geometry Optimization in Reflectance Mode
Since wearable devices are largely constrained to reflectance mode (with the exception of ring-form-factor devices that can use transmittance on the finger), optimizing the reflectance optical geometry is critical.
Source-detector separation: Increasing the separation increases the average interrogation depth and can increase the pulsatile component by sampling deeper arteries. However, detected intensity drops exponentially with separation, requiring higher LED drive currents. The separation is therefore a trade-off between interrogation depth and signal level (see Asada et al., 2003, for a review of wearable PPG sensor design; doi:10.1109/MEMB.2003.1213624).
Multiple photodetectors: Using multiple photodetectors at different distances from the LED enables depth-resolved measurements. The near detector (2-3 mm separation) captures primarily superficial tissue, while the far detector (5-8 mm separation) captures deeper tissue including larger arterioles. Subtracting or ratioing the two signals can improve the AC/DC ratio and reduce surface-layer artifacts.
LED arrangement: Surrounding the photodetector with multiple LEDs (typically 2-4 LEDs in a symmetric arrangement) improves spatial averaging and reduces sensitivity to localized perfusion variations and sensor tilt. Most commercial wrist PPG sensors use this multi-LED topology.
Ring-Form Factor: The Transmittance Exception
Ring-form devices (Oura Ring, Samsung Galaxy Ring, RingConn) represent a unique case where transmittance or semi-transmittance PPG is possible in a wearable form factor. The finger base has a thickness of 15-22 mm, which is at the upper limit for infrared transmittance. Some ring devices use a hybrid geometry where LEDs and detectors are positioned to capture light that has traversed the thinner lateral portions of the finger rather than the full dorsal-palmar thickness.
Ring PPG can be highly accurate at rest. Kinnunen et al. (2020) compared the Oura ring with ECG in 49 adults and found very high agreement for nightly average heart rate and HRV (r^2 = 0.996 and 0.980; mean bias -0.63 bpm and -1.2 ms) (doi:10.1088/1361-6579/ab840a). For an analysis of Oura Ring accuracy data, see our Oura Ring accuracy review.
Reflectance SpO2 Calibration Challenges
Calibrating reflectance SpO2 is fundamentally more challenging than transmittance because the optical path is less well-defined and more variable between individuals. Key calibration challenges include:
Population variability: The relationship between the R ratio and SpO2 varies more across individuals in reflectance mode due to differences in subcutaneous fat thickness, melanin content, and superficial vascular anatomy. This requires either larger calibration cohorts or individual calibration.
Body site dependence: The R-SpO2 calibration curve differs between body sites in reflectance mode because the arterio-venous composition of the sampled tissue varies. A calibration derived at the forehead does not directly transfer to the wrist without adjustment.
Contact pressure sensitivity: Increasing contact pressure compresses the superficial vasculature, altering both the DC baseline and the AC pulsatile component in a wavelength-dependent manner. This effectively shifts the R ratio independently of SpO2, introducing a systematic error source not present in transmittance mode with consistent clip pressure.
Hybrid and Emerging Approaches
Multi-Distance Reflectance for Enhanced Depth Resolution
Advanced reflectance sensors use multiple source-detector separations to reconstruct depth-resolved tissue optical properties, effectively mimicking some advantages of transmittance mode. Spatially resolved spectroscopy (SRS) uses the slope of reflectance versus source-detector separation to estimate the tissue absorption coefficient independently of scattering, enabling more robust SpO2 estimation.
Green Reflectance for Heart Rate, Red/IR Transmittance for SpO2
Some devices implement a hybrid approach where green reflectance PPG is used for continuous heart rate monitoring (leveraging its superior AC amplitude at the wrist) while red/infrared is used only for periodic SpO2 measurements. This allows the device to optimize each measurement modality independently, using higher LED drive currents and longer integration times for the less frequent SpO2 measurements.
Conclusion
The choice between reflectance and transmittance PPG is primarily determined by body site geometry rather than inherent superiority of either mode. Transmittance remains the clinical standard for SpO2 at the fingertip, where it achieves accuracy that reflectance has not yet matched in the wearable form factor. Reflectance mode enables PPG measurement at virtually any body site, making it the foundation of the wrist-worn wearable industry, but with tradeoffs in signal quality, SpO2 accuracy, and motion artifact susceptibility. For engineers designing PPG systems, understanding these tradeoffs and selecting the appropriate optical geometry, LED drive strategy, and signal processing algorithms for the chosen mode is essential for achieving target performance specifications.
References
- Delpy, D. T., et al. (1988). Estimation of optical pathlength through tissue from direct time of flight measurement. Physics in Medicine and Biology, 33(12), 1433-1442. https://doi.org/10.1088/0031-9155/33/12/008
- Schmitt, J. M. (1991). Simple photon diffusion analysis of the effects of multiple scattering on pulse oximetry. IEEE Transactions on Biomedical Engineering, 38(12), 1194-1203. https://doi.org/10.1109/10.137285
- Reisner, A., Shaltis, P. A., McCombie, D., & Asada, H. H. (2008). Utility of the photoplethysmogram in circulatory monitoring. Anesthesiology, 108(5), 950-958. https://doi.org/10.1097/ALN.0b013e31816c89e1
- Severinghaus, J. W., & Kelleher, J. F. (1992). Recent developments in pulse oximetry. Anesthesiology, 76(6), 1018-1038. https://doi.org/10.1097/00000542-199206000-00024
- Asada, H. H., Shaltis, P., Reisner, A., Rhee, S., & Hutchinson, R. C. (2003). Mobile monitoring with wearable photoplethysmographic biosensors. IEEE Engineering in Medicine and Biology Magazine, 22(3), 28-40. https://doi.org/10.1109/MEMB.2003.1213624
- Kinnunen, H., Rantanen, A., Kentta, T., & Koskimaki, H. (2020). Feasible assessment of recovery and cardiovascular health: accuracy of nocturnal HR and HRV assessed via ring PPG in comparison to medical grade ECG. Physiological Measurement, 41(4), 04NT01. https://doi.org/10.1088/1361-6579/ab840a
Related articles
PPG Wearable Form Factors: Ring, Patch, Earbud, and Headband Sensor Design
**The body location where a PPG sensor is worn fundamentally determines its signal quality, motion artifact susceptibility, power budget, and clinical...
How PPG Wearables Are Validated in Clinical Trials: Methods and Standards
How are PPG wearables validated clinically? Learn the study designs, statistical methods, and regulatory standards used to assess wearable heart rate device accuracy.
PPG Heart Rate Sensor Explained: Optical Modules, Multi-LED Design, and Motion Compensation
How PPG heart rate sensors work inside wearables. Learn about multi-LED arrays, ambient light rejection, accelerometer fusion, and sensor module design.
Photoplethysmography Sensor: Types, Design, and Selection Guide
Everything you need to know about photoplethysmography sensors: LED wavelengths, photodetector types, analog front-ends, form factors, and how to choose the right sensor for your application.
PPG Inter-Beat Interval Accuracy: IBI Precision vs ECG Gold Standard
**Inter-beat interval (IBI) measurement from photoplethysmography achieves mean absolute errors of 2-10 ms compared to ECG under resting conditions, b...
Devices in this article
Research records with the datasets, papers and published validation results for each device.