Objective Pain Assessment with PPG: Measuring Pain from Photoplethysmography Signals
**Pain assessment remains one of medicine's most persistent challenges: it is inherently subjective, difficult to communicate for many patients, and i...
- PPG & Signal Processing
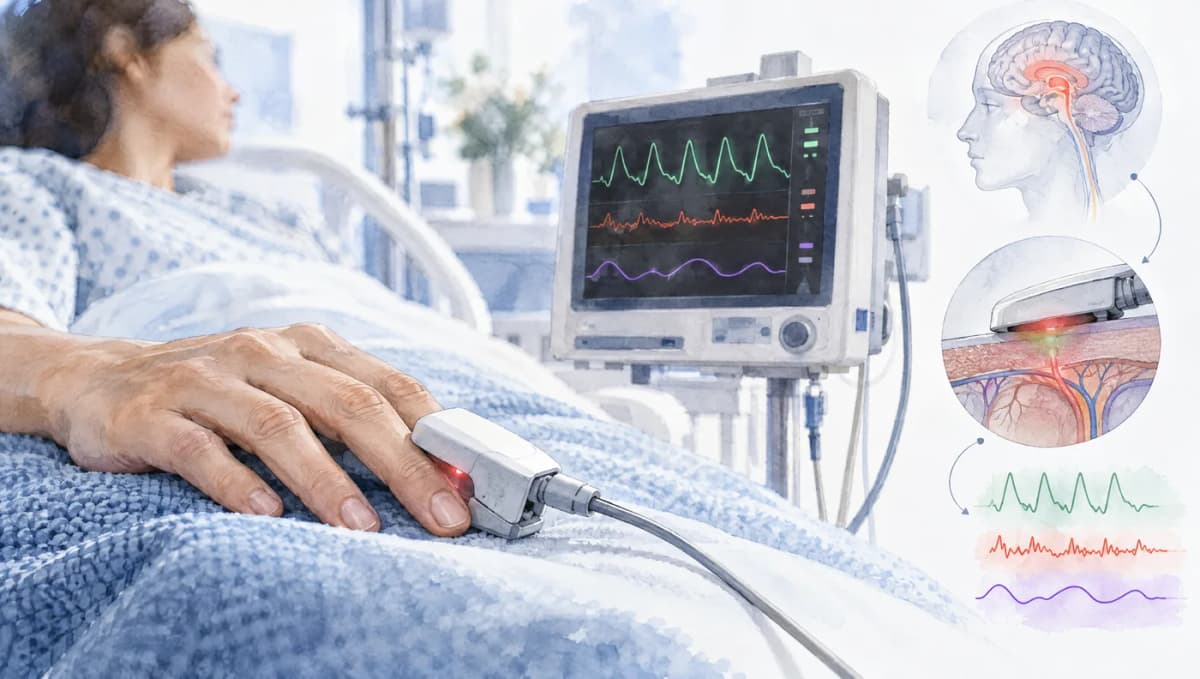
Pain assessment remains one of medicine's most persistent challenges: it is inherently subjective, difficult to communicate for many patients, and impossible to self-report for those who are anesthetized, sedated, cognitively impaired, or preverbal. The quest for objective pain measurement has led researchers and clinicians to photoplethysmography, which captures autonomic nervous system responses to nociceptive stimuli through changes in heart rate, heart rate variability, and peripheral vascular tone. PPG-derived pain indices are now commercially available in surgical monitoring systems and under active investigation for broader clinical application.
This article examines the physiological basis of PPG-based pain assessment, the established clinical indices (SPI, ANI), emerging machine learning approaches, validation evidence, clinical utility, and the fundamental limitations inherent in attempting to objectively measure a subjective experience. For background on PPG technology, see our introduction to photoplethysmography.
The Physiology of Pain and Autonomic Responses
Nociception versus Pain
A critical distinction underpins all work in this field: nociception is not pain. Nociception is the neural process of detecting and encoding noxious (tissue-damaging or potentially damaging) stimuli through specialized sensory neurons called nociceptors. Pain is the subjective, conscious experience that may or may not result from nociception. Pain involves cortical processing, emotional evaluation, memory, and cognitive interpretation.
This distinction matters because PPG measures peripheral autonomic responses that correlate with nociceptive input, not with the subjective experience of pain. An anesthetized patient receiving a surgical incision exhibits nociceptive autonomic responses (tachycardia, vasoconstriction) without experiencing pain. Conversely, a patient with chronic neuropathic pain may experience severe pain with minimal autonomic activation due to autonomic habituation.
Autonomic Responses to Nociception
Acute nociceptive stimulation triggers a sympathetic stress response through spinal and brainstem reflex pathways:
Cardiovascular responses:
- Heart rate increase of 5-20 bpm (via sympathetic cardiac acceleration and vagal withdrawal)
- Blood pressure increase of 10-30 mmHg (via sympathetic vasoconstriction and increased cardiac output)
- Peripheral vasoconstriction (sympathetically mediated reduction in skin and muscle blood flow)
- Decreased heart rate variability (parasympathetic withdrawal)
PPG-detectable changes:
- Decreased pulse wave amplitude (PPA reduction of 15-50% during noxious stimulation)
- Increased heart rate (shortened inter-beat intervals)
- Reduced HRV (decreased RMSSD, HF power)
- Altered pulse waveform morphology (steeper systolic rise, reduced dicrotic notch)
- Decreased pulse transit time (reflecting blood pressure increase)
These responses are mediated by the same sympatho-adrenal pathway involved in the general stress response, which is why PPG-based nociception indices overlap substantially with stress indices. For a detailed discussion of PPG-based stress detection, see our article on PPG stress detection methods.
Modulation by Analgesia and Anesthesia
Analgesic drugs (opioids, regional anesthetics, non-opioid analgesics) reduce nociceptive autonomic responses in a dose-dependent manner. This creates the clinical rationale for PPG-based nociception monitoring during anesthesia: if the PPG signal shows significant autonomic activation during surgery, the current analgesia may be insufficient.
Opioids attenuate nociceptive autonomic responses through multiple mechanisms: direct suppression of spinal nociceptive transmission, inhibition of brainstem sympathetic outflow, and vagal enhancement. At adequate analgesic doses, the PPG pulse wave amplitude remains stable and heart rate variability is maintained during surgical stimulation. At inadequate doses, noxious stimulation produces the vasoconstriction and tachycardia described above.
Established PPG-Based Pain/Nociception Indices
Surgical Pleth Index (SPI)
The Surgical Pleth Index (SPI), formerly known as the Surgical Stress Index (SSI), was developed by GE Healthcare and introduced by Huiku et al. (2007) (doi:10.1093/bja/aem004). SPI is calculated from two PPG-derived parameters obtained from finger pulse oximetry:
Components:
- Heartbeat interval (HBI): The pulse-to-pulse interval derived from the PPG waveform, inversely related to heart rate.
- Photoplethysmographic pulse wave amplitude (PPGA): The AC amplitude of the PPG signal, reflecting peripheral vascular tone.
Both components are normalized, and the index was originally defined (as the Surgical Stress Index) as:
The weighting emphasizes PPGA because pulse wave amplitude is more specifically affected by nociceptive sympathetic activation than heart rate, which responds to many non-nociceptive stimuli.
Interpretation: SPI ranges from 0 to 100, with higher values indicating a stronger sympathetic response to nociceptive stimulation. Huiku et al. (2007) showed that the index rose at skin incision and fell at higher remifentanil concentrations, so changes within a patient are more informative than any single value.
Validation evidence: Gruenewald et al. (2009) (doi:10.1093/bja/aep206) studied the surgical stress index response to tetanic stimulation under sevoflurane anesthesia at different remifentanil concentrations in 24 patients.
In a randomized controlled trial (n = 170), Bergmann et al. (2013) (doi:10.1093/bja/aes426) found that SPI-guided analgesia management reduced remifentanil and propofol consumption and shortened time to extubation compared to standard practice, with no difference in postoperative pain scores.
Analgesia Nociception Index (ANI)
The Analgesia Nociception Index (ANI), developed by MDoloris Medical Systems, is derived from the parasympathetic component of PPG or ECG heart rate variability (Jeanne et al., 2012; doi:10.1007/s10877-012-9354-0). ANI quantifies the respiratory influence on heart rate, which reflects parasympathetic (vagal) tone:
Principle: During adequate analgesia, parasympathetic tone is preserved and respiratory sinus arrhythmia (RSA) produces clear HF modulation of the heart rate. During nociceptive stimulation with inadequate analgesia, sympathetic activation suppresses parasympathetic tone, reducing RSA amplitude.
Calculation: ANI analyzes the HF component (0.15-0.50 Hz) of the RR interval series over a moving 64-second window, normalizing it to a 0-100 scale:
- ANI 50-100: Adequate analgesia, preserved parasympathetic tone
- ANI 30-50: Borderline, possible nociception
- ANI 0-30: Inadequate analgesia, significant nociceptive response
Clinical studies have evaluated ANI for predicting hemodynamic responses to surgical stimulation, though validation data varies across different patient populations and surgical contexts.
Ledowski et al. (2014) (doi:10.1111/aas.12216) evaluated ANI in 30 patients and found that ANI decreased with airway manipulation and skin incision but had limited ability to predict hemodynamic responses.
Newborn Infant Parasympathetic Evaluation (NIPE)
A specialized application of the ANI algorithm, the NIPE index (MDoloris Medical Systems) is designed for neonatal pain assessment. Neonates cannot self-report pain, and behavioral pain scales (NIPS, PIPP) have significant inter-observer variability.
Faye et al. (2010) studied 28 newborn infants after major surgery and found that a high-frequency HRV index (the precursor of NIPE) was significantly lower in infants with high postoperative pain scores (EDIN >= 5) than in those with low scores.
Machine Learning Approaches to PPG-Based Pain Assessment
Feature Engineering for Pain Classification
Beyond SPI and ANI, researchers have explored multimodal physiological feature sets for pain classification.
Werner et al. (2014) (doi:10.1109/icpr.2014.784) combined facial video with biomedical signals (EMG, skin conductance, ECG) from the BioVid Heat Pain Database for automatic pain recognition, showing that multimodal fusion improved recognition over single modalities.
Deep Learning
Recent work has applied deep learning directly to raw physiological signals, bypassing manual feature engineering.
Thiam et al. (2019) designed deep learning architectures on raw physiological signals (EDA, ECG, EMG) from the BioVid Heat Pain Database. Their EDA-only model and deep-fusion models reached average accuracies of 84.57% and 84.40% for baseline vs. pain-tolerance classification under leave-one-subject-out validation, outperforming previous hand-crafted-feature methods. Notably, EDA rather than cardiac signals carried most of the discriminative information.
Lopez-Martinez and Picard (2018) (doi:10.1109/embc.2018.8513575) used recurrent neural networks to estimate continuous pain intensity from autonomic signals including skin conductance and heart rate variability.
Multi-Modal Pain Assessment
PPG alone captures only the autonomic component of pain. Combining PPG with other modalities improves pain assessment:
- PPG + EDA (electrodermal activity): EDA captures sympathetic cholinergic sudomotor responses that are independent of the sympathetic adrenergic responses captured by PPG. Combining both modalities can improve pain classification performance.
- PPG + EMG (electromyography): Facial EMG captures pain-related muscle activation (corrugator, zygomaticus) that is mechanistically distinct from autonomic responses.
- PPG + facial video: Computer vision-based facial action unit detection combined with PPG provides complementary behavioral and physiological pain information.
Clinical Applications and Evidence
Intraoperative Nociception Monitoring
The primary clinical application of PPG-based pain assessment is guiding analgesic administration during general anesthesia. The clinical goal is maintaining adequate analgesia without overdosing, which causes hypotension, delayed recovery, and respiratory depression.
Multiple randomized controlled trials have evaluated nociception index-guided analgesia management. Studies generally report that nociception-guided approaches can reduce intraoperative opioid consumption and hemodynamic instability while maintaining adequate analgesia, though the magnitude of benefit varies across different surgical contexts and patient populations.
ICU Pain Assessment
Critically ill patients in the ICU are frequently unable to self-report pain due to sedation, mechanical ventilation, or cognitive impairment. Current practice relies on behavioral pain scales (BPS, CPOT) that require trained nurses and provide only intermittent assessment.
Continuous PPG-based nociception monitoring could supplement behavioral assessment in the ICU. Ben-Israel et al. (2013) (doi:10.1007/s10877-013-9487-9) developed a multi-parameter nociception level index in 25 surgical patients under general anesthesia. Validation of such indices in ICU populations remains limited.
Neonatal Pain Assessment
Neonates, particularly premature infants, experience numerous painful procedures during NICU stay (heel lances, IV insertions, intubation) and may be inadequately treated due to difficulty assessing their pain. PPG-based indices offer continuous, objective supplementation of behavioral assessment.
Cremillieux et al. (2018) (doi:10.1002/ejp.1191) evaluated the NIPE index in 29 premature neonates during heel lance but found that NIPE did not correlate reliably with behavioral pain scales and was judged unreliable for acute pain assessment in this population.
Chronic Pain Monitoring
PPG-based pain assessment is least validated for chronic pain, where the relationship between nociception and autonomic activation is weakest. Chronic pain patients often show:
- Autonomic habituation (blunted autonomic responses to ongoing pain)
- Central sensitization (pain without peripheral nociceptive input)
- Autonomic dysfunction (baseline autonomic abnormalities confounding interpretation)
- Medication effects (opioids, gabapentinoids, antidepressants alter autonomic function)
Limited evidence suggests that PPG-derived HRV may serve as a biomarker for pain-related autonomic burden in chronic pain populations. A meta-analysis by Tracy et al. (2016) found a consistent moderate-to-large reduction in high-frequency HRV across chronic pain conditions (heavily influenced by fibromyalgia studies), though this likely reflects general autonomic dysregulation rather than pain intensity per se.
For information on autonomic assessment via PPG, see our article on PPG autonomic function testing.
Limitations and Ethical Considerations
Fundamental Measurement Limitations
PPG-based pain indices face several irreducible limitations:
Specificity: Autonomic responses to pain are not distinguishable from autonomic responses to anxiety, stress, fever, hypovolemia, bladder distension, or many other stimuli. Any factor activating the sympathetic nervous system will alter SPI, ANI, and similar indices regardless of whether pain is present.
Sensitivity to medications: Beta-blockers, alpha-agonists (clonidine, dexmedetomidine), anticholinergics (atropine, glycopyrrolate), and vasopressors directly affect the cardiovascular parameters that PPG-based pain indices measure, independently of nociception.
Individual variability: Pain sensitivity, autonomic reactivity, and analgesic requirements vary enormously between individuals. Population-level calibrations provide only rough estimates for any individual patient.
Chronic pain insensitivity: PPG indices primarily capture acute nociceptive responses and have limited sensitivity to chronic pain states where autonomic habituation has occurred.
Ethical Considerations
The pursuit of objective pain measurement raises important ethical questions. Pain is fundamentally a subjective experience, and patients' self-reports should remain the primary basis for pain management decisions when available. PPG-based indices should supplement, not replace, patient communication.
There is a risk that objective pain indices could be used to discredit patient pain reports (if the index reads low, is the patient's complaint dismissed?). Clinical guidelines should ensure that pain indices are used to detect under-reported pain (in non-communicative patients) rather than to override self-reported pain.
Our conditions page provides additional context on how various health conditions affect pain processing and PPG signals.
Future Directions
Multi-Wavelength Pain Assessment
Different PPG wavelengths probe different tissue depths and vascular beds. Multi-wavelength PPG arrays could simultaneously capture superficial cutaneous vasoconstriction and deeper muscular vascular responses to pain, potentially improving specificity. For background on wavelength selection, see our article on green vs. red vs. infrared PPG.
Integration with Other Biomarkers
Combining PPG-derived autonomic pain indices with other objective biomarkers, including pupillometry (pupil dilation reflex), skin conductance (sudomotor response), and EEG-based pain signatures, could create multi-modal pain assessment systems with improved accuracy and specificity.
Personalized Pain Models
Individual calibration using brief standardized pain stimuli (pressure algometry, electrical stimulation) could establish person-specific relationships between nociceptive input and PPG response, enabling personalized pain scoring that accounts for individual autonomic reactivity. This personalized approach, combined with continuous learning from clinical outcomes, represents the most promising path toward clinically useful objective pain assessment through PPG-based health monitoring algorithms.
Conclusion
PPG-based pain assessment provides a window into the autonomic component of nociception, capturing the sympathetic activation and parasympathetic withdrawal that accompany acute noxious stimulation. Established indices like SPI and ANI have demonstrated clinical utility in guiding intraoperative analgesia, reducing opioid consumption, and supplementing pain assessment in non-communicative patients. However, fundamental limitations in specificity, sensitivity to confounders, and individual variability prevent PPG from serving as a standalone pain measurement tool. The technology is most valuable when understood for what it truly measures: not pain itself, but the body's autonomic response to nociceptive input, a physiological correlate that, combined with clinical context and patient communication, can improve pain management decisions.
References
- Huiku, M., et al. (2007). Assessment of surgical stress during general anaesthesia. British Journal of Anaesthesia, 98(4), 447-455. https://doi.org/10.1093/bja/aem004
- Gruenewald, M., et al. (2009). Influence of different remifentanil concentrations on the performance of the surgical stress index to detect a standardized painful stimulus during sevoflurane anaesthesia. British Journal of Anaesthesia, 103(4), 586-593. https://doi.org/10.1093/bja/aep206
- Bergmann, I., et al. (2013). Surgical pleth index-guided remifentanil administration reduces remifentanil and propofol consumption and shortens recovery times in outpatient anaesthesia. British Journal of Anaesthesia, 110(4), 622-628. https://doi.org/10.1093/bja/aes426
- Ledowski, T., et al. (2014). Analgesia Nociception Index (ANI) to predict intraoperative haemodynamic changes: results of a pilot investigation. Acta Anaesthesiologica Scandinavica, 58(1), 74-79. https://doi.org/10.1111/aas.12216
- Jeanne, M., et al. (2012). Variations of the analgesia nociception index during general anaesthesia for laparoscopic abdominal surgery. Journal of Clinical Monitoring and Computing, 26(4), 289-294. https://doi.org/10.1007/s10877-012-9354-0
- Faye, P. M., et al. (2010). Newborn infant pain assessment using heart rate variability analysis. The Clinical Journal of Pain, 26(9), 777-782. https://doi.org/10.1097/AJP.0b013e3181ed1058
- Werner, P., Al-Hamadi, A., Niese, R., et al. (2014). Automatic pain recognition from video and biomedical signals. 22nd International Conference on Pattern Recognition, 4582-4587. https://doi.org/10.1109/ICPR.2014.784
- Thiam, P., et al. (2019). Exploring deep physiological models for nociceptive pain recognition. Sensors, 19(20), 4503. https://doi.org/10.3390/s19204503
- Lopez-Martinez, D., & Picard, R. (2018). Continuous pain intensity estimation from autonomic signals with recurrent neural networks. 40th Annual International Conference of the IEEE EMBC, 5624-5627. https://doi.org/10.1109/EMBC.2018.8513575
- Ben-Israel, N., et al. (2013). Monitoring the nociception level: a multi-parameter approach. Journal of Clinical Monitoring and Computing, 27(6), 659-668. https://doi.org/10.1007/s10877-013-9487-9
- Cremillieux, C., et al. (2018). Objective assessment of induced acute pain in neonatology with the Newborn Infant Parasympathetic Evaluation index. European Journal of Pain, 22(6), 1071-1079. https://doi.org/10.1002/ejp.1191
- Tracy, L. M., et al. (2016). Meta-analytic evidence for decreased heart rate variability in chronic pain implicating parasympathetic nervous system dysregulation. Pain, 157(1), 7-29. https://doi.org/10.1097/j.pain.0000000000000360
Related articles
PPG in Veterinary Medicine: Animal Health Monitoring with Photoplethysmography
PPG is widely used in veterinary medicine for pulse oximetry, anesthesia monitoring, and heart rate measurement across animal species. Wearable PPG de...
PPG Vascular Age Assessment: Arterial Stiffness Measurement from Pulse Wave Analysis
**Arterial stiffness is one of the earliest detectable markers of cardiovascular disease, and the PPG waveform encodes surprisingly rich information a...
PPG Respiratory Rate Estimation: Extracting Breathing Rate from Photoplethysmography
**Respiratory rate is the vital sign most sensitive to clinical deterioration, yet it is the least frequently and least accurately recorded in routine...
History of Photoplethysmography: From 1930s Invention to Modern Wearables
**Photoplethysmography (PPG) has undergone one of the most remarkable transformations in biomedical sensing history -- from a laboratory curiosity bui...
PPG for Emotion Recognition: Affective Computing with Photoplethysmography
**Emotions are not purely cognitive events -- they are embodied physiological states that leave measurable traces in cardiovascular signals.** Fear ac...