PPG Ballistocardiography Comparison
Ballistocardiography (BCG) and photoplethysmography (PPG) represent two fundamentally different approaches to non-invasive cardiac monitoring. PPG det...
- PPG & Signal Processing
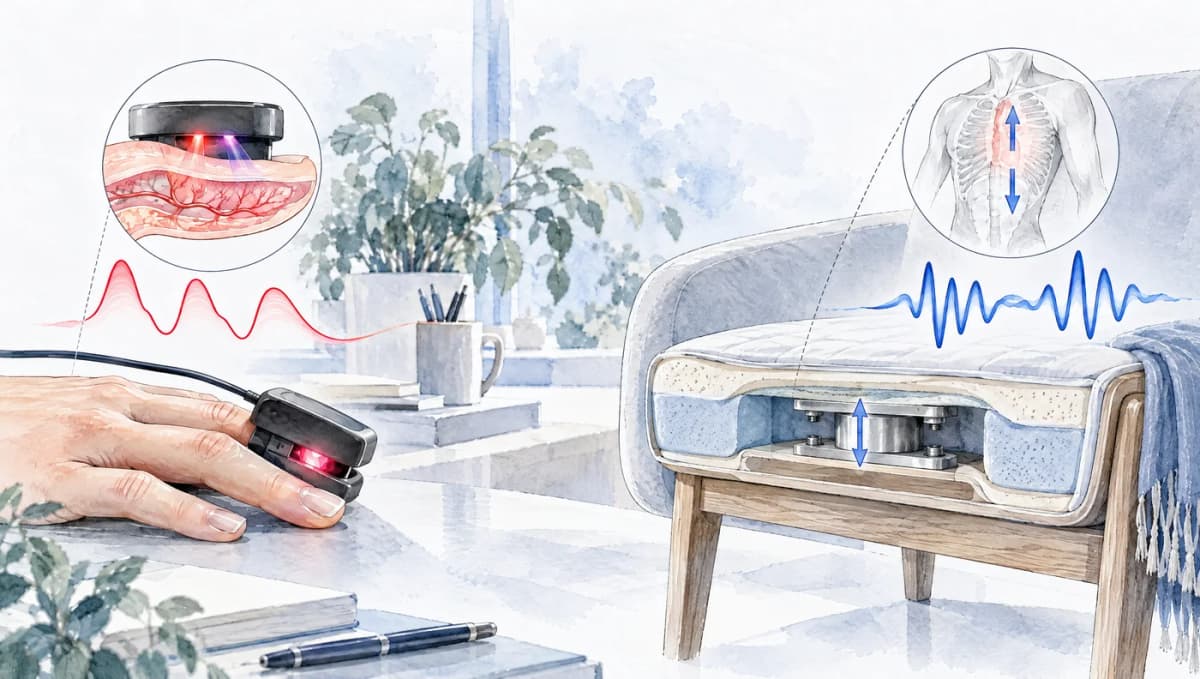
Ballistocardiography (BCG) and photoplethysmography (PPG) represent two fundamentally different approaches to non-invasive cardiac monitoring. PPG detects blood volume changes optically by measuring light absorption modulation in peripheral tissue, as described in our comprehensive PPG guide. BCG detects the whole-body recoil forces generated by cardiac contraction and blood ejection into the vasculature. These are complementary measurements: PPG captures the hemodynamic propagation of the pulse wave through peripheral arteries, while BCG captures the mechanical forces generated at the heart itself.
This article provides a detailed technical comparison of BCG and PPG, examining their physical principles, signal characteristics, measurement capabilities, accuracy, and practical applications. Understanding the strengths and limitations of each modality is essential for researchers and engineers designing cardiac monitoring systems, as the optimal choice depends critically on the application context, form factor constraints, and required physiological parameters.
Physical Principles
Ballistocardiography
BCG was first described by Gordon in 1877 and extensively characterized by Starr et al. in 1939, predating modern PPG by decades (Starr et al., 1939; doi:10.1152/ajplegacy.1939.127.1.1). The physical basis is Newton's third law: when the heart ejects blood into the aorta during systole, the body experiences an equal and opposite reaction force. As blood accelerates headward through the aortic arch and then decelerates as it distributes through the arterial tree, the body undergoes a complex pattern of micro-accelerations and micro-displacements.
The BCG signal reflects the net force exerted by moving blood masses on the body. The peak-to-peak displacement of the body's center of mass during a single cardiac cycle is approximately 10-50 micrometers, corresponding to accelerations of 1-10 milligravity (mg). The BCG waveform contains characteristic waves labeled H through N (following Starr's nomenclature), where the H-I-J complex corresponds to ventricular ejection and the K-L-M-N complex corresponds to the filling phases and valve movements.
The BCG signal amplitude is directly related to cardiac contractility and stroke volume because the reaction force is proportional to the rate of momentum transfer to the ejected blood. This relationship gives BCG a unique capability not shared by PPG: the potential to assess cardiac output and contractile function non-invasively.
Photoplethysmography
PPG measures the peripheral manifestation of the cardiac cycle rather than the central mechanical event. Each heartbeat generates a pressure wave that propagates through the arterial tree at 5-15 m/s (depending on arterial stiffness), arriving at the fingertip or wrist approximately 100-300 ms after the R-wave on ECG. The pressure wave causes arterial distension, increasing the local blood volume and modulating light absorption as detected by the PPG sensor.
The PPG waveform morphology is shaped by the arterial pressure wave, its reflections from peripheral vascular bifurcations and impedance mismatches, and the local vascular compliance. This makes PPG sensitive to vascular health, arterial stiffness, and autonomic nervous system tone, providing information that BCG does not directly capture.
Temporal Relationship
The BCG signal precedes the peripheral PPG signal because it is generated at the heart (the source of the pressure wave), while PPG is measured at the periphery (after the pressure wave has propagated through the vasculature). The time delay between the BCG J-wave and the PPG systolic peak represents a form of pulse transit time (PTT) that correlates with blood pressure. Combining the two modalities therefore offers a route to cuffless blood pressure estimation (see the Blood Pressure section below).
Signal Characteristics Comparison
Frequency Content
BCG and PPG signals contain energy in similar frequency bands but with different spectral distributions. The cardiac fundamental frequency (heart rate) is present in both signals, but the harmonic content differs.
BCG signals have significant energy at higher harmonics of the cardiac frequency because the sharp acceleration/deceleration events produce waveform features with fast temporal transitions. The useful frequency content of BCG extends to approximately 20-25 Hz, requiring sampling rates of at least 50 Hz for adequate representation. Low-frequency content below 0.5 Hz includes respiratory modulation and postural drift.
PPG signals have more energy concentrated at the fundamental cardiac frequency, with harmonics decreasing more rapidly. The useful bandwidth of PPG is approximately 0.5-15 Hz for waveform morphology analysis, though heart rate extraction requires only 0.5-4 Hz. The spectral characteristics of PPG at different wavelengths vary, with green PPG showing the strongest pulsatile component at the wrist.
Signal-to-Noise Ratio
The SNR of BCG and PPG signals differs dramatically depending on the measurement context. At rest in a supine position, bed-mounted BCG achieves excellent SNR because the entire body mass participates in the measurement and environmental vibration can be isolated. Inan et al. (2015) review how newer instrumentation and signal processing have reduced BCG measurement noise and enabled measurement outside the clinic, in the home, in the field, and even in microgravity (doi:10.1109/JBHI.2014.2361732).
PPG SNR depends on the measurement site, wavelength, and sensor design. Finger-clip transmission-mode PPG generally achieves higher SNR than wrist-based reflectance-mode PPG, which has a lower pulsatile signal amplitude and greater susceptibility to motion artifacts.
Motion Artifact Susceptibility
This is where the two modalities diverge most dramatically. BCG is extraordinarily sensitive to motion artifacts because any body movement generates accelerations far exceeding the cardiac-induced micro-accelerations. Walking produces accelerations of 100-1000 mg, compared to the 1-10 mg cardiac BCG signal, a signal-to-artifact ratio of -40 to -60 dB. This makes BCG essentially unusable during any form of physical activity or even during voluntary movements while seated.
PPG is also susceptible to motion artifacts, as discussed in our motion artifact removal guide, but the motion-to-cardiac signal ratio is typically -10 to -30 dB during moderate activity, and modern multi-axis accelerometer-referenced adaptive filtering can recover usable cardiac signals during walking, running, and many other activities. This is a decisive practical advantage of PPG for wearable continuous monitoring during daily life.
Measurement Capabilities
Heart Rate
Both BCG and PPG provide accurate heart rate measurement under stationary conditions. BCG heart rate can be extracted from inter-beat intervals measured between corresponding fiducial points (typically J-wave peaks) in successive cardiac cycles. PPG heart rate is extracted from systolic peak intervals, as implemented in virtually all wearable devices.
Under stationary conditions, bed-based BCG heart rate can be comparable to wrist-based PPG at rest. However, BCG heart rate measurement is limited to stationary conditions, while PPG provides continuous heart rate during activity.
Heart Rate Variability
Both modalities can provide HRV analysis, but with different characteristics. BCG-based beat-to-beat interval estimation has been compared against ECG in a number of studies; Bruser et al. (2015) review BCG alongside other ambient and unobtrusive cardiorespiratory monitoring modalities (doi:10.1109/RBME.2015.2414661). The temporal precision of BCG fiducial point detection is comparable to PPG, both being inferior to ECG for beat-to-beat timing accuracy.
PPG-derived HRV has been widely compared against ECG and generally agrees well for standard HRV metrics during rest and sleep. The advantage of PPG for HRV analysis is continuous availability during both rest and activity, enabling 24-hour HRV monitoring that is impractical with BCG.
Cardiac Output and Contractility
BCG has a unique advantage in its potential to assess cardiac contractile function. Because the BCG signal amplitude is directly related to the rate of momentum transfer during ventricular ejection, it correlates with stroke volume and cardiac output. Human physiology studies reviewed by Inan et al. (2015) have explored BCG features as non-invasive markers of cardiac function (doi:10.1109/JBHI.2014.2361732).
PPG does not directly measure cardiac output, though PPG waveform features (augmentation index, pulse area, dicrotic notch position) provide indirect information about vascular impedance and arterial compliance that is related to cardiac function. The pulse wave analysis algorithms used in PPG research can estimate derived parameters, but PPG fundamentally measures the peripheral hemodynamic response rather than the central cardiac force generation.
Blood Oxygen Saturation
PPG has a definitive advantage here: SpO2 measurement is inherently optical and is one of PPG's most clinically important applications. By comparing the pulsatile absorption at red (660 nm) and infrared (940 nm) wavelengths, PPG-based pulse oximeters estimate arterial oxygen saturation with accuracy of 2-3% SpO2 in the 70-100% range. BCG has no mechanism for SpO2 measurement.
Blood Pressure
Both modalities contribute to cuffless blood pressure estimation, but through different mechanisms. BCG provides timing information about the cardiac ejection event, which, when combined with a peripheral timing reference (such as PPG), yields pulse transit time. PTT has an inverse relationship with blood pressure through arterial stiffness: higher blood pressure increases arterial wall tension, increasing pulse wave velocity and decreasing PTT.
The BCG-PPG PTT approach has shown promising results. Martin et al. (2016) measured "scale PTT" from BCG on a bathroom weighing scale plus foot PPG during interventions that raised blood pressure. Scale PTT tracked diastolic pressure changes with a correlation of -0.80 and an RMSE of 7.6 mmHg after best-case calibration, outperforming conventional ECG-to-finger-PPG pulse arrival time (-0.60 and 14.6 mmHg) (doi:10.1038/srep39273). PPG-only blood pressure estimation using pulse wave analysis features is also an active area of research, as discussed in our article on cuffless blood pressure monitoring.
Form Factors and Deployment
BCG Form Factors
BCG sensors are most naturally integrated into surfaces that support the body:
Bed sensors: Piezoelectric films, load cells, or accelerometers embedded in or placed under the mattress capture BCG during sleep. This is the most successful commercial BCG deployment, with products like Emfit QS, Beddit (acquired by Apple), and Withings Sleep Mat providing overnight heart rate, respiratory rate, and sleep staging.
Smart scales: Standing BCG captured during weight measurement can extract heart rate and pulse wave velocity. The Withings Body Cardio scale uses standing BCG to estimate aortic pulse wave velocity, which correlates with cardiovascular risk. The measurement requires standing still for 15-30 seconds, limiting it to brief spot checks rather than continuous monitoring.
Smart chairs and car seats: Seated BCG can be captured through force-sensing elements in chair legs or seat cushions. Automotive applications for driver health monitoring are under development, though vibration from the vehicle itself presents significant artifact challenges.
Handheld devices: Smartphone motion sensors can capture BCG-like cardiac motion. Hernandez et al. (2015) extracted heart and breathing rates from smartphone accelerometer data, even with the phone carried in a bag or pocket, reaching a heart rate mean absolute error of 1.16 BPM across still postures in 12 people (doi:10.1109/EMBC.2015.7320048). The approach requires the user to remain still during the measurement.
PPG Form Factors
PPG sensors can be integrated into any device that maintains skin contact with optical access:
Wrist wearables: Smartwatches and fitness bands use reflectance-mode PPG with green LEDs for heart rate and red/infrared LEDs for SpO2. This is the dominant consumer health sensing form factor, with billions of devices deployed.
Finger sensors: Clinical pulse oximeters use transmission-mode PPG for the most accurate SpO2 measurements. Smart rings (Oura) use reflectance-mode PPG from the finger.
Ear-based devices: Earbuds with PPG sensors (PPG from the ear canal or concha) achieve excellent signal quality due to minimal motion artifact and consistent skin contact.
Patches and adhesive sensors: Medical-grade adhesive PPG patches provide continuous monitoring of hospitalized or ambulatory patients.
Cameras: Remote PPG (rPPG) extends PPG to contactless measurement using ambient light and video cameras. Smartphone cameras can also perform contact PPG with the finger-on-lens technique.
Accuracy Comparison Summary
Scroll horizontally if needed
| Parameter | BCG (bed/scale) | PPG (wrist wearable) | PPG (finger clip) |
|---|---|---|---|
| Heart rate (rest) | MAE 0.5-2 BPM | MAE 1-3 BPM | MAE 0.5-1 BPM |
| Heart rate (motion) | Not feasible | MAE 3-8 BPM | MAE 1-3 BPM |
| Respiratory rate | MAE 0.5-1.5 BPM | MAE 1-2 BPM | MAE 1-2 BPM |
| HRV (RMSSD) | r = 0.92-0.97 | r = 0.85-0.95 | r = 0.95-0.99 |
| SpO2 | Not possible | 2-4% (wrist) | 1-2% (finger) |
| Cardiac contractility | Feasible | Not direct | Not direct |
| Continuous monitoring | Sleep only | 24-hour | Spot check |
Complementary Integration
The strongest case for BCG is not as a replacement for PPG but as a complement. BCG excels in exactly the scenarios where wearable PPG is absent: during sleep when many users remove wrist wearables, during weight measurement as a natural health checkpoint, and in ambient monitoring contexts where no wearable is needed.
The temporal relationship between BCG (central cardiac event) and PPG (peripheral pulse arrival) provides pulse transit time, which is valuable for blood pressure estimation. Multi-modal systems that capture both BCG and PPG can extract parameters unavailable from either modality alone, including pre-ejection period, left ventricular ejection time, and pulse wave velocity.
For comprehensive cardiac monitoring, the ideal system might combine wrist-based PPG for continuous daytime monitoring with bed-based BCG for overnight monitoring and smart scale BCG for periodic cardiovascular health assessment, all feeding into a unified digital biomarker platform that tracks longitudinal trends.
Future Directions
Advances in MEMS accelerometer sensitivity and AI-based signal processing are expanding BCG capabilities. Machine learning models trained on large BCG datasets can extract heart rate during mild motion and detect cardiac arrhythmias from BCG morphology. Integration of BCG sensing into everyday surfaces (toilets, desks, vehicle seats) could enable truly ambient health monitoring that requires no user awareness or interaction.
PPG continues to advance through multi-wavelength sensing, improved motion artifact removal, and expanding clinical validation for parameters like cuffless blood pressure and atrial fibrillation detection. The technology maturity and commercial ecosystem of PPG are substantially ahead of BCG.
The convergence of BCG, PPG, and radar-based vital signs approaches into multi-modal health monitoring platforms represents the most promising direction for comprehensive, non-invasive cardiac assessment. Each modality contributes unique information, and their combination provides redundancy and complementary coverage across different activity states and environments.
References
- Starr, I., Rawson, A. J., Schroeder, H. A., & Joseph, N. R. (1939). Studies on the estimation of cardiac output in man, and of abnormalities in cardiac function, from the heart's recoil and the blood's impacts; the ballistocardiogram. American Journal of Physiology, 127(1), 1-28. https://doi.org/10.1152/ajplegacy.1939.127.1.1
- Inan, O. T., et al. (2015). Ballistocardiography and seismocardiography: a review of recent advances. IEEE Journal of Biomedical and Health Informatics, 19(4), 1414-1427. https://doi.org/10.1109/JBHI.2014.2361732
- Bruser, C., Antink, C. H., Wartzek, T., Walter, M., & Leonhardt, S. (2015). Ambient and unobtrusive cardiorespiratory monitoring techniques. IEEE Reviews in Biomedical Engineering, 8, 30-43. https://doi.org/10.1109/RBME.2015.2414661
- Martin, S. L.-O., et al. (2016). Weighing scale-based pulse transit time is a superior marker of blood pressure than conventional pulse arrival time. Scientific Reports, 6, 39273. https://doi.org/10.1038/srep39273
- Hernandez, J., McDuff, D. J., & Picard, R. W. (2015). BioPhone: Physiology monitoring from peripheral smartphone motions. 2015 37th Annual International Conference of the IEEE EMBC, 7180-7183. https://doi.org/10.1109/EMBC.2015.7320048
Related articles
PPG Ring vs Wrist Sensor Comparison
Ring-based PPG sensors and wrist smartwatches both measure heart rate, SpO2, and HRV using photoplethysmography. But they access fundamentally differe...
PPG vs Abp Comparison
The photoplethysmographic (PPG) waveform and the arterial blood pressure (ABP) waveform are intimately related but fundamentally different measurement...
PPG vs ECG Accuracy Comparison: Heart Rate, HRV, and Arrhythmia Detection Data
PPG vs ECG accuracy compared for heart rate, HRV metrics, arrhythmia detection, and respiratory rate with published validation data and comparison tables.
Which Wearable Has the Most Accurate Heart Rate Monitor in 2026?
Comparing heart rate accuracy across Apple Watch, Garmin, Fitbit, Samsung, Polar, and Oura Ring. Based on independent clinical validation studies.