PPG Sampling Rate: How Many Hz Do You Need?
How PPG sampling rate limits heart rate, HRV, SpO2 and waveform analysis. A pilot downsampling study found pulse rate variability held up at 25 Hz and up.
- SpO2 & Oximetry
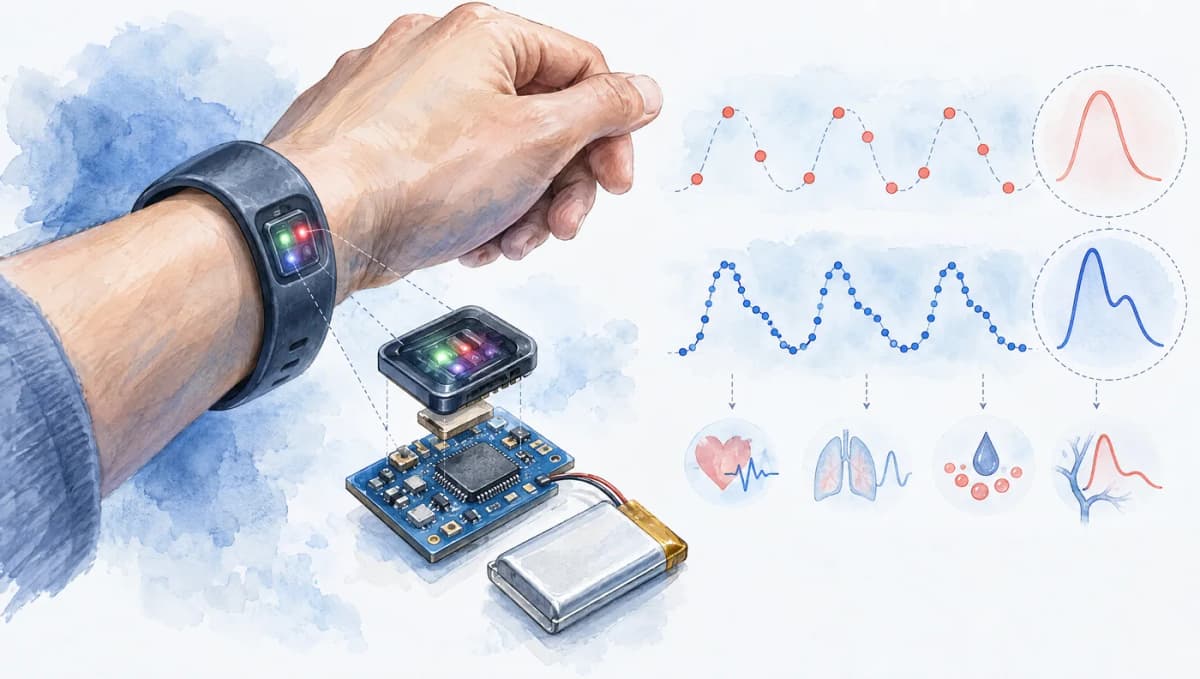
The sampling rate of a PPG sensor determines the upper bound on timing precision, frequency resolution, and waveform fidelity for every downstream analysis, yet selecting the optimal rate requires balancing accuracy requirements against power consumption constraints that are often orders of magnitude apart. A clinical pulse oximeter sampling at 500 Hz captures the full morphological detail of every pulse waveform but consumes milliwatts of continuous power. A wearable fitness tracker sampling at 25 Hz captures enough information for basic heart rate but loses the fine waveform features needed for advanced hemodynamic analysis.
This guide systematically examines how PPG sampling rate affects the accuracy of heart rate estimation, heart rate variability analysis, blood oxygen saturation measurement, pulse wave analysis, and respiratory rate extraction. It provides specific numerical benchmarks to help engineers and researchers select the right sampling rate for their application. For the fundamentals of PPG signal acquisition, see our guide to PPG technology.
Sampling Theory Fundamentals for PPG
Nyquist Criterion
The Nyquist-Shannon sampling theorem states that a bandlimited signal must be sampled at a rate at least twice the highest frequency component to enable perfect reconstruction. For PPG, the relevant frequency content depends on the analysis objective:
- Heart rate fundamental frequency: 0.5-3.5 Hz (30-210 BPM), requiring a minimum of 7 Hz sampling
- Heart rate with harmonics: Up to 10-15 Hz for the first 3-4 harmonics of the cardiac waveform
- Pulse wave morphological features: The dicrotic notch and systolic peak contain frequency content up to 15-25 Hz
- High-frequency noise and artifact: Can extend to 50-100 Hz or higher
The theoretical Nyquist minimum for PPG cardiac content is approximately 7-10 Hz, but practical considerations push the required sampling rate significantly higher.
Beyond Nyquist: Practical Considerations
The Nyquist theorem assumes ideal bandlimited signals and perfect reconstruction filters, neither of which exists in practice. Real PPG signals contain frequency content above any chosen anti-aliasing filter cutoff, real anti-aliasing filters have finite rolloff slopes, and quantization noise from the ADC adds a noise floor that interacts with sampling rate.
The practical rule of thumb for PPG is to sample at 5-10 times the highest frequency of interest to provide adequate margin for anti-aliasing filter rolloff, timing interpolation accuracy, and robust peak detection. This translates to 25-100 Hz for heart rate applications and 100-500 Hz for waveform morphology applications.
Anti-Aliasing Filter Requirements
Before analog-to-digital conversion, an anti-aliasing low-pass filter must attenuate frequency content above half the sampling rate to prevent aliasing. For a 25 Hz PPG sampling rate, the anti-aliasing filter must suppress content above 12.5 Hz. A typical second-order analog filter provides -12 dB/octave rolloff, meaning that at twice the cutoff frequency (25 Hz), attenuation is only -12 dB, potentially allowing aliased noise into the signal.
Higher-order analog filters (fourth-order Butterworth provides -24 dB/octave) or oversampling with digital decimation filtering can address this. Oversampling at 4-16 times the target rate followed by digital low-pass filtering and decimation is common in modern PPG AFEs (analog front-ends), providing effective anti-aliasing with a simple first-order analog pre-filter.
Impact on Heart Rate Estimation
Peak Detection Timing Resolution
The most direct effect of sampling rate on heart rate accuracy is through peak detection timing resolution. At sampling rate Fs, the temporal resolution of any detected peak is 1/Fs seconds. This timing uncertainty propagates directly into heart rate estimation error.
For a heart rate of 60 BPM (1000 ms inter-beat interval), a timing uncertainty of +/-1 sample at 25 Hz (+/-40 ms) produces a heart rate uncertainty of +/-2.4 BPM. At 100 Hz (+/-10 ms), the uncertainty drops to +/-0.6 BPM. At 256 Hz (+/-3.9 ms), it drops further to +/-0.23 BPM.
Interpolation techniques can improve timing precision beyond the native sampling resolution. Parabolic interpolation around the peak sample estimates the true peak location to sub-sample accuracy. Béres and Hejjel (2021) found that cubic spline or parabolic interpolation can improve HRV accuracy from lower-resolution PPG (doi:10.1016/j.bspc.2021.102589).
Empirical Accuracy vs. Sampling Rate
Béres and Hejjel (2021) decimated 57 high-quality 5-minute PPG recordings from healthy volunteers, originally sampled at 1 kHz, and measured the resulting error in pulse rate and HRV parameters (doi:10.1016/j.bspc.2021.102589). They concluded that for monitoring average heart rate, a sampling frequency as low as 5 Hz can be sufficient without interpolation in healthy subjects, while correct HRV analysis requires higher sampling rates depending on the parameter.
In practice, 25-50 Hz is a common choice for heart rate estimation in wearables, with higher rates used when beat timing or waveform detail matters.
Spectral Heart Rate Estimation
FFT-based heart rate estimation determines heart rate from the dominant spectral peak in the cardiac frequency band. The frequency resolution of the FFT is Fs/N, where N is the window length in samples. For a 25 Hz sampling rate with an 8-second window (200 samples), frequency resolution is 0.125 Hz, corresponding to 7.5 BPM resolution. For a 100 Hz rate with the same 8-second window (800 samples), resolution improves to 0.125 Hz (identical, since resolution depends on window duration, not sampling rate).
This highlights an important distinction: spectral frequency resolution depends on the window duration in seconds, not the sampling rate. Higher sampling rates do not improve spectral resolution for a fixed window duration. They do improve spectral SNR (through increased frequency bins for noise averaging) and reduce spectral leakage from aliased high-frequency content.
Zero-padding the FFT provides interpolated frequency resolution but does not add true spectral information. For improved spectral heart rate estimates at low sampling rates, longer analysis windows (10-15 seconds) are more effective than higher sampling rates. More on spectral methods for PPG is available in our power spectral analysis guide.
Impact on Heart Rate Variability
Time-Domain HRV Metrics
HRV analysis requires precise timing of inter-beat intervals, making it the most sampling-rate-sensitive PPG application. The key time-domain metrics and their sampling rate dependencies are:
SDNN (standard deviation of NN intervals): Relatively robust to sampling rate because it averages timing errors over many intervals.
RMSSD (root mean square of successive differences): Highly sensitive to timing precision because it amplifies interval-to-interval variations. Timing quantization at low sampling rates adds noise to each interval, and that noise is amplified in successive differences, so RMSSD is inflated more than SDNN.
pNN50 (percentage of successive intervals differing by >50 ms): At low sampling rates, quantization can push intervals across the 50 ms threshold, inflating pNN50. This effect is most pronounced at 25 Hz where the quantization step (40 ms) is close to the 50 ms threshold.
Choi and Shin (2017) down-sampled 10 kHz PPG recordings to rates from 5000 Hz down to 5 Hz and compared the derived PRV variables with HRV from 10 kHz ECG. pNN50 and NN50 differed significantly at 20 Hz or below, RMSSD and SDSD at 15 Hz or below, and no variable differed significantly above 25 Hz in this pilot study (doi:10.1088/1361-6579/aa5efa).
Frequency-Domain HRV
Frequency-domain HRV analysis (LF power at 0.04-0.15 Hz, HF power at 0.15-0.4 Hz) is computed from the inter-beat interval time series, not directly from the PPG waveform. The effective sampling rate for this spectral analysis is the mean heart rate (typically 1-1.5 Hz), regardless of the PPG sampling rate.
Higher PPG sampling rates improve frequency-domain HRV primarily through better inter-beat interval timing precision, which reduces the noise floor of the interval spectrum. At 25 Hz, the quantization noise floor can obscure low-amplitude HRV spectral components. At 100 Hz, the noise floor drops by approximately 12 dB (fourfold reduction in timing noise power).
For standard LF/HF ratio analysis used in autonomic function assessment, 50 Hz PPG sampling is generally adequate. For research applications requiring precise VLF analysis or assessment of specific spectral peaks, 200 Hz or higher is recommended. See our HRV analysis algorithms guide for more on frequency-domain techniques.
Impact on SpO2 Accuracy
Ratio-of-Ratios Precision
SpO2 estimation from PPG uses the ratio of pulsatile-to-baseline signal amplitude at red and infrared wavelengths:
Accurate R calculation requires precise measurement of the AC amplitude at each wavelength. Low sampling rates reduce the probability of capturing the exact peak and trough of each pulse, introducing amplitude estimation error that propagates into SpO2 error.
The systolic upstroke of a finger PPG is relatively fast, so coarse sampling can miss the true peak and trough and bias the AC amplitude estimate. Any such amplitude error propagates into SpO2 through the R-ratio calibration curve, which is one reason clinical devices use higher sampling rates than many wearables.
Clinical Pulse Oximeter Standards
ISO 80601-2-61 specifies accuracy requirements for clinical pulse oximeters (expressed as Arms over the 70-100% SpO2 range) but does not mandate a specific sampling rate. In practice, clinical pulse oximeters typically sample at higher rates than consumer wearables to ensure adequate amplitude resolution and to support the multi-wavelength time-division multiplexing needed for ambient light rejection.
Consumer wearable SpO2 sensors typically sample at 25-50 Hz for the red and infrared channels, which contributes to their generally lower accuracy compared to clinical devices. However, sampling rate is only one factor among many (sensor placement, contact pressure, skin pigmentation, motion) that affect wearable SpO2 accuracy. For SpO2 reference values and clinical interpretation, see our blood oxygen level chart.
Impact on Pulse Wave Analysis
Morphological Feature Resolution
Pulse wave analysis extracts features from the shape of individual PPG pulses, including the systolic peak time, dicrotic notch position, pulse area, and various derivative-based indices. These features contain frequency content up to 15-25 Hz, requiring sampling rates of 50-100 Hz minimum.
The dicrotic notch is the most sampling-rate-sensitive morphological feature. It manifests as a brief indentation (typically 20-60 ms duration) in the diastolic downslope. At 25 Hz, the notch occupies only 1-2 samples and may be undetectable or severely distorted. At 100 Hz, 2-6 samples capture the notch shape. At 250 Hz, 5-15 samples provide clear morphological definition.
Morphology-based indices depend on resolving these features. For example, the stiffness index of Millasseau et al. (2002) is derived from the time delay between the direct and reflected waves of the digital volume pulse; it correlated with carotid-femoral pulse wave velocity (r = 0.65) in 87 subjects, and its accuracy depends on locating both waves precisely (doi:10.1042/cs1030371).
Second Derivative Analysis (SDPPG)
The second derivative of the PPG waveform (acceleration plethysmogram, APG) decomposes each pulse into characteristic waves (a, b, c, d, e waves) that correlate with vascular aging and arterial stiffness. Computing the second derivative amplifies high-frequency content and noise, making it extremely sensitive to sampling rate.
At 50 Hz, second derivative computation from PPG is dominated by quantization noise, rendering SDPPG wave identification unreliable. At 100 Hz, the a and b waves are typically identifiable, but the smaller c, d, and e waves are marginal. At 250 Hz and above, all five waves are consistently resolvable in clean signals.
For SDPPG-based vascular assessment, a minimum sampling rate of 200 Hz is recommended, with 500 Hz preferred for research applications requiring precise wave amplitude ratios. This is one application where sampling rate has a dramatic impact on feasibility.
Pulse Transit Time and Blood Pressure
Cuffless blood pressure estimation using pulse transit time (PTT) or pulse arrival time (PAT) requires high timing precision. PTT values are typically 100-300 ms, and a 10 mmHg blood pressure change corresponds to a PTT change of approximately 5-15 ms. To detect such changes reliably, timing resolution of 1-2 ms is needed, implying sampling rates of 500-1000 Hz.
At lower sampling rates, interpolation can partially compensate. Parabolic interpolation at 100 Hz achieves effective timing resolution of approximately 2-3 ms, marginally adequate for blood pressure trending. At 25 Hz, even with interpolation, PTT-based blood pressure estimation is unreliable due to insufficient timing precision.
Impact on Respiratory Rate Extraction
Respiratory rate extraction from PPG uses three modulation types: amplitude modulation (AM), baseline modulation (BM), and frequency modulation (FM, respiratory sinus arrhythmia). The respiratory frequency band is 0.15-0.5 Hz (9-30 breaths per minute).
Since respiratory information is encoded as modulation of the cardiac signal rather than as direct frequency content, the critical sampling rate requirement is determined by the cardiac signal, not the respiratory signal itself. A sampling rate adequate for reliable peak detection (25-50 Hz) is sufficient for respiratory rate extraction from PPG.
Karlen et al. (2013) estimated respiratory rate from the frequency, intensity, and amplitude variations of the PPG in 29 children and 13 adults, and found that fusing the three variations (RMS error 3.0 breaths/min) outperformed the individual methods (doi:10.1109/TBME.2013.2246160). Because these modulations are slow, respiratory rate extraction depends mainly on reliable beat detection rather than on high sampling rates.
Power Consumption and Battery Life
Sampling rate has a nearly linear relationship with PPG sensor power consumption because each sample requires the LED to be illuminated and the photodetector and ADC to be active. For a typical wrist PPG sensor:
- At 25 Hz: LED duty cycle approximately 0.5%, average current 0.3-0.8 mA
- At 50 Hz: LED duty cycle approximately 1%, average current 0.5-1.5 mA
- At 100 Hz: LED duty cycle approximately 2%, average current 1-3 mA
- At 250 Hz: LED duty cycle approximately 5%, average current 2.5-7 mA
For a wearable with a 300 mAh battery, doubling the sampling rate from 25 Hz to 50 Hz reduces continuous PPG monitoring battery life by approximately 10-20%. Going from 25 Hz to 250 Hz can reduce battery life by 50% or more, depending on other system power consumers.
This power-accuracy tradeoff is the primary engineering driver behind the 25-50 Hz sampling rates used in consumer wearables. The marginal accuracy improvement from higher rates rarely justifies the battery life penalty for basic heart rate monitoring. However, for clinical devices with rechargeable batteries and continuous power availability, higher sampling rates are practical and preferred.
ADC Resolution Considerations
While not directly related to sampling rate, ADC resolution (bit depth) interacts with sampling rate to determine overall signal quality. Common PPG ADC resolutions are:
- 16-bit: Dynamic range of 96 dB, adequate for most applications
- 20-bit: Dynamic range of 120 dB, enables simultaneous capture of large DC and small AC components without gain switching
- 24-bit: Dynamic range of 144 dB, used in high-end research systems
Modern PPG AFEs (such as the TI AFE4404, Maxim MAX86150, and Analog Devices ADPD4101) provide 20-24 bit resolution with integrated ambient light rejection, LED current control, and configurable sampling rates from 10 Hz to 1600 Hz. For an overview of how these components integrate into wearable systems, see our wearable sensor technology guide.
Practical Sampling Rate Recommendations
Based on the evidence reviewed above, the following sampling rates are recommended for specific PPG applications:
Scroll horizontally if needed
| Application | Minimum Rate | Recommended Rate | Notes |
|---|---|---|---|
| Heart rate (resting) | 25 Hz | 25-50 Hz | With interpolation |
| Heart rate (exercise) | 50 Hz | 50-100 Hz | Higher for motion artifact processing |
| HRV (time-domain) | 50 Hz | 100-256 Hz | RMSSD sensitive to timing |
| HRV (frequency-domain) | 25 Hz | 50-100 Hz | Less timing-sensitive |
| SpO2 | 50 Hz | 100 Hz | Amplitude accuracy critical |
| Pulse wave analysis | 100 Hz | 200-500 Hz | Dicrotic notch resolution |
| Blood pressure (PTT) | 250 Hz | 500-1000 Hz | Sub-ms timing needed |
| Respiratory rate | 25 Hz | 25-50 Hz | Low frequency content |
| Research (general) | 100 Hz | 250-500 Hz | Flexibility for multiple analyses |
For a comprehensive understanding of how sampling rate choices interact with other signal processing decisions in the PPG pipeline, see our PPG signal processing algorithms guide.
Frequently Asked Questions
What sampling rate do I need for PPG heart rate measurement?
For basic heart rate measurement, 25 Hz is the practical minimum sampling rate, and most consumer wearables sample at 25-50 Hz. At 25 Hz, peak detection timing resolution is 40 ms, which translates to approximately 1-3 BPM uncertainty at typical heart rates. In healthy subjects at rest, even much lower rates can be sufficient for average heart rate (Béres and Hejjel, 2021). For exercise heart rate where motion artifact algorithms need spectral resolution, 50-100 Hz is recommended.
What sampling rate is required for accurate HRV from PPG?
For time-domain HRV metrics (SDNN, RMSSD), a minimum sampling rate of 50 Hz is recommended, with 100-256 Hz preferred. Lower rates add quantization error to inter-beat intervals, which inflates RMSSD; in one pilot study, no PRV variable differed significantly from ECG-derived HRV above 25 Hz (Choi and Shin, 2017). For frequency-domain HRV (LF, HF power), 50 Hz is generally adequate since spectral methods are less sensitive to individual interval timing precision.
Why do clinical pulse oximeters sample faster than smartwatches?
Clinical pulse oximeters typically sample at 100-500 Hz, while consumer smartwatches sample at 25-50 Hz. The higher clinical sampling rate serves several purposes: it provides better temporal resolution for detecting the precise timing of the pulsatile waveform needed for accurate SpO2 ratio-of-ratios calculation, enables better motion artifact detection and removal, supports pulse waveform analysis for hemodynamic monitoring, and meets regulatory requirements for clinical accuracy. Consumer wearables use lower rates primarily to reduce power consumption and extend battery life.
Does higher PPG sampling rate always mean better accuracy?
No, beyond a certain point, increasing sampling rate provides diminishing returns while increasing power consumption, data storage, and computational requirements. For heart rate, accuracy improvement plateaus above approximately 50 Hz. For HRV, improvement plateaus above 200-256 Hz. For SpO2, 100 Hz is generally sufficient. For pulse wave analysis and blood pressure estimation, 200-500 Hz may be beneficial. The optimal rate depends entirely on the target application and the specific parameters being extracted. Oversampling does help with noise reduction through averaging, but this can also be achieved with lower sample rates and analog filtering.
References
- Béres, S., & Hejjel, L. (2021). The minimal sampling frequency of the photoplethysmogram for accurate pulse rate variability parameters in healthy volunteers. Biomedical Signal Processing and Control, 68, 102589. https://doi.org/10.1016/j.bspc.2021.102589
- Choi, A., & Shin, H. (2017). Photoplethysmography sampling frequency: pilot assessment of how low can we go to analyze pulse rate variability with reliability? Physiological Measurement, 38(3), 586-600. https://doi.org/10.1088/1361-6579/aa5efa
- Millasseau, S. C., Kelly, R. P., Ritter, J. M., & Chowienczyk, P. J. (2002). Determination of age-related increases in large artery stiffness by digital pulse contour analysis. Clinical Science, 103(4), 371-377. https://doi.org/10.1042/cs1030371
- Karlen, W., Raman, S., Ansermino, J. M., & Dumont, G. A. (2013). Multiparameter respiratory rate estimation from the photoplethysmogram. IEEE Transactions on Biomedical Engineering, 60(7), 1946-1953. https://doi.org/10.1109/TBME.2013.2246160
Related articles
PPG vs ECG Accuracy Comparison: Heart Rate, HRV, and Arrhythmia Detection Data
PPG vs ECG accuracy compared for heart rate, HRV metrics, arrhythmia detection, and respiratory rate with published validation data and comparison tables.
PPG Heart Rate Sensor Explained: Optical Modules, Multi-LED Design, and Motion Compensation
How PPG heart rate sensors work inside wearables. Learn about multi-LED arrays, ambient light rejection, accelerometer fusion, and sensor module design.
PPG Heart Rate Measurement: Algorithms, Accuracy, and Practical Implementation
How PPG measures heart rate step by step. Learn peak detection algorithms, beat-to-beat vs averaged HR, and accuracy benchmarks for rest, exercise, and sleep.
ECG vs Heart Rate Monitor: Electrical vs Optical
ECG vs heart rate monitoring explained. Understand when ECG electrical signals or PPG optical pulse detection is the right tool for cardiac measurement.
Devices in this article
Research records with the datasets, papers and published validation results for each device.