PAD Detection with PPG: Ankle-Brachial Index, Pulse Wave Analysis & Screening
**Peripheral artery disease affects over 230 million people worldwide, yet up to 50% of cases remain undiagnosed because standard screening requires s...
- PPG & Signal Processing
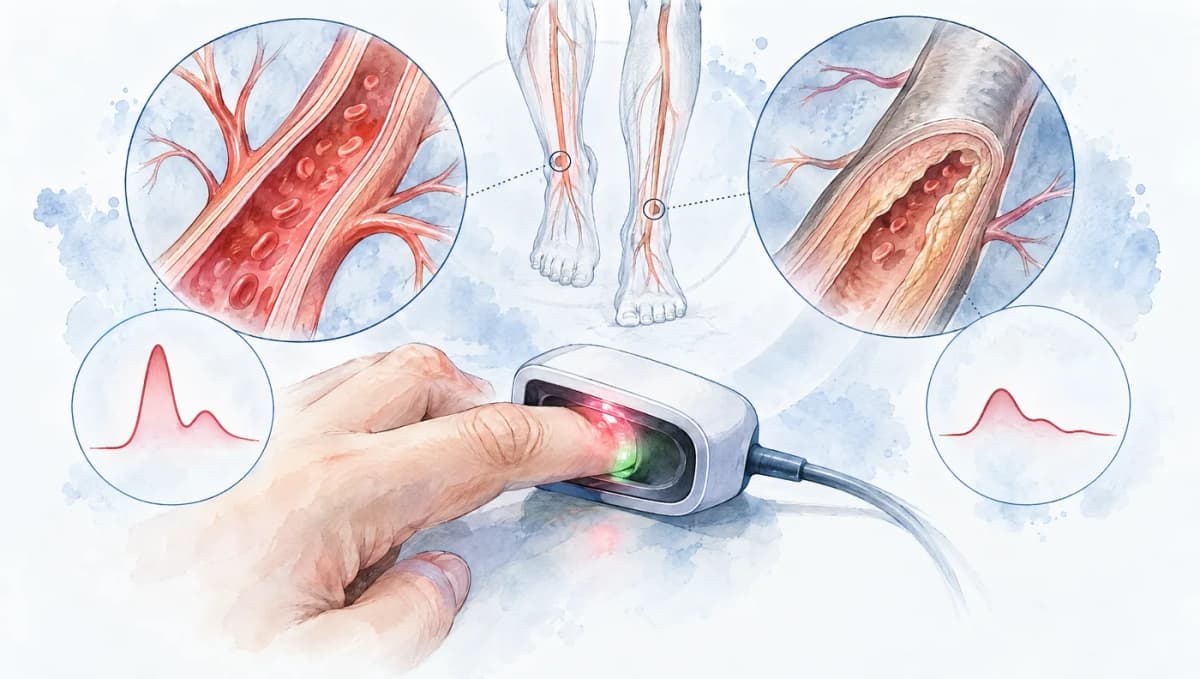
Peripheral artery disease affects over 230 million people worldwide, yet up to 50% of cases remain undiagnosed because standard screening requires specialized Doppler equipment and trained operators. Photoplethysmography offers a simpler, cheaper, and more accessible approach to PAD screening that could dramatically expand detection in primary care, community health settings, and even home environments. PPG-based approaches include simplified ankle-brachial index (ABI) measurement, pulse wave morphology analysis, and multi-feature machine learning classification, all leveraging the fundamental sensitivity of PPG to arterial blood flow and peripheral perfusion.
This article reviews the clinical significance of PAD, the physiological basis for PPG-based detection, the evidence from validation studies, and the practical considerations for implementation. For foundational context on how PPG sensors measure arterial blood flow, see our introduction to PPG technology.
Clinical Significance of PAD and the Screening Gap
Peripheral artery disease is characterized by atherosclerotic narrowing or occlusion of arteries supplying the limbs, predominantly the lower extremities. PAD is a marker of systemic atherosclerosis, and patients with PAD are at increased risk of myocardial infarction and stroke. Globally, an estimated 202 million people were living with PAD in 2010, 69.7% of them in low- and middle-income countries (Fowkes et al., 2013, The Lancet; doi:10.1016/S0140-6736(13)61249-0).
The clinical presentation ranges from asymptomatic disease (the majority of cases) through intermittent claudication (leg pain with walking) to critical limb ischemia (rest pain, tissue loss, gangrene). Early detection enables guideline-recommended risk reduction with statin therapy, antiplatelet agents, and structured exercise programs (Gerhard-Herman et al., 2017, AHA/ACC Guidelines; doi:10.1161/CIR.0000000000000471).
The Standard ABI Measurement
The ankle-brachial index is the ratio of systolic blood pressure measured at the ankle to that measured in the arm. An ABI of 0.90 or below is the standard diagnostic threshold for PAD, and values of 1.00 to 1.40 are considered normal (Aboyans et al., 2012, AHA scientific statement in Circulation; doi:10.1161/CIR.0b013e318276fbcb). Values above 1.4 suggest medial arterial calcification (common in diabetes and chronic kidney disease), which can mask underlying PAD.
Standard ABI measurement uses a Doppler ultrasound probe and a blood pressure cuff to measure systolic pressure in the dorsalis pedis and posterior tibial arteries at the ankle and the brachial artery in the arm. This procedure requires trained personnel, takes 15-20 minutes, and is rarely performed outside vascular specialty clinics despite guideline recommendations for screening in at-risk populations (adults over 65, smokers, diabetics).
PPG-Based ABI Measurement
PPG can replace the Doppler probe in ABI measurement by using PPG sensors at the toe and finger to detect the arrival of the arterial pulse during cuff deflation, analogous to oscillometric blood pressure measurement.
Methodology
The PPG-ABI technique places a PPG sensor (typically a transmission-mode clip sensor) on the great toe and another on the index finger. Standard blood pressure cuffs are inflated above systolic pressure at both the ankle and the arm, then slowly deflated. The systolic pressure at each site is determined as the cuff pressure at which the PPG pulsatile signal reappears during deflation. The ratio of ankle to arm systolic pressure yields the PPG-based ABI.
Validation Evidence
Published validation of automated, non-Doppler ABI methods is a reminder that automation alone does not guarantee accuracy. Kornø et al. (2009) compared an automated oscillometric ankle-pressure device (not PPG) with hand-held Doppler in 61 vascular patients (122 legs). For ABI ≤0.9 it had 71% sensitivity and 92% specificity, and ankle pressures were systematically overestimated in patients with reduced pressures, so some PAD patients were falsely classified as normal (doi:10.1016/j.ejvs.2009.07.004). Cuff-based PPG-ABI devices need similar head-to-head validation against Doppler in the populations where they will be used.
Advantages Over Doppler ABI
PPG-based ABI measurement offers several practical advantages for screening:
- Reduced operator dependence: Doppler ABI requires the operator to identify arterial signals and position the probe correctly, which is error-prone in patients with weak pulses. PPG measurement is largely automated once sensors are placed.
- Shorter examination time: Automated measurement can shorten examinations compared with manual Doppler.
- Lower equipment cost: PPG sensors cost a fraction of Doppler probes, making widespread deployment feasible in primary care.
- Compatibility with automated systems: PPG-based measurement lends itself to fully automated devices requiring minimal operator interaction.
Limitations
PPG-ABI shares some limitations with Doppler-ABI. In patients with medial arterial calcification (diabetes, CKD), both methods may fail to compress the ankle arteries sufficiently, yielding falsely elevated ABI values. PPG-ABI measurement still requires blood pressure cuffs and a controlled measurement protocol, limiting applicability for casual screening. Peripheral vasoconstriction from cold exposure or anxiety can reduce PPG signal amplitude and introduce measurement error.
Pulse Wave Morphology Analysis
Beyond ABI measurement, the shape of the PPG waveform itself contains diagnostic information about upstream arterial stenosis. This approach requires only a single PPG sensor and no blood pressure cuffs, offering potential for simplified screening.
Waveform Changes in PAD
Arterial stenosis produces characteristic changes in the distal PPG waveform through several mechanisms:
Pulse dampening: A hemodynamically significant stenosis (>50% diameter reduction) attenuates the amplitude and slows the rise time of the arterial pressure pulse transmitted to distal vessels. This manifests as reduced PPG amplitude and a slower, more rounded systolic upstroke. Allen (2007) documented that the time from pulse onset to systolic peak increases from approximately 120-150 ms in healthy limbs to 180-250 ms in limbs with significant PAD (doi:10.1088/0967-3334/28/3/R01).
Loss of dicrotic notch: The dicrotic notch in the PPG waveform is generated by aortic valve closure and reflected pressure waves from peripheral vascular branch points. Stenotic segments absorb and scatter these reflected waves, eliminating the dicrotic notch. Loss of the notch is therefore much more common in limbs with significant PAD than in healthy limbs.
Altered wave contour: The ratio of systolic area to diastolic area under the PPG curve changes with PAD. The crest time (time from onset to peak), expressed as a fraction of pulse duration, increases in PAD-affected limbs.
Multi-Site Waveform Comparison
Comparing PPG waveforms acquired simultaneously from multiple body sites provides powerful diagnostic information. The asymmetry between left and right limbs, or between upper and lower extremities, reveals lateralized or level-specific vascular disease.
Allen et al. (2008) prospectively compared bilateral great-toe PPG with the ankle-brachial pressure index in 111 subjects (48 with significant PAD, 63 healthy). Pulse wave analysis extracted timing, amplitude, and shape features and their right-to-left differences. Pulse shape falling outside the normal range detected significant disease (ABPI <0.9) with 91% accuracy, 93% sensitivity, and 89% specificity, and right-to-left toe transit-time differences reached 86% accuracy (doi:10.1016/j.jvs.2007.11.057).
The pulse volume recording (PVR), a standardized clinical application of limb-level plethysmography, uses cuff-based volume displacement measurement at multiple lower extremity levels (thigh, calf, ankle, metatarsal). While PVR traditionally uses air plethysmography rather than optical PPG, the same multi-level approach applied with PPG sensors yields comparable waveform morphology information with simpler equipment.
Quantitative Waveform Features
Researchers have extracted numerous quantitative features from the PPG waveform for PAD classification:
- Crest time ratio: Systolic rise time / pulse duration. Increases in PAD.
- Pulse area ratio: Systolic area / total pulse area. Increases in PAD.
- Reflection index: Dicrotic notch amplitude / systolic peak amplitude. Decreases in PAD.
- Large artery stiffness index (SI): Subject height / time between systolic and diastolic peaks. Decreases in PAD due to delayed or absent reflected wave.
- Slope ratio: Systolic upstroke slope / diastolic downstroke slope. Moves toward a more symmetric waveform in PAD than in normal limbs.
Machine Learning Classification
Multi-feature machine learning models combine waveform features, demographic data, and risk factors to achieve robust PAD classification.
Traditional Machine Learning
Feature-based classifiers built on the timing, amplitude, and shape features above are a natural extension of the bilateral normative-range approach of Allen et al. (2008). Published validations remain small and mostly single-center.
Deep Learning Approaches
Allen et al. (2021) converted toe PPG signals from 214 participants (31.3% of legs with PAD by ABPI) into spectrogram images and fine-tuned a pretrained AlexNet convolutional neural network. With 5-fold cross-validation, overall test sensitivity was 86.6%, specificity 90.2%, and accuracy 88.9% (kappa 0.76). Sensitivity was 83.0% for mild-moderate disease and 100% for major disease (doi:10.1088/1361-6579/abf9f3). The approach requires minimal pre-processing, but it was a proof-of-concept study built on previously collected data.
Screening Applications and Implementation
Primary Care Screening
The simplicity of PPG-based PAD screening makes it attractive for primary care settings. A screening protocol could involve bilateral toe PPG recording during a routine office visit, with automated waveform analysis providing immediate risk assessment. Positive screens would be referred for confirmatory Doppler ABI and vascular evaluation.
The target screening population includes adults over 65, smokers, diabetics, and those with known cardiovascular disease, as recommended by ACC/AHA guidelines. PAD prevalence rises steeply with age (Fowkes et al., 2013), which raises the pre-test probability in these groups.
Home-Based Screening
Smartphone-based PPG using the phone camera as a transmission-mode PPG sensor on the fingertip has been validated for heart rate and SpO2 measurement. Extending this approach to toe PPG for PAD screening is technically feasible. While home-based screening requires further validation, it could enable mass screening of at-risk populations.
Integration with Cardiovascular Risk Assessment
PPG-based PAD detection provides information beyond PAD itself. The arterial stiffness and vascular function metrics derived from PPG pulse wave analysis are independent predictors of cardiovascular events. Combining PPG-derived vascular health markers with traditional risk factors could improve cardiovascular risk stratification. For more on how PPG algorithms extract vascular health metrics, see our algorithms guide.
Limitations and Future Directions
Calcified Vessels
Medial arterial calcification in diabetic and elderly patients remains a challenge for both Doppler and PPG-based ABI measurement. Alternative approaches such as toe-brachial index (TBI) using PPG may be more reliable in these patients because digital arteries are less prone to calcification. Toe pressures below 30 mmHg (or TBI below 0.7) indicate PAD even when ankle pressures are falsely elevated.
Standardization
No consensus exists on PPG sensor placement, signal processing parameters, or waveform feature definitions for PAD assessment. Variability in sensor type (transmission vs. reflectance), wavelength (green vs. infrared), and sampling rate (30-1000 Hz) across studies makes comparison difficult. Standardization efforts are needed before PPG-based PAD screening can be incorporated into clinical guidelines.
Exercise PPG
Post-exercise PPG assessment could improve sensitivity for detecting mild PAD that is hemodynamically insignificant at rest. Walking exercise provokes symptoms and hemodynamic changes in affected limbs that amplify PPG waveform differences. This approach mirrors the clinical use of post-exercise ABI but could be implemented with a simplified walking protocol and wearable PPG sensors.
Conclusion
PPG-based PAD detection is one of the more mature applications of PPG beyond heart rate and SpO2 measurement, supported by decades of research and consistent validation data. Bilateral toe pulse wave analysis has shown 93% sensitivity and 89% specificity against ABPI (Allen et al., 2008) without requiring blood pressure cuffs, and a deep-learning classifier reached 86.6% sensitivity and 90.2% specificity in a proof-of-concept study (Allen et al., 2021). The primary barrier to clinical adoption is the lack of standardized protocols and prospective validation in large, diverse screening populations. Given the enormous undiagnosed burden of PAD and the simplicity of PPG measurement, this represents a high-impact opportunity for improving cardiovascular screening.
For related content on cardiovascular conditions detectable through PPG analysis and the signal processing methods underlying these approaches, see our dedicated guides.
References
- Fowkes, F. G. R., Rudan, D., Rudan, I., Aboyans, V., Denenberg, J. O., McDermott, M. M., Norman, P. E., Sampson, U. K. A., Williams, L. J., Mensah, G. A., & Criqui, M. H. (2013). Comparison of global estimates of prevalence and risk factors for peripheral artery disease in 2000 and 2010: a systematic review and analysis. The Lancet, 382(9901), 1329-1340. https://doi.org/10.1016/S0140-6736(13)61249-0
- Gerhard-Herman, M. D., Gornik, H. L., Barrett, C., et al. (2017). 2016 AHA/ACC guideline on the management of patients with lower extremity peripheral artery disease. Circulation, 135(12), e726-e779. https://doi.org/10.1161/CIR.0000000000000471
- Aboyans, V., Criqui, M. H., Abraham, P., et al. (2012). Measurement and interpretation of the ankle-brachial index: a scientific statement from the American Heart Association. Circulation, 126(24), 2890-2909. https://doi.org/10.1161/CIR.0b013e318276fbcb
- Kornø, M., Eldrup, N., & Sillesen, H. (2009). Comparison of ankle-brachial index measured by an automated oscillometric apparatus with that by standard Doppler technique in vascular patients. European Journal of Vascular and Endovascular Surgery, 38(5), 610-615. https://doi.org/10.1016/j.ejvs.2009.07.004
- Allen, J. (2007). Photoplethysmography and its application in clinical physiological measurement. Physiological Measurement, 28(3), R1-R39. https://doi.org/10.1088/0967-3334/28/3/R01
- Allen, J., Overbeck, K., Nath, A. F., Murray, A., & Stansby, G. (2008). A prospective comparison of bilateral photoplethysmography versus the ankle-brachial pressure index for detecting and quantifying lower limb peripheral arterial disease. Journal of Vascular Surgery, 47(4), 794-802. https://doi.org/10.1016/j.jvs.2007.11.057
- Allen, J., Liu, H., Iqbal, S., Zheng, D., & Stansby, G. (2021). Deep learning-based photoplethysmography classification for peripheral arterial disease detection: a proof-of-concept study. Physiological Measurement, 42(5), 054002. https://doi.org/10.1088/1361-6579/abf9f3
Related articles
PPG Vascular Age Assessment: Arterial Stiffness Measurement from Pulse Wave Analysis
**Arterial stiffness is one of the earliest detectable markers of cardiovascular disease, and the PPG waveform encodes surprisingly rich information a...
Driver Drowsiness Detection with PPG: How Pulse Sensors Monitor Fatigue
Technical guide to PPG-based driver drowsiness detection covering HRV fatigue markers, sensor placement options, algorithm accuracy, and integration with automotive safety systems.
Pulse Wave Analysis Using PPG: Waveform Features, Vascular Health, and Clinical Applications
Complete guide to pulse wave analysis from PPG signals. Covers augmentation index, stiffness index, derivatives, fiducial points, and vascular assessment.
What Is Pulse Wave Velocity? Normal Ranges, Clinical Thresholds, and PPG Estimation
Plain-language explanation of pulse wave velocity, normal ranges by age, clinical risk thresholds, and how PPG wearables estimate PWV from pulse transit time.
Wearable AHI Estimation: Can PPG Approximate the Apnea-Hypopnea Index?
Can wearable PPG estimate AHI? See where ODI-based severity tracking helps, where calibration fails, and what validation wearables need before clinical use.