PPG Inter-Beat Interval Accuracy: IBI Precision vs ECG Gold Standard
**Inter-beat interval (IBI) measurement from photoplethysmography achieves mean absolute errors of 2-10 ms compared to ECG under resting conditions, b...
- Arrhythmia & ECG
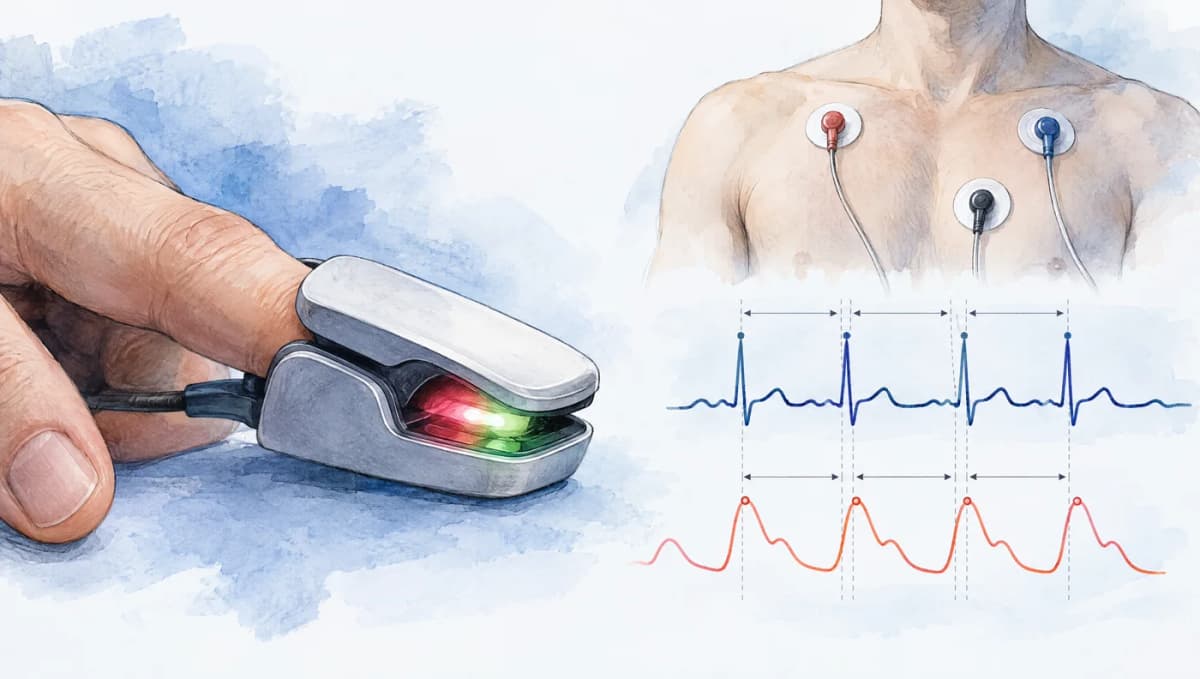
Inter-beat interval (IBI) measurement from photoplethysmography achieves mean absolute errors of 2-10 ms compared to ECG under resting conditions, but this precision degrades substantially during motion and varies with detection algorithm, sampling rate, and measurement site. Understanding the sources and magnitudes of IBI timing errors is critical for anyone using PPG-derived pulse intervals for heart rate variability (HRV) analysis, autonomic nervous system assessment, or arrhythmia screening. This article examines the fundamental limits of PPG IBI accuracy, the algorithms that determine it, and the conditions under which PPG can or cannot substitute for ECG.
For foundational context on how PPG signals are generated and what physiological information they encode, see our introduction to PPG technology.
Defining Inter-Beat Intervals in PPG vs ECG
In electrocardiography, the inter-beat interval is measured as the R-R interval: the time between successive R-peaks of the QRS complex. The R-peak is a sharp, high-amplitude deflection that is relatively easy to detect with well-established algorithms like Pan-Tompkins (Pan & Tompkins, 1985; doi:10.1109/TBME.1985.325532). The QRS complex has a duration of 80-120 ms, with the R-peak itself representing a near-instantaneous electrical event that can be localized to within 1-2 ms at standard ECG sampling rates of 250-1000 Hz.
In photoplethysmography, the analogous measurement is the pulse-to-pulse interval (PPI), sometimes called the peak-to-peak interval (PPI) or simply the PPG-derived IBI. The PPG waveform represents the pulsatile blood volume change in tissue, which is a mechanical and hemodynamic event occurring downstream of the electrical cardiac activation. The systolic upstroke of the PPG pulse corresponds to the arrival of the arterial pressure wave at the measurement site, which occurs approximately 200-300 ms after the ECG R-peak at the fingertip and 100-200 ms at the wrist.
This delay, known as the pulse arrival time (PAT) or pulse transit time (PTT), is not constant. It varies with blood pressure, arterial compliance, sympathetic tone, and respiration. Consequently, even if both ECG R-peaks and PPG systolic peaks are detected with perfect precision, the PPG-derived IBI series will differ from the ECG R-R interval series because of beat-to-beat PTT variability. Schäfer and Vagedes (2013; doi:10.1016/j.ijcard.2012.03.119) systematically reviewed this issue and found that PTT variability contributes 1-5 ms of additional IBI error beyond what is attributable to detection algorithm limitations.
Fiducial Point Selection
The choice of fiducial point on the PPG waveform directly determines IBI measurement precision. Unlike the ECG R-peak, the PPG pulse does not have a single obvious landmark. Several fiducial points have been proposed and evaluated.
Systolic Peak
The most intuitive fiducial point is the maximum of the PPG systolic peak. This is the most commonly used point in consumer devices and many research implementations. The systolic peak is relatively easy to detect but has a significant disadvantage: the peak region of the PPG waveform is broad and rounded, meaning that small amounts of noise or waveform variability can shift the detected maximum by several milliseconds.
Maximum First Derivative (Maximum Slope)
The point of maximum upslope on the systolic rising edge provides a sharper, more temporally defined fiducial point. Because the rising edge of the PPG pulse is steeper than the peak region, this point is less sensitive to noise-induced jitter.
Foot of the Pulse
The onset point (foot) of the PPG pulse, defined as the minimum before the systolic upstroke, is another option. While less affected by waveform morphology changes, the foot point can be difficult to localize precisely because the transition from diastolic baseline to systolic upstroke is often gradual. The intersecting tangent method, which finds the intersection of the baseline tangent and the upslope tangent, improves foot localization (Chiu et al., 1991, doi:10.1016/0002-8703(91)90153-9).
Second Derivative Landmarks
The second derivative of the PPG waveform (SDPPG or acceleration plethysmogram) produces distinct peaks labeled a, b, c, d, and e waves. The 'a' wave corresponds to the initial systolic acceleration and provides a sharp fiducial point.
Algorithmic Approaches to PPG Peak Detection
The accuracy of PPG IBI measurement depends heavily on the detection algorithm employed. Several classes of algorithms have been developed, each with distinct performance characteristics.
Threshold-Based Detection
Simple amplitude threshold crossing is the most basic approach. A threshold is set relative to the signal amplitude (typically 50-70% of the recent peak amplitude), and a beat is detected when the signal crosses this threshold. While computationally trivial, threshold-based methods are highly sensitive to baseline drift, amplitude modulation from respiration, and motion artifacts. Adaptive thresholding, where the threshold is continuously updated based on recent signal statistics, substantially improves robustness. The performance of threshold methods is described in detail in our PPG signal processing algorithms guide.
Derivative-Based Detection
Taking the first derivative of the PPG signal converts the broad systolic peak into a zero-crossing problem, which can be more precisely localized. Combining the first derivative with adaptive thresholding creates a robust detector that identifies the maximum upslope of each pulse. Aboy et al. (2005; doi:10.1109/TBME.2005.855725) developed a derivative-based PPG beat detector that achieved sensitivity of 99.5% and positive predictive value of 99.6% on clinical monitoring data.
Template Matching
Cross-correlation with a learned pulse template can identify beats even in moderately corrupted signals. The template is typically initialized from a clean segment and updated periodically. Template matching provides timing precision that depends on the template quality and update strategy.
Wavelet-Based Detection
Wavelet transform methods decompose the PPG signal across multiple time-frequency scales, allowing beat detection at scales where the pulse morphology is most distinct from noise. The stationary wavelet transform (SWT) with a scale corresponding to the cardiac frequency band has proven effective.
Deep Learning Approaches
Recent work has applied convolutional neural networks (CNNs) and recurrent networks to PPG beat detection. Reiss et al. (2019; doi:10.3390/s19143079) showed that deep learning detectors can maintain high accuracy even during moderate motion, outperforming classical methods on the PPG-DaLiA dataset. However, deep learning approaches require substantially more computational resources and training data, and their performance advantage over well-tuned classical methods is most apparent in noisy conditions.
Quantitative Accuracy Benchmarks
The accuracy of PPG IBI measurement has been evaluated across numerous studies with varying conditions, populations, and measurement sites. The following summarizes key findings.
Resting Conditions
Under supine or seated rest without motion, PPG IBI accuracy is consistently high across studies. Gil et al. (2010; doi:10.1088/0967-3334/31/9/015) found no statistically significant differences between time-invariant PRV and HRV indices in 17 young subjects during a tilt-table test, with the indices correlating at 0.99 ± 0.01. Schäfer and Vagedes (2013; doi:10.1016/j.ijcard.2012.03.119) reviewed the literature and concluded that PRV is sufficiently accurate at rest, although short-term variability tends to be somewhat overestimated, and physical activity and some mental stressors can impair agreement with HRV to an unacceptable extent.
At the wrist, accuracy is slightly lower due to the smaller signal amplitude and greater susceptibility to motion. Bent et al. (2020; doi:10.1038/s41746-020-0226-6) evaluated wrist PPG from the Apple Watch and Fitbit against chest ECG in 53 participants and found mean absolute IBI errors of 8-15 ms during seated rest.
During Controlled Breathing
Paced breathing protocols are commonly used to assess HRV accuracy because they induce known respiratory sinus arrhythmia patterns.
During Motion
Motion dramatically degrades PPG IBI accuracy. Even with advanced motion artifact removal algorithms, residual artifacts can shift detected peaks by tens of milliseconds. The degradation is not uniform: some beats may be detected accurately while others are severely distorted or entirely missed, creating gaps in the IBI series that are particularly problematic for HRV calculation.
Across Populations
Signal quality and consequently IBI accuracy varies with skin pigmentation, age, and vascular health. Fallow et al. (2013; doi:10.1007/s10877-013-9436-7) tested four wavelengths in 23 adults of varying skin types and found that the darkest skin type (type V) had significantly lower PPG modulation than all other skin types, although green light still gave the greatest modulation at rest. Elderly subjects with reduced peripheral perfusion or arterial stiffness may also show degraded PPG pulse morphology, making fiducial point detection less precise. For more on how PPG wavelength affects measurement quality across skin tones, see our wavelength comparison guide.
Impact of Sampling Rate on IBI Precision
The temporal resolution of PPG IBI measurement is fundamentally bounded by the sampling rate. At a sampling rate of Fs Hz, the minimum detectable IBI change is 1/Fs seconds. For a typical consumer wearable sampling at 25 Hz, this means a temporal resolution of 40 ms, which is clearly inadequate for HRV analysis requiring millisecond-level precision.
Raw Resolution Limits
At 25 Hz: 40 ms resolution. At 50 Hz: 20 ms resolution. At 100 Hz: 10 ms resolution. At 250 Hz: 4 ms resolution. Since meaningful HRV variations (particularly in the HF band) involve IBI fluctuations of 10-50 ms, sampling rates below 100 Hz introduce significant quantization effects that can bias HRV metrics.
Interpolation Methods
Sub-sample interpolation can substantially improve effective temporal resolution. Parabolic interpolation fits a second-order polynomial to the three samples surrounding the detected peak, estimating the true peak location with sub-sample precision. Merri et al. (1990; doi:10.1109/10.43621) analyzed how the sampling frequency of the ECG affects spectral analysis of heart rate variability, which is why low-rate signals benefit from interpolation of the fiducial point.
Cubic spline interpolation, which upsamples the PPG signal before peak detection, provides even finer resolution. Choi and Shin (2017; doi:10.1088/1361-6579/aa5efa) down-sampled PPG recordings and found no significant difference from ECG-derived HRV for any PRV variable as long as the sampling frequency was at least 25 Hz. However, interpolation cannot recover information that was not captured by the original sampling: it smooths between samples but cannot detect events occurring between sample points.
HRV Metric Agreement Between PPG and ECG
The ultimate test of PPG IBI accuracy for most applications is whether the derived HRV metrics agree with ECG-derived values. The agreement depends on which specific HRV metric is being computed.
Time-Domain Metrics
SDNN (standard deviation of normal-to-normal intervals) shows strong PPG-ECG agreement with typical correlation coefficients of r = 0.95-0.99 and mean biases below 5% at rest (Schäfer & Vagedes, 2013). RMSSD, which is more sensitive to short-term variability and thus to individual beat timing precision, shows slightly lower but still strong agreement (r = 0.90-0.98). pNN50 (percentage of successive intervals differing by more than 50 ms) tends to show the poorest agreement because it is a threshold metric: small timing errors near the 50 ms boundary can flip beats above or below the threshold, amplifying the effect of IBI inaccuracy.
Frequency-Domain Metrics
LF power (0.04-0.15 Hz) and HF power (0.15-0.4 Hz) from PPG generally agree well with ECG values at rest, and during a tilt test Gil et al. (2010) found the temporal patterns of LF and HF power from PRV and HRV correlated at 0.98 and 0.95, respectively, with the larger differences in the respiration-related HF band. The LF/HF ratio, commonly used as an index of sympathovagal balance, shows more variable agreement because it is a ratio metric where errors in both numerator and denominator compound. For comprehensive interpretation of these metrics, see our HRV analysis guide.
Nonlinear Metrics
Poincaré plot parameters (SD1 and SD2) derived from PPG show high concordance with ECG values at rest. SD1, which reflects short-term variability (mathematically related to RMSSD), typically correlates at r > 0.95. Sample entropy and detrended fluctuation analysis exponents show more variable agreement because these measures are sensitive to the exact timing and ordering of individual beats.
Practical Recommendations
For researchers and engineers implementing PPG-based IBI measurement, several practical guidelines emerge from the literature.
First, use the maximum first derivative or second derivative 'a' wave as the fiducial point rather than the systolic peak. The sharper temporal definition of these landmarks reduces detection jitter by 30-50% compared to peak-based approaches.
Second, sample at a minimum of 100 Hz for HRV applications, or apply sub-sample interpolation if hardware constraints limit the sampling rate. Parabolic interpolation at the detected peak provides meaningful improvement with negligible computational cost.
Third, implement robust beat quality assessment. Not every detected PPG pulse should be trusted for IBI calculation. Signal quality indices (SQI) based on waveform morphology, amplitude consistency, and inter-beat interval plausibility should be used to flag or exclude unreliable beats. For approaches to signal quality assessment, see our PPG signal processing algorithms documentation.
Fourth, restrict HRV analysis to periods of minimal motion. Even with advanced motion artifact removal, the residual IBI timing error during movement is typically too large for reliable HRV calculation. Use accelerometer data to identify stationary segments and compute HRV only from those windows.
Fifth, report PPG-ECG agreement statistics alongside any PPG-derived HRV results. Bland-Altman analysis, ICC (intraclass correlation coefficient), and limits of agreement provide a more complete picture of measurement validity than correlation coefficients alone, which can appear high even when systematic biases exist.
Conclusion
PPG-derived inter-beat intervals can achieve sufficient accuracy for many HRV applications under controlled conditions, with mean absolute errors of 2-10 ms at rest when using appropriate algorithms and adequate sampling rates. The technology falls short of ECG precision for applications requiring sub-millisecond beat timing or robust performance during physical activity. As detection algorithms improve and sampling rates increase in consumer devices, the gap between PPG and ECG IBI accuracy continues to narrow, but the fundamental limitation of pulse transit time variability ensures that PPG will always measure a slightly different physiological quantity than ECG. Understanding these differences is essential for correctly interpreting PPG-derived cardiac timing data in both research and clinical contexts.
For further exploration of PPG signal analysis techniques, visit our algorithms reference and PPG learning center.
References
- Gil E, Orini M, Bailón R, Vergara JM, Mainardi L, Laguna P. Photoplethysmography pulse rate variability as a surrogate measurement of heart rate variability during non-stationary conditions. Physiol Meas. 2010;31(9):1271-1290. https://doi.org/10.1088/0967-3334/31/9/015
- Schäfer A, Vagedes J. How accurate is pulse rate variability as an estimate of heart rate variability? A review on studies comparing photoplethysmographic technology with an electrocardiogram. Int J Cardiol. 2013;166(1):15-29. https://doi.org/10.1016/j.ijcard.2012.03.119
- Fallow BA, Tarumi T, Tanaka H. Influence of skin type and wavelength on light wave reflectance. J Clin Monit Comput. 2013;27(3):313-317. https://doi.org/10.1007/s10877-013-9436-7
- Merri M, Farden DC, Mottley JG, Titlebaum EL. Sampling frequency of the electrocardiogram for spectral analysis of the heart rate variability. IEEE Trans Biomed Eng. 1990;37(1):99-106. https://doi.org/10.1109/10.43621
- Choi A, Shin H. Photoplethysmography sampling frequency: pilot assessment of how low can we go to analyze pulse rate variability with reliability? Physiol Meas. 2017;38(3):586-600. https://doi.org/10.1088/1361-6579/aa5efa
Core guide: What Is an Interbeat Interval?
Related articles
rPPG vs Contact PPG Accuracy
Remote photoplethysmography and contact PPG measure the same physiological phenomenon through very different means. Both detect blood volume changes i...
Stress Tracker Accuracy Guide: What Wearables Actually Measure
Independent review of wearable stress tracker accuracy covering HRV methods, sensor limitations, and how to interpret stress scores from Garmin, Fitbit, and Apple Watch.
PPG vs ECG Accuracy Comparison: Heart Rate, HRV, and Arrhythmia Detection Data
PPG vs ECG accuracy compared for heart rate, HRV metrics, arrhythmia detection, and respiratory rate with published validation data and comparison tables.
PPG Heart Rate Measurement: Algorithms, Accuracy, and Practical Implementation
How PPG measures heart rate step by step. Learn peak detection algorithms, beat-to-beat vs averaged HR, and accuracy benchmarks for rest, exercise, and sleep.
rPPG Lighting Conditions Accuracy
Remote photoplethysmography captures the subtle color fluctuations your skin makes with every heartbeat. That signal is tiny — on the order of 0.1 to ...
Devices in this article
Research records with the datasets, papers and published validation results for each device.