Continuous Blood Pressure Monitoring from PPG: Beat-to-Beat Waveform Analysis
**Beat-to-beat blood pressure monitoring from PPG waveform analysis represents the frontier of non-invasive hemodynamic assessment, offering the possi...
- Blood Pressure
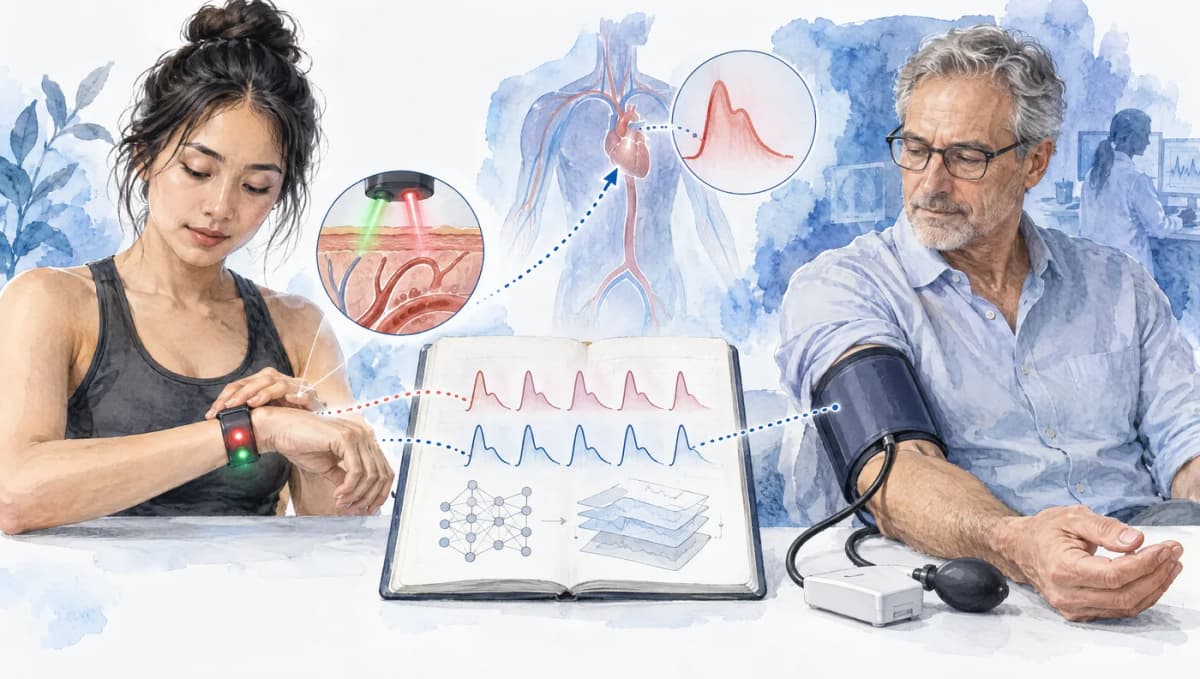
Beat-to-beat blood pressure monitoring from PPG waveform analysis represents the frontier of non-invasive hemodynamic assessment, offering the possibility of continuous pressure tracking without arterial catheterization or even an inflatable cuff. While intermittent cuffless blood pressure estimation from PPG has received widespread attention, continuous waveform reconstruction -- recovering the full arterial pressure waveform from the PPG pulse contour on every cardiac cycle -- is a more technically demanding and clinically valuable problem.
Continuous blood pressure monitoring has traditionally been restricted to invasive arterial lines in operating rooms and ICUs, or to cumbersome volume-clamp devices (Finapres/ClearSight) in research settings. The proliferation of high-quality PPG sensors in wearable devices has motivated extensive research into extracting beat-to-beat hemodynamic information from the peripheral PPG waveform. This article reviews the signal processing, transfer function, and machine learning approaches to this challenge, with attention to the physiological constraints that define the accuracy ceiling.
Why Continuous Monitoring Matters
Intermittent blood pressure measurements, even if taken every few minutes, miss clinically significant hemodynamic events. In noncardiac surgery, mean arterial pressure below an absolute threshold of 65 mmHg or a relative threshold of 20% below baseline was progressively related to both myocardial and kidney injury, and longer exposure was associated with higher odds (Salmasi et al., 2017; doi:10.1097/ALN.0000000000001432). These transient episodes can only be captured by continuous monitoring.
Beyond acute care, continuous ambulatory BP data reveals patterns invisible to clinic measurements. A diminished nocturnal decline in blood pressure is a risk factor for cardiovascular mortality independent of 24-hour blood pressure: in 1,542 residents of Ohasama, Japan, followed for a mean of 9.2 years, each 5% smaller nocturnal decline was associated with approximately 20% greater cardiovascular mortality risk (Ohkubo et al., 2002; doi:10.1097/00004872-200211000-00017). Blood pressure variability itself also matters: visit-to-visit variability in systolic pressure was a strong predictor of stroke independent of mean systolic pressure (Rothwell et al., 2010; doi:10.1016/S0140-6736(10)60308-X).
The Peripheral PPG Waveform and Central Pressure
A fundamental challenge in PPG-based continuous BP estimation is the transformation between central (aortic) and peripheral pressure waveforms. The PPG signal measured at the finger or wrist reflects the volumetric blood pulse in the peripheral microcirculation, which differs from central aortic pressure in several important ways.
Pulse Wave Amplification
As the pressure wave propagates from the aorta to the periphery, it undergoes progressive amplification. Peripheral systolic pressure is typically 10-20 mmHg higher than central aortic systolic pressure, while diastolic and mean pressures remain relatively preserved. This amplification results from wave reflection at arterial bifurcations and impedance mismatches, and its magnitude varies with age (decreasing in older subjects due to arterial stiffening), vasoactive medications, and autonomic state.
The PPG waveform further modifies this picture because it measures volume rather than pressure. The relationship between transmural pressure and vessel volume (the compliance curve) is nonlinear: at higher pressures, arteries become stiffer, and the same pressure change produces a smaller volume change. This pressure-dependent compliance means the PPG waveform is a distorted version of the peripheral pressure waveform, with the distortion itself depending on the prevailing blood pressure -- a circular problem for BP estimation.
Transfer Function Approaches
Generalized transfer functions (GTFs) have been developed to transform peripheral arterial waveforms to central aortic pressure estimates. Chen et al. (1997) showed in 20 patients that a generalized transfer function can estimate central aortic pressure from radial tonometry to within 0.2 +/- 3.8 mmHg error (doi:10.1161/01.CIR.95.7.1827). Several groups have attempted to extend this approach to PPG.
Millasseau et al. (2000) showed in 60 subjects that a single generalized transfer function could predict radial and digital artery pressure waveforms from the finger PPG volume pulse, with average root mean square errors of 4.4 +/- 2.0 and 4.3 +/- 1.9 mmHg, respectively (doi:10.1161/01.HYP.36.6.952). The Arteriograph and SphygmoCor systems use related approaches with tonometric input rather than PPG.
The limitation of GTFs is that they assume a fixed arterial system transfer characteristic. In reality, the transfer function changes with heart rate, blood pressure level, vasoactive drugs, and aging. Subject-specific and condition-adaptive transfer functions have been proposed but require calibration data that limits their practical utility.
Pulse Contour Analysis Methods
Pulse contour analysis extracts hemodynamic parameters from the shape of individual PPG pulses. Originally developed for arterial line waveforms (the PiCCO and FloTrac systems), these methods have been adapted for non-invasive PPG input.
Windkessel Model Fitting
The arterial system can be modeled as a Windkessel circuit, where the heart acts as a pulsatile pump driving flow into an elastic arterial compliance (capacitor) that discharges through peripheral resistance (resistor). The three-element Windkessel model adds aortic characteristic impedance to capture the systolic pressure peak more accurately.
By fitting a Windkessel model to individual PPG pulse contours, the model parameters (compliance, resistance, impedance) can be estimated on a beat-to-beat basis. Blood pressure is then derived from these parameters:
where MAP is mean arterial pressure, CO is cardiac output, and SVR is systemic vascular resistance.
Waveform Feature Extraction
Beat-to-beat analysis extracts time-domain features from each PPG pulse cycle:
- Systolic peak amplitude: Correlates with pulse pressure (SBP - DBP) but is confounded by sensor coupling variability.
- Systolic rise time: The interval from pulse onset to peak, reflecting arterial stiffness and wave propagation velocity. Faster rise times correlate with higher SBP.
- Diastolic time constant: The exponential decay rate during diastole, reflecting the product of peripheral resistance and arterial compliance (the RC time constant).
- Dicrotic notch position and amplitude: Reflects aortic valve closure timing and the magnitude of wave reflection. A deeper notch with later timing indicates better arterial compliance and typically lower blood pressure.
- Pulse width at half-maximum (FWHM): An integrated measure of the systolic ejection phase duration.
- Waveform area ratios: The ratio of systolic area (onset to dicrotic notch) to total pulse area reflects the balance of cardiac ejection and peripheral runoff.
Deep Learning for Waveform-to-Pressure Mapping
The most recent and highest-performing approaches use deep neural networks to learn a direct mapping from PPG waveform segments to arterial blood pressure values or waveforms.
End-to-End Waveform Regression
Ibtehaz et al. (2022) developed PPG2ABP, a two-stage cascaded deep learning method that estimates the continuous arterial blood pressure waveform from an input PPG signal, with a waveform mean absolute error of 4.604 mmHg (doi:10.3390/bioengineering9110692). SBP, DBP, and MAP computed from the estimated waveform had mean absolute errors of 5.727, 3.449, and 2.310 mmHg, respectively, even though the model was not explicitly trained to predict them.
The PPG2ABP approach reconstructs the full pressure waveform, enabling extraction of not only SBP, DBP, and MAP but also derived parameters like pulse pressure, dP/dt (rate of pressure rise, reflecting cardiac contractility), and systolic pressure variation (indicating fluid responsiveness in mechanically ventilated patients).
Sequence-to-Sequence Models
Recurrent architectures capture temporal context across multiple beats. Harfiya et al. (2021) used an LSTM-based signal-to-signal translation model to convert raw PPG into a continuous arterial blood pressure waveform, then extracted SBP and DBP from it; the results met AAMI criteria and BHS grade A (doi:10.3390/s21092952).
Attention and Transformer Models
Transformer-based models have shown promise for capturing long-range dependencies in PPG signals. The self-attention mechanism can learn to weight different portions of the PPG waveform dynamically, potentially capturing respiratory modulation, Mayer waves, and other slow hemodynamic oscillations that modulate beat-to-beat pressure.
Paviglianiti et al. (2021) compared convolutional (ResNet, WaveNet) and recurrent (LSTM) networks for predicting arterial blood pressure from PPG alone and from PPG plus ECG on MIMIC data. Adding ECG improved every configuration, and the best model, a ResNet followed by three LSTM layers, reached MAEs of 4.118 mmHg for systolic and 2.228 mmHg for diastolic pressure (doi:10.1007/s12559-021-09910-0).
Signal Quality and Preprocessing Requirements
Continuous beat-to-beat BP estimation imposes stringent signal quality requirements that exceed those needed for simple heart rate extraction.
Waveform Fidelity
Heart rate can be extracted from a PPG signal even when waveform morphology is distorted, using peak detection or frequency analysis. Blood pressure estimation, however, relies on subtle morphological features -- the exact shape of the systolic upstroke, the position and depth of the dicrotic notch, the diastolic decay contour -- that are easily corrupted by motion artifacts, baseline wander, and sensor coupling changes.
High-quality continuous BP estimation requires PPG signals with signal-to-noise ratio exceeding 15 dB, minimal baseline wander (high-pass filtering below 0.3 Hz risks distorting the diastolic decay), and stable sensor-tissue optical coupling. For guidance on ensuring signal quality, see our article on PPG motion artifact removal.
Beat Segmentation
Accurate beat-to-beat analysis requires precise segmentation of individual PPG pulses. The pulse onset (foot) detection is particularly critical because it serves as the reference point for timing features. Errors in onset detection of even 10-20 ms can shift systolic rise time estimates enough to alter BP predictions by several mmHg.
Adaptive beat segmentation algorithms must handle heart rate variability, premature beats (PACs/PVCs that alter waveform morphology), and respiratory modulation of pulse amplitude. Template matching, derivative-based methods, and learned beat detectors each have strengths depending on the signal quality and target population.
Validation Challenges and Clinical Translation
The path from laboratory demonstration to clinical deployment of continuous PPG-based BP monitoring faces several unresolved challenges.
The Generalization Gap
Models trained on MIMIC-III ICU data perform well on held-out MIMIC data but typically show degraded performance on ambulatory or healthy-population datasets. This domain gap reflects differences in patient demographics (ICU patients tend to be older, sicker, and pharmacologically managed), signal acquisition hardware (ICU monitors vs. wearable sensors), and hemodynamic conditions (ICU patients have more extreme BP ranges but less motion artifact).
This is why external validation on independent datasets, with controlled hemodynamic challenges such as posture changes, cold pressor tests, and exercise, matters more than headline MAE figures reported on MIMIC alone.
Regulatory Requirements
The FDA recognizes continuous BP devices as Class II medical devices requiring 510(k) clearance. The validation protocol requires demonstration of accuracy across a clinically meaningful range of blood pressures, including hypertensive values (SBP > 160 mmHg), in a population representative of the intended use. Importantly, the FDA distinguishes between devices intended for trend monitoring (tracking relative changes from a calibrated baseline) and devices intended for absolute measurement (providing accurate BP values without prior calibration).
For the latest on regulatory developments and the path toward clinical deployment, see our exploration of cuffless blood pressure technology and the broader conditions that continuous monitoring aims to address.
Toward Clinical Deployment
Several commercial efforts are advancing toward clinical-grade continuous PPG-based BP monitoring. Biobeat (Israel) has obtained CE marking for a wrist-worn device providing continuous BP trending in hospitalized patients. Aktiia (Switzerland) received CE marking for a wrist-worn oscillometric-PPG hybrid that provides nighttime continuous BP measurements after initial cuff calibration.
The convergence of improved deep learning architectures, larger and more diverse training datasets, multi-modal sensor fusion, and maturing regulatory frameworks suggests that clinically validated continuous PPG-based BP monitoring for specific clinical scenarios (post-surgical ward monitoring, medication titration follow-up) may reach the market within the next 2-3 years, with broader consumer applications following as calibration-free accuracy improves.
References
- Salmasi, V., et al. (2017). Relationship between intraoperative hypotension, defined by either reduction from baseline or absolute thresholds, and acute kidney and myocardial injury after noncardiac surgery. Anesthesiology, 126(1), 47-65. https://doi.org/10.1097/ALN.0000000000001432
- Ohkubo, T., et al. (2002). Prognostic significance of the nocturnal decline in blood pressure in individuals with and without high 24-h blood pressure: the Ohasama study. Journal of Hypertension, 20(11), 2183-2189. https://doi.org/10.1097/00004872-200211000-00017
- Rothwell, P. M., et al. (2010). Prognostic significance of visit-to-visit variability, maximum systolic blood pressure, and episodic hypertension. The Lancet, 375(9718), 895-905. https://doi.org/10.1016/S0140-6736(10)60308-X
- Chen, C. H., et al. (1997). Estimation of central aortic pressure waveform by mathematical transformation of radial tonometry pressure. Circulation, 95(7), 1827-1836. https://doi.org/10.1161/01.CIR.95.7.1827
- Millasseau, S. C., et al. (2000). Noninvasive assessment of the digital volume pulse: comparison with the peripheral pressure pulse. Hypertension, 36(6), 952-956. https://doi.org/10.1161/01.HYP.36.6.952
- Ibtehaz, N., et al. (2022). PPG2ABP: Translating photoplethysmogram (PPG) signals to arterial blood pressure (ABP) waveforms. Bioengineering, 9(11), 692. https://doi.org/10.3390/bioengineering9110692
- Harfiya, L. N., Chang, C. C., & Li, Y. H. (2021). Continuous blood pressure estimation using exclusively photopletysmography by LSTM-based signal-to-signal translation. Sensors, 21(9), 2952. https://doi.org/10.3390/s21092952
- Paviglianiti, A., et al. (2021). A comparison of deep learning techniques for arterial blood pressure prediction. Cognitive Computation, 14, 1689-1710. https://doi.org/10.1007/s12559-021-09910-0
Related articles
White-Coat vs Masked Hypertension: Where Wearables Help and Where ABPM Still Wins
White-coat and masked hypertension are opposite out-of-office blood pressure phenotypes. This guide explains the difference, the risks of each pattern, and where cuffless wearables can help compared with ambulatory blood pressure monitoring.
Cuffless Blood Pressure Monitoring: When Will It Actually Work?
An industry analysis of cuffless blood pressure monitoring technologies including PTT, PWV, PPG morphology, ultrasound, and tonometry. Covers calibration challenges, regulatory hurdles, current players (Samsung, Aktiia, Biobeat, Valencell), and a realistic timeline for when truly calibration-free devices will be available.
Pulse Wave Analysis Using PPG: Waveform Features, Vascular Health, and Clinical Applications
Complete guide to pulse wave analysis from PPG signals. Covers augmentation index, stiffness index, derivatives, fiducial points, and vascular assessment.
Patient Monitoring Systems and PPG: From Hospital Bedside to Home Health
Learn how PPG technology powers modern patient monitoring systems in hospitals and homes, covering multiparameter monitors, pulse oximetry, and remote health tracking.
Non-Invasive Cardiac Output Estimation from PPG Waveform Morphology
**Cardiac output -- the volume of blood the heart pumps per minute -- is the fundamental measure of cardiovascular performance, yet its non-invasive m...
Athletic and Sports Performance Metrics from PPG: VO2max, Lactate Threshold & Recovery Analysis
**The photoplethysmographic (PPG) sensor in a wrist-worn device or chest-strap monitor captures far more than just heart rate during exercise. The con...

