Non-Invasive Cardiac Output Estimation from PPG Waveform Morphology
**Cardiac output -- the volume of blood the heart pumps per minute -- is the fundamental measure of cardiovascular performance, yet its non-invasive m...
- PPG & Signal Processing
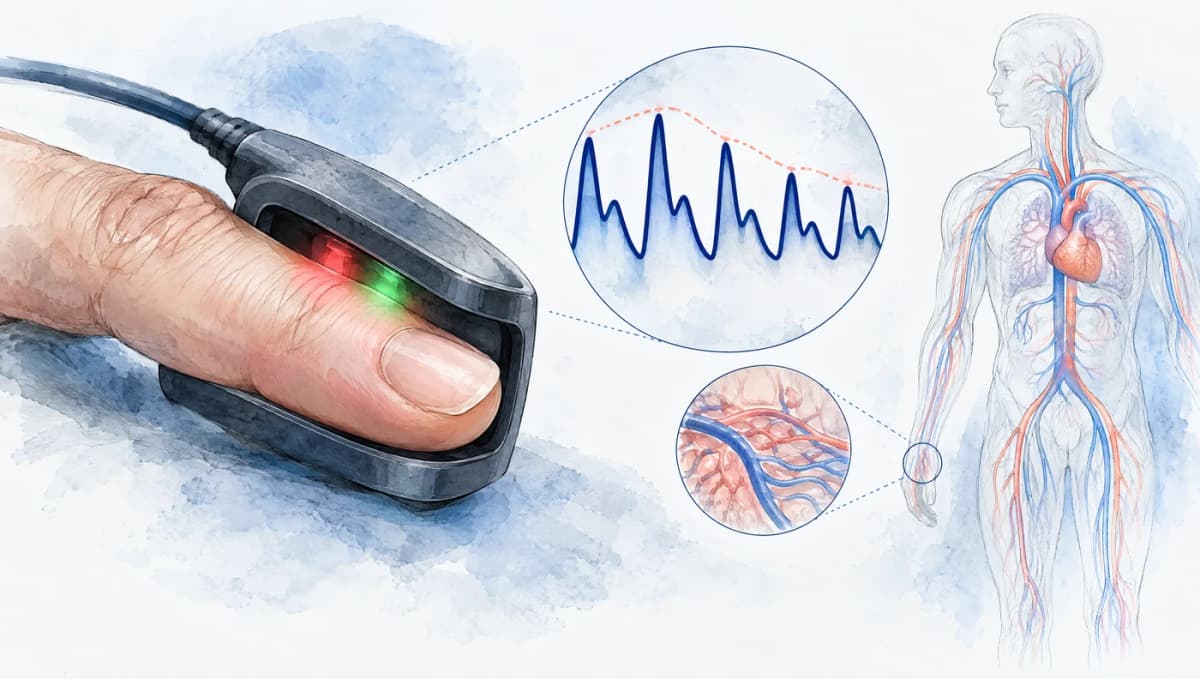
Cardiac output -- the volume of blood the heart pumps per minute -- is the fundamental measure of cardiovascular performance, yet its non-invasive measurement remains one of the most technically challenging problems in physiological monitoring. The peripheral PPG waveform carries information about cardiac output encoded in its amplitude, shape, and timing, but extracting quantitative flow estimates from this volumetric signal requires bridging the complex transfer function between central cardiac pump performance and peripheral vascular pulsations.
Cardiac output (CO) monitoring is the cornerstone of hemodynamic management in critical care, anesthesia, and cardiology. The gold standard -- thermodilution via pulmonary artery catheterization -- is invasive, expensive, and carries procedural risk. Semi-invasive alternatives like arterial line pulse contour analysis (PiCCO, FloTrac) require arterial catheterization. Echocardiography provides non-invasive CO measurement but requires skilled operators and is intermittent. A continuous, non-invasive CO monitor based on PPG technology -- sensors already embedded in pulse oximeters and wearable devices -- could democratize hemodynamic monitoring from the ICU to the general ward to the home.
Physiological Foundations
From Cardiac Output to the Peripheral PPG Pulse
Understanding why PPG can potentially estimate cardiac output requires tracing the path from left ventricular ejection to the peripheral pulse waveform.
During each heartbeat, the left ventricle ejects a stroke volume (SV, typically 60-100 mL at rest) into the aorta. This bolus of blood generates a pressure pulse that propagates through the arterial tree at a velocity (pulse wave velocity, PWV) of 5-15 m/s, much faster than the actual blood flow velocity (0.3-0.5 m/s). As the pressure wave traverses the arterial system, it encounters impedance changes at branch points and arterioles, generating reflected waves that travel back toward the heart and interact with the forward-traveling wave.
The PPG sensor at the periphery (finger, wrist, earlobe) detects the net result of this wave propagation process: the volumetric blood pulse in the local microvascular bed. The amplitude, shape, and timing of this pulse carry information about the upstream hemodynamics:
- Pulse amplitude reflects pulse pressure (SBP - DBP), which is related to stroke volume and arterial compliance by the relationship: , where is total arterial compliance.
- Systolic upstroke slope reflects the rate of aortic pressure rise (dP/dt), which correlates with left ventricular contractility and aortic impedance.
- Diastolic decay reflects the arterial time constant (), the product of systemic vascular resistance () and arterial compliance ().
- Dicrotic notch characteristics reflect aortic valve closure timing, wave reflection magnitude, and the balance between forward and reflected waves.
The central challenge is that the PPG signal is a peripheral volumetric measurement, not a central pressure measurement. The transfer function between aortic pressure/flow and peripheral PPG volume is complex, nonlinear, and modulated by factors independent of cardiac output (peripheral vascular resistance, autonomic vasomotor tone, skin temperature, venous return dynamics).
The Windkessel Model Framework
The Windkessel model provides the standard theoretical framework for relating arterial pressure waveform morphology to cardiac output. The model represents the arterial system as an electrical circuit analog:
Two-Element Windkessel:
- Compliance (C): Elastic energy storage in the arterial walls, primarily the aorta. Analogous to a capacitor.
- Resistance (R): Peripheral vascular resistance from arterioles. Analogous to a resistor.
- The time constant governs the diastolic pressure decay: , where is the pressure at the beginning of diastole.
Three-Element Windkessel: Adds characteristic impedance () of the aorta in series, improving the systolic pressure peak fit:
- captures the impedance to pulsatile flow in the proximal aorta.
- This addition separates the effects of aortic impedance (affecting systolic peak shape) from peripheral resistance (affecting diastolic decay).
Four-Element Windkessel: Adds arterial inertance (L) representing blood mass inertia:
- Inertance affects the high-frequency components of the pressure waveform.
- Generally provides marginal improvement over the three-element model for CO estimation.
By fitting a Windkessel model to the arterial pressure or PPG waveform, the model parameters (, , ) can be estimated. Cardiac output is then derived from:
where MAP is mean arterial pressure and R is peripheral resistance estimated from the model fit. Alternatively, stroke volume can be estimated from the systolic area of the waveform and the compliance parameter.
Pulse Contour Methods for CO Estimation
The Systolic Area Method
The foundational pulse contour method for stroke volume estimation, developed by Wesseling and colleagues, relates stroke volume to the area under the systolic portion of the arterial pressure waveform, corrected for aortic impedance:
where is the systolic area (from pulse onset to the dicrotic notch), is aortic impedance (estimated from patient demographics -- age, sex, height, weight -- or from the pulse waveform itself), and is a calibration constant.
This principle underlies the commercial PiCCO (Pulsion Medical Systems) and FloTrac (Edwards Lifesciences) systems, which use invasive arterial line pressure waveforms. Adapting this to non-invasive PPG requires addressing two additional challenges: (1) the PPG waveform measures volume, not pressure, so the area relationship must account for the pressure-volume compliance curve; and (2) the PPG measurement site (finger, wrist) is far from the aorta, so wave transmission effects must be considered.
PPG Pulse Contour Analysis
Reisner et al. (2008) reviewed the utility of the photoplethysmogram in circulatory monitoring, noting that although the PPG resembles an arterial pressure waveform, its relation to the underlying circulation is complicated by optical, biomechanical, and physiologic covariates (doi:10.1097/ALN.0b013e31816c89e1). For cardiac output, this makes PPG-based methods better suited to tracking relative changes than to measuring absolute values. The distinction between absolute accuracy and trending ability is clinically important: many hemodynamic management decisions require knowing the direction and magnitude of CO changes in response to interventions (fluid bolus, vasopressor titration) rather than the absolute CO value.
Modified Liljestrand-Zander Method
Liljestrand and Zander (1928, doi:10.1007/BF02608853) compared cardiac output estimated from blood pressure measurement with the nitrous oxide method; their pressure-based estimate scales pulse pressure by the sum of systolic and diastolic pressure. An area-based PPG analogue, the stroke volume index can be estimated as:
where and are the areas above and below the mean level of the PPG pulse. This ratio is less sensitive to absolute signal amplitude calibration because it normalizes by the total pulse area. Related multi-beat methods have so far been validated on arterial pressure rather than PPG. Mukkamala et al. (2006) estimated proportional CO from the exponential diastolic pressure decay of peripheral arterial blood pressure waveforms, reporting an overall CO error of 14.6% against aortic flow probe measurements in six swine experiments (doi:10.1109/TBME.2005.869780).
Machine Learning Approaches
Feature-Based Models
Classical ML approaches extract hand-crafted features from the PPG waveform and train regression models to predict stroke volume or cardiac output.
Saugel et al. (2021) reviewed pulse wave analysis algorithms for estimating CO from the arterial pressure waveform, including Windkessel models, multi-beat analysis, and pulse power analysis (doi:10.1016/j.bja.2020.09.049). PPG-based models adapt similar waveform features, including:
- Systolic upstroke time and slope: Reflects rate of ventricular ejection and aortic impedance.
- Pulse width at various amplitude levels (25%, 50%, 75%): Captures the overall pulse shape, which changes with stroke volume and vascular tone.
- Diastolic decay time constant: Estimated by fitting an exponential to the diastolic portion; reflects the RC time constant of the arterial system.
- Augmentation index (AI): The ratio of the reflected wave amplitude to the forward wave amplitude; reflects wave reflection magnitude and arterial stiffness.
- Pulse area ratios: Systolic area, diastolic area, and their ratio.
- First and second derivative features: Peak values and timing of the first derivative (dPPG) and second derivative (ddPPG/acceleration plethysmogram) provide information about cardiac contractility and arterial stiffness.
Deep Learning on Raw PPG
Deep learning models can learn to extract CO-relevant features directly from raw PPG waveforms. This approach may capture subtle waveform characteristics that are not captured by traditional hand-crafted features.
Architectures explored for this task include 1D convolutional networks applied to short PPG segments and hybrid CNN-LSTM models that combine intra-beat morphology with inter-beat temporal patterns, such as respiratory-induced stroke volume variation. Validation datasets remain small and heterogeneous, so these models should be regarded as research prototypes.
Transfer Learning and Domain Adaptation
A key challenge for deep learning CO estimation is the limited availability of paired PPG-cardiac output training data. Most reference CO measurements (thermodilution, echocardiography) are obtained in hospital settings with different PPG hardware than consumer wearables.
One proposed strategy is transfer learning: pre-training a model on a large dataset such as MIMIC-III for blood pressure estimation, which shares many waveform features with CO estimation, and then fine-tuning it on a smaller dataset with CO reference values.
Validation Against Reference Methods
Thermodilution (Gold Standard)
Pulmonary artery catheter thermodilution provides intermittent CO measurements with a precision of approximately 10-15% (coefficient of variation of repeated measurements). The Bland-Altman framework is the standard for evaluating agreement between a new method and thermodilution:
- Bias: Mean difference between methods. Acceptable bias is typically less than 0.5 L/min.
- Limits of agreement (LOA): Mean +/- 1.96 SD of differences. Should be within +/- 1.5 L/min for clinical acceptability.
- Percentage error: LOA / mean reference CO. In a meta-analysis of cardiac output validation studies, Critchley and Critchley (1999) concluded that, given the imprecision of current reference methods, a new technique should be accepted if its limits of agreement are within +/- 30% (doi:10.1023/A:1009982611386).
PPG-based CO estimation has not yet consistently met this threshold across diverse clinical populations; the best results have come from controlled settings with calibrated systems and homogeneous patient populations.
Echocardiography
Transthoracic echocardiography (TTE) provides non-invasive CO measurement via Doppler velocity-time integral (VTI) across the aortic valve. While less precise than thermodilution (typical coefficient of variation 8-15%), TTE is widely available and non-invasive, making it a practical reference for ambulatory PPG validation studies.
Studies comparing PPG-based CO estimates to echocardiographic reference generally show better trending ability than absolute accuracy.
Clinical Applications and Future Directions
Goal-Directed Fluid Therapy
One of the most impactful potential applications of non-invasive CO monitoring is goal-directed fluid therapy (GDFT) during surgery. GDFT uses real-time CO or SV monitoring to guide intravenous fluid administration, optimizing tissue perfusion while avoiding fluid overload. In the OPTIMISE trial of high-risk patients undergoing major gastrointestinal surgery, Pearse et al. (2014) found that a cardiac output-guided hemodynamic therapy algorithm did not significantly reduce a composite of complications and 30-day mortality (36.6% vs. 43.4%; RR 0.84, 95% CI 0.71-1.01). However, an updated meta-analysis of 38 trials in the same paper associated the approach with fewer complications (31.5% vs. 41.6%; RR 0.77, 95% CI 0.71-0.83) (doi:10.1001/jama.2014.5305).
Currently, GDFT requires an arterial line with pulse contour analysis or esophageal Doppler, limiting its use to high-risk surgeries in major medical centers. A PPG-based CO monitor integrated into a standard pulse oximeter could extend GDFT to a much broader surgical population, potentially improving outcomes for millions of patients annually.
Stroke Volume Variation for Fluid Responsiveness
Stroke volume variation (SVV) -- the percentage change in stroke volume across the respiratory cycle -- is a validated predictor of fluid responsiveness in mechanically ventilated patients. In a meta-analysis of 29 studies (685 patients), Marik et al. (2009) found a mean SVV threshold of 11.6% +/- 1.9%, with a pooled sensitivity of 0.82 and specificity of 0.86 for predicting fluid responsiveness (doi:10.1097/CCM.0b013e3181a590da).
PPG-derived SVV can be estimated from the respiratory-induced amplitude variation (RIAV) of the pulse waveform. Cannesson et al. (2008) showed that the pleth variability index (PVI, available in Masimo monitors) predicts fluid responsiveness in mechanically ventilated patients under general anesthesia: in 25 patients, a PVI above 14% before volume expansion identified responders with 81% sensitivity and 100% specificity (doi:10.1093/bja/aen133). This represents one of the most clinically mature applications of PPG-based hemodynamic estimation, as it requires only relative (not absolute) stroke volume measurement.
For more on how respiratory modulations of the PPG signal encode hemodynamic information, see our article on PPG respiratory rate estimation. Our algorithms reference provides foundational signal processing methods relevant to pulse contour analysis, and our overview of cardiovascular conditions provides clinical context for hemodynamic monitoring applications. For preprocessing requirements, our guide to PPG motion artifact removal covers the signal quality considerations essential for reliable waveform morphology analysis.
Wearable Hemodynamic Monitoring
Looking further ahead, continuous CO estimation from wrist PPG could enable longitudinal hemodynamic tracking for heart failure patients. Serial changes in resting CO, exercise CO response, and nocturnal hemodynamic patterns could provide early warning of decompensation, enabling preemptive medication adjustment and reducing hospital readmissions. This application requires only accurate trending (detecting changes from an individual baseline) rather than absolute CO measurement, which plays to the relative strengths of PPG-based methods.
The convergence of improved PPG sensor hardware (multi-wavelength arrays, improved skin coupling), advanced signal processing for motion artifact removal, and deep learning models trained on growing databases of paired PPG-hemodynamic data suggests that clinically useful non-invasive CO estimation from PPG is an achievable near-term goal, likely first in controlled clinical settings (operating room, ICU) and eventually in ambulatory and wearable applications.
References
- Reisner, A., Shaltis, P. A., McCombie, D., & Asada, H. H. (2008). Utility of the photoplethysmogram in circulatory monitoring. Anesthesiology, 108(5), 950-958. https://doi.org/10.1097/ALN.0b013e31816c89e1
- Mukkamala, R., Reisner, A. T., Hojman, H. M., Mark, R. G., & Cohen, R. J. (2006). Continuous cardiac output monitoring by peripheral blood pressure waveform analysis. IEEE Transactions on Biomedical Engineering, 53(3), 459-467. https://doi.org/10.1109/TBME.2005.869780
- Saugel, B., et al. (2021). Cardiac output estimation using pulse wave analysis: physiology, algorithms, and technologies: a narrative review. British Journal of Anaesthesia, 126(1), 67-76. https://doi.org/10.1016/j.bja.2020.09.049
- Critchley, L. A., & Critchley, J. A. (1999). A meta-analysis of studies using bias and precision statistics to compare cardiac output measurement techniques. Journal of Clinical Monitoring and Computing, 15(2), 85-91. https://doi.org/10.1023/A:1009982611386
- Pearse, R. M., et al. (2014). Effect of a perioperative, cardiac output-guided hemodynamic therapy algorithm on outcomes following major gastrointestinal surgery. JAMA, 311(21), 2181-2190. https://doi.org/10.1001/jama.2014.5305
- Marik, P. E., Cavallazzi, R., Vasu, T., & Hirani, A. (2009). Dynamic changes in arterial waveform derived variables and fluid responsiveness in mechanically ventilated patients: a systematic review of the literature. Critical Care Medicine, 37(9), 2642-2647. https://doi.org/10.1097/CCM.0b013e3181a590da
- Cannesson, M., et al. (2008). Pleth variability index to monitor the respiratory variations in the pulse oximeter plethysmographic waveform amplitude and predict fluid responsiveness in the operating theatre. British Journal of Anaesthesia, 101(2), 200-206. https://doi.org/10.1093/bja/aen133
Related articles
PPG for Cardiac Monitoring: From Heart Rate to Heart Failure Detection
PPG is becoming a first-line cardiac monitoring tool. This guide covers validated applications: heart rate, HRV, atrial fibrillation, heart failure, and emerging ECG-free arrhythmia detection.
PPG Waveform Decomposition: Extracting Physiological Components from the Pulse Wave
**The photoplethysmography waveform is not a simple cardiac pulse but a composite signal encoding information about cardiac function, vascular complia...
PPG Respiratory Rate Estimation: Extracting Breathing Rate from Photoplethysmography
**Respiratory rate is the vital sign most sensitive to clinical deterioration, yet it is the least frequently and least accurately recorded in routine...
Continuous Blood Pressure Monitoring from PPG: Beat-to-Beat Waveform Analysis
**Beat-to-beat blood pressure monitoring from PPG waveform analysis represents the frontier of non-invasive hemodynamic assessment, offering the possi...
PPG Morphology Features
The shape of a photoplethysmographic pulse waveform is not merely a stylized heartbeat trace. Every contour, slope, and inflection point encodes speci...